

Fulltext
Full text is available in PDF
Official Journal of Research Center for Gastroenterology and Liver Diseases
Authors
A 35-year-old man was referred to our center because of low grade fever, vomiting, yellow sclera, and tenderness in the upper-right quadrant of his abdomen. Laboratory tests showed a white blood cell (WBC) of 7100/µL, a platelet of 184,000/µL, an erythrocyte sedimentation rate (ESR) of 4 mm/h, an alanine aminotransferase (ALT) of 525 U/L, an aspartate aminotransferase AST of 142 U/L, a total bilirubin level of 4.23 mg/dL, and a direct bilirubin level of 3.16 mg/dL. Viral hepatitis markers, immunoglobuline M antibody to cytomegalovirus (anti-CMV IgM), Ebstein-Barr virus (EBV) IgM, and immunologic markers of autoimmune hepatitis were negative. The patient was diagnosed with acute hepatitis. Alkaline phosphatase was in the normal range throughout the course of the disease. Because of the patient's occupation as a butcher and his history of eating semi-cooked sheep testes, serologic tests of brucellosis were conducted; the tests came out positive. We were concerned about the hepatotoxicity of standard regimens; therefore, we started treatment with streptomycin and ciprofloxacin regimens. Although liver enzyme had fallen and fever discontinued, the total and direct bilirubin concentrations in the patient's serum both increased in spite of using 2 weeks of the abovementioned drug regimen. The elevation of bilirubin could have been due to drug hepatotoxicity. Alternatively, a regimen containing ciprofloxacin may have not have been efficient enough and may have had effects on the direct bilirubin concentration. Fortunately, within 8 weeks, progressive recovery was noticed. Brucellosis should be considered in the differential diagnosis of fever and hepatitis for those who live in endemic areas, especially if his/her job was at high risk for acquiring brucellosis. We recommend taking a careful occupational and behavioral history for patients with acute hepatitis syndrome. We assumed that ciprofloxacin was not suitable for brucella hepatitis treatment and also it may cause liver damage. The most appropriate treatment is a standard regimen containing doxycycline.
© 2009, Author(s). This open-access article is available under the Creative Commons Attribution 4.0 (CC BY 4.0) International License (https://creativecommons.org/licenses/by/4.0/), which allows for unrestricted use, distribution, and reproduction in any medium, provided that the original work is properly cited.
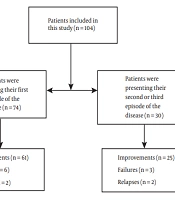
Keyvanfar A, Sali S, Zamani A. Epidemiology, Clinical and Laboratory Manifestations, and Outcomes of Brucellosis Among 104 Patients in Referral Hospitals of Tehran, Iran. Arch Clin Infect Dis. 2021;16(2):e111546. doi: https://doi.org/10.5812/archcid.111546

Hajia M, Rahbar M, Hossieni Taghavi A. Brucellosis Antibody Level of Hospitalized Patients in Hamadan, Western Iran. Shiraz E-Med J. 2007;8(3):. doi:

Ayazi P, Mahyar A, Rasoli A. Brucellosis in Children. J Compr Ped. 2012;3(1):12-15. doi: https://doi.org/10.17795/compreped-7079
Haratipour H, Sohrabi MB, Zolfaghari P, Enayatfard M. Breast Feeding Transmission of Brucellosis. Arch Clin Infect Dis. 2008;3(2):. doi:

Haddadi A, Rasoulinejad M, Afhami S, Mohraz M. Epidemiological, Clinical, Para clinical Aspects of Brucellosis in Imam Khomeini and Sina Hospital of Tehran (1998-2005). J Kermanshah Univ Med Sci. 2006;10(3):e81811. doi:
Last Update: 3 weeks ago
Last Update: 3 weeks ago
Last Update: 3 weeks ago
Last Update: 5 hours ago
Last Update: 1 day ago
Last Update: 4 days ago