Cover image of the article: Successful Conservative Management of Tracheal Injury After Forceful Coughing During Extubation: A Case Report

Image Credit:Anesth Pain Med

Successful Conservative Management of Tracheal Injury After Forceful Coughing During Extubation: A Case Report

Authors

Joo Hyeon Oh1, Sung Jun Hong1, Sang Soo Kang1, Sung Mi Hwang2,*
1Department of Anesthesiology and Pain Medicine, College of Medicine, Hallym University, Seoul, Korea
2Department of Anesthesiology and Pain Medicine, College of Medicine, Hallym University, Chuncheon, Korea
*Corresponding Author: Corresponding author: Sung Mi Hwang, Department of Anesthesiology and Pain Medicine, College of Medicine, Hallym University, Chuncheon, Korea. Tel: +82-332405155, Fax: +82-332510941, E-mail: Email: h70sm@hallym.or.kr

Anesthesiology and Pain Medicine:Vol. 6, issue 4; e39262
Published online:Jul 31, 2016
Article type:Case Report
Received:Jun 03, 2016
Accepted:Jul 18, 2016
How to Cite:Hyeon Oh J, Jun Hong S, Soo Kang S, Mi Hwang S. Successful Conservative Management of Tracheal Injury After Forceful Coughing During Extubation: A Case Report. Anesth Pain Med. 2016;6(4):e39262. doi: https://doi.org/10.5812/aapm.39262

Abstract

A-56-year-old woman underwent carpal tunnel release surgery under general anesthesia. Thirty minutes after extubation, the patient complained of chest discomfort with dyspnea. Swelling of the neck and upper anterior chest was observed. Computed tomography of the chest showed tracheal rupture at the brachiocephalic trunk level, and bronchoscopy demonstrated a 5 cm linear tracheal defect in the posterior membranous wall, 6 cm proximal to the carina. Surgical repair of the tracheal injury was impossible due to its location. The patient was managed with intubation, mechanical ventilator care, and antibiotics. She made a full and uncomplicated recovery and was discharged 18 days after the original injury. When suspicious symptoms appear in patients receiving mechanical ventilation support, an immediate and accurate diagnostic process should be undertaken to rule out endotracheal tube-related tracheal injuries and to avoid potentially lethal complications.

Highlights

1. Introduction

Tracheal injury is a rare and serious complication of endotracheal intubation. Tracheal perforation resulting from tracheal intubation causes pneumothorax and pneumomediastinum through high-volume air leakage, and may lead to mediastinitis and sepsis. As acute mediastinitis is a life-threatening condition if not diagnosed early and treated adequately, early diagnosis and treatment are critical. We report a case of pneumomediastinum occurring due to tracheal injury during general anesthesia with endotracheal intubation.

2. Case Presentation

A 56-year-old woman (height 146 cm, weight 74 kg) was scheduled to undergo carpal tunnel release surgery under general anesthesia. No other medical history or specific abnormal laboratory results were recorded except for the presence of arterial hypertension treated with valsartan 80 mg/day and hydrochlorothiazide 12.5 mg/day for approximately 3 months. Following induction of anesthesia with propofol 120 mg, a continuous infusion of remifentanil 10 μ10i, and fentanyl rocuronium 50 mg, the oral intubation was performed without difficulty using a 6.5 mm internal diameter (ID) high-volume/low-pressure cuffed endotracheal tube (MALLINCKRODT®, Covidien, USA) without a stylet. The cuff was inflated with 4 ml of air, but its pressure was not checked. Anesthesia was maintained with desflurane in air/O2 (FiO2 = 0.5) and remifentanil. The entire surgery lasted approximately 25 minutes. At the end of surgery, anesthesia was discontinued and the endotracheal tube was suctioned. While awakening, the patient coughed vigorously and made a violent neck movement. However, the extubated endotracheal tube was not tinged with blood. She was transferred to the post-anesthesia care unit (PACU). Thirty minutes after the extubation, the patient complained of chest discomfort with dyspnea. The anesthesiologist checked for swelling of the neck and upper anterior chest. The results of the arterial blood gasses were as follows: pH = 7.32, PCO2 = 51 mmHg, PO2 = 78 mmHg, HCO3 = 26.8 mmol/L, and SpO2 = 93%. The chest X-ray showed pneumomediastinum and subcutaneous emphysema (Figure 1), and a subsequent computed tomography (CT) scan showed a tracheal laceration at the brachiocephalic trunk level (Figure 2). The bronchoscopy demonstrated a 5 cm linear tracheal defect in the posterior membranous wall, 6 cm proximal to the carina (Figure 3). The thoracic surgeon’s opinion was that thoracic surgical repair of the tracheal tear was impossible due to its location. In the intensive care unit, a 7.5 mm ID cuffed endotracheal tube was al tube was acic surgical repair of the tracheal tear was imposly to the lesion as possible near the carina under bronchoscopy. Low-tidal-volume lung ventilation was applied to allow the lesion to recover without deteriorating the pneumomediastinum. A pressure-controlled mode was applied as follows: tidal volume of 250 - 350 ml/kg, frequency of 20 - 25/min, and pressure-limited ventilation (mean airway pressure < 25 cm H2O) with permissive hypercapnia. A course of broad-spectrum intravenous antibiotics was administered. The patient improved, and three days later, chest CT showed markedly reduced mediastinal and subcutaneous emphysema. After eight days, bronchoscopy showed that the lesion was healing. Endotracheal tube extubation was performed 13 days after the initial injury, and the patient was discharged in good condition 5 days later.
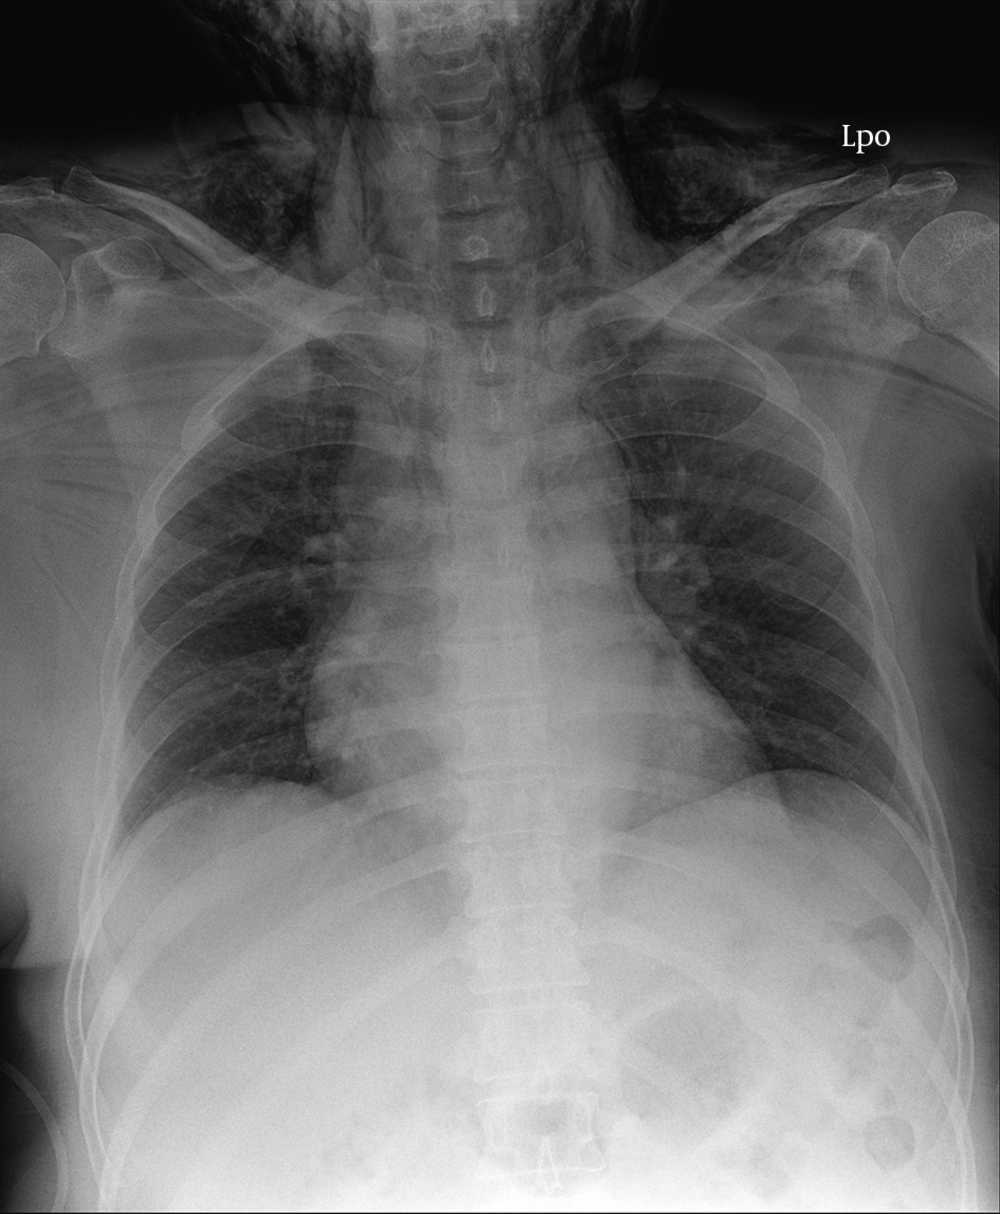
Chest X-ray PA View Showing Pneumomediastinum and Subcutaneous Emphysema in the Neck and Chest Wall
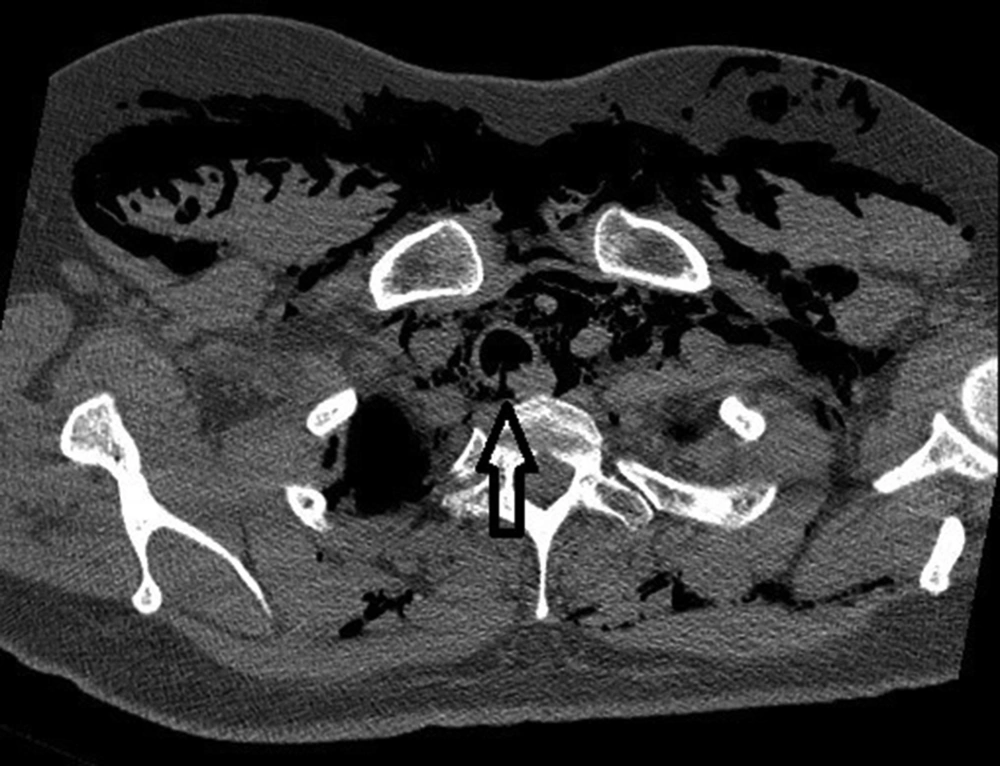
Figure 1.
Chest X-ray PA View Showing Pneumomediastinum and Subcutaneous Emphysema in the Neck and Chest Wall
Chest CT Showing Linear Tracheal Rupture in Posterior Wall (Arrow), Pneumomediastinum, and Subcutaneous Emphysema
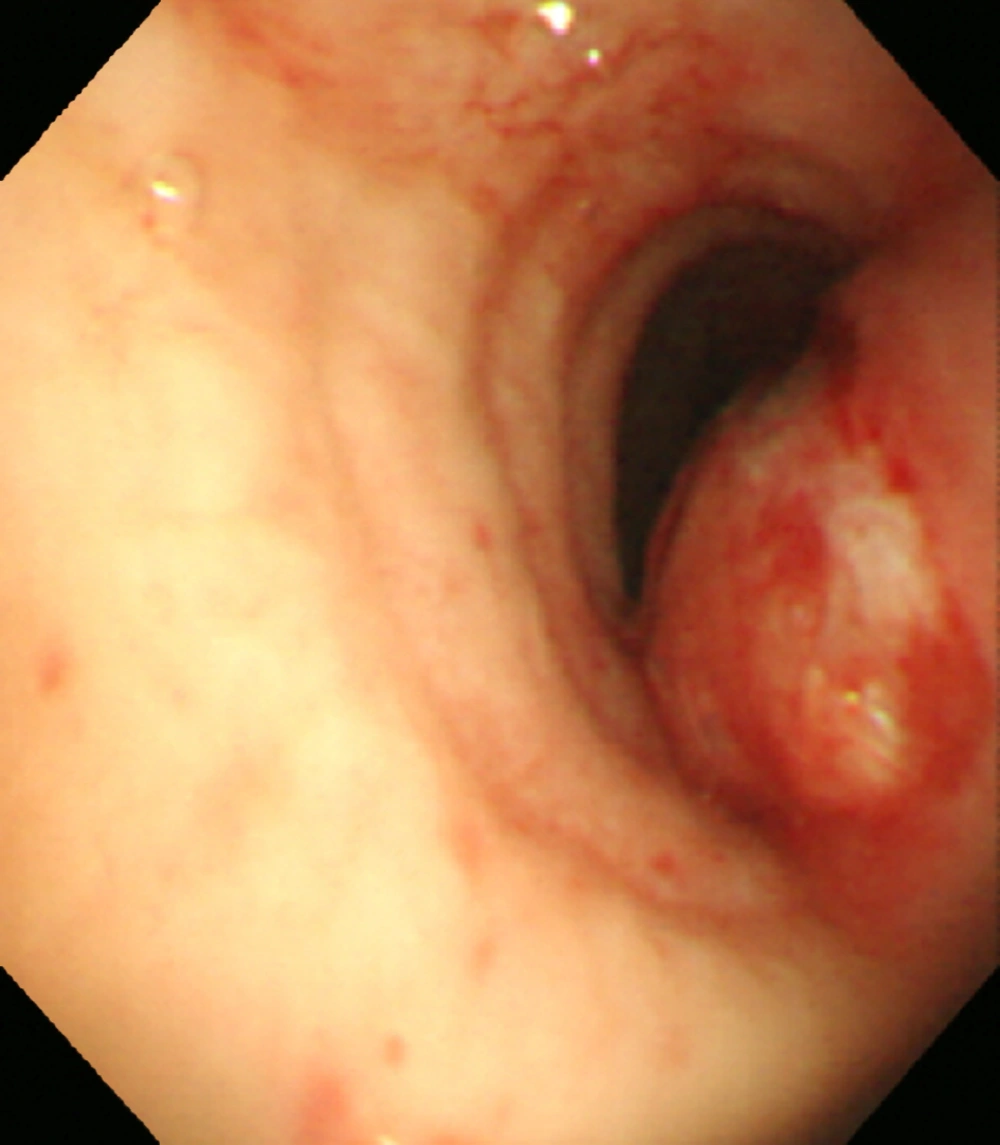
Figure 2.
Chest CT Showing Linear Tracheal Rupture in Posterior Wall (Arrow), Pneumomediastinum, and Subcutaneous Emphysema
Diagnostic Bronchoscopy Revealing a 5 cm Linear Laceration on the Posterior Membranous Wall
Figure 3.
Diagnostic Bronchoscopy Revealing a 5 cm Linear Laceration on the Posterior Membranous Wall

3. Discussion

Iatrogenic tracheal injury following intubation is extremely rare. For intubation with a patient was disendotracheal tube, the incidence ranges between 1:20,000 and 1:75,000, and the lesions are typically longitudinal lacerations of the posterior tracheal wall (pars membranosa) (1, 2). Tracheal injury occurs mainly in women, as their airways have a narrower diameter, their tracheas are shorter, and their pars membranosa is weaker than in men (3, 4). In addition, short stature and advanced age can be predisposing factors to tracheal injury (4, 5). In this case, the patient had sufficient predisposing factors, but we did not monitor the pressure of the endotracheal cuff.
The precise cause of post-intubation tracheal tears is unclear. However, over-inflation of the endotracheal tube cuff is the most common factor (4). Since st common cause of tracheal tearsff al tears is unclear. We did not monitor the pressure of l lacerations of the posterior tracheompletely eliminated. High-volume/low-pressure was applied in this case. Accidental cuff over-inflation with higher pressure is an obvious explanation, as relative over-inflation is possible if the cuff is filled just above the carina where the trachea has its largest diameter, and the tube is pulled back to its correct position (6). Although tracheal rupture may be caused by an injury from the stylet or tube tip (7), in this case, the stylet was not used and the airway was not difficult.
Generally, tube repositioning without cuff deflation causes mucosal injuries and intra-operative repositioning of the patientdeflation ina where the trachea hathe endotracheal tube and change the pressure of the cuff, and promote tracheal injuries (1, 8). The diffusion of anesthetic N2O gas into the cuff can also increase the pressure due to over-inflation (9). However, N2O was not administered in our case. We guessed that the over-inflation of the cuff made the tracheal wall weak, and sudden movement of the tube during the vigorous coughing caused the tracheal injury. The detection of a subcutaneous emphysema when the patient complained of dyspnea alerted us to the possibility of a tracheal rupture. In that event, pneumomediastinum and pneumothorax should be promptly excluded or diagnosed to accelerate the initiation of appropriate treatment (4).
A chest X-ray can show emphysema of the soft tissues, pneumomediastinum, pneumopericardium, and/or pneumothorax. A combination of chest CT and emergency bronchoscopy is recommended to diagnose a suspected tracheal injury. CT images show injuries of the posterior tracheal wall and pneumomediastinum; however, the tracheal injury site seen on CT does not always match bronchoscopy findings, and CT scans only have an 85% sensitivity for the detection of tracheal injury (10). Therefore, diagnostic bronchoscopy is mandatory to establish a diagnosis and to determine the type and extent of the laceration.
No consensus regarding treatment has yet been established. Early surgical repair has been the traditional treatment mainstay. However, over the past 20 years, non-operative management of tracheal injury has been recommended for selected patients in the following circumstances: stable vital signs, easy achievement of adequate functional respiratory status under mechanical or spontaneous ventilation, absence of esophageal injury, minimal mediastinal fluid collection, non-progressive pneumomediastinum or subcutaneous emphysema, absence of sepsis, short ruptures, and delayed diagnosis (2, 4, 11). In the largest case series report, the conservative approach to post-intubation tracheal rupture was independent of the length of the defect (2). Considerations for surgical repair were the rapid progression of air leaks, mediastinitis, and ventilatory deterioration (12). Conservative treatment consists of positioning the tracheal tube cuff distally to the lesion, i.e., a bridging maneuver (in order to keep the lesion under zero pressure and to prevent widening of the injury during inspiration), broad-spectrum antibiotics, and cough suppression (13). When treated optimally and avoiding steroid use, immunosuppression, and malnutrition, complete recovery can be achieved within one month (14).
In summary, we presumed that the tracheal injuries in our case were caused by the sudden movement of the over-inflated endotracheal tube cuff from the patient’s vigorous coughing while emerging from anesthesia. This can occur in any patient receiving mechanical ventilatory support, and even , and even t receiving mechanical ventilatory support, and even ede iesion, i.e., a monitoring of the cuff pressure during general anesthesia is necessary, and minimizing movement of the head and neck at emergence is important in order to avoid tracheal injury. If any suspicious symptoms appear, an immediate and accurate diagnostic process should be performed to rule out the risk of tracheal injury.


Footnotes

  • Authors’ Contribution:Sung Mi Hwang: acquisition of data; Joo Hyeon Oh: drafting of the manuscript; Sung Jun Hong and Sang Soo Kang: critical revision of the manuscript for important intellectual content, study supervision.

References

  • 1.
    Lampl L. Tracheobronchial injuries. Conservative treatment. Interact Cardiovasc Thorac Surg. 2004;3(2):401-5. [PubMed ID: 17670273]. https://doi.org/10.1016/j.icvts.2004.02.016.
  • 2.
    Conti M, Pougeoise M, Wurtz A, Porte H, Fourrier F, Ramon P, et al. Management of postintubation tracheobronchial ruptures. Chest. 2006;130(2):412-8. [PubMed ID: 16899839]. https://doi.org/10.1378/chest.130.2.412.
  • 3.
    Cardillo G, Carbone L, Carleo F, Batzella S, Jacono RD, Lucantoni G, et al. Tracheal lacerations after endotracheal intubation: a proposed morphological classification to guide non-surgical treatment. Eur J Cardiothorac Surg. 2010;37(3):581-7. [PubMed ID: 19748275]. https://doi.org/10.1016/j.ejcts.2009.07.034.
  • 4.
    Minambres E, Buron J, Ballesteros MA, Llorca J, Munoz P, Gonzalez-Castro A. Tracheal rupture after endotracheal intubation: a literature systematic review. Eur J Cardiothorac Surg. 2009;35(6):1056-62. [PubMed ID: 19369087]. https://doi.org/10.1016/j.ejcts.2009.01.053.
  • 5.
    Chen EH, Logman ZM, Glass PS, Bilfinger TV. A case of tracheal injury after emergent endotracheal intubation: a review of the literature and causalities. Anesth Analg. 2001;93(5):1270-1. table of contents. [PubMed ID: 11682412].
  • 6.
    Striebel HW, Pinkwart LU, Karavias T. [Tracheal rupture caused by overinflation of endotracheal tube cuff]. Anaesthesist. 1995;44(3):186-8. [PubMed ID: 7762778].
  • 7.
    Kim YS, Han I, Ahn JK. Pneumothorax and Pneumomediastinum Occurred after Esophageal Perforation by a Stylet during Difficult Endotracheal Intubation. Korean J Anesthesiol. 2001;40(4):546. https://doi.org/10.4097/kjae.2001.40.4.546.
  • 8.
    Liu J, Zhang X, Gong W, Li S, Wang F, Fu S, et al. Correlations between controlled endotracheal tube cuff pressure and postprocedural complications: a multicenter study. Anesth Analg. 2010;111(5):1133-7. [PubMed ID: 20736432]. https://doi.org/10.1213/ANE.0b013e3181f2ecc7.
  • 9.
    Massard G, Rouge C, Dabbagh A, Kessler R, Hentz JG, Roeslin N, et al. Tracheobronchial lacerations after intubation and tracheostomy. Ann Thorac Surg. 1996;61(5):1483-7. [PubMed ID: 8633963].
  • 10.
    Tu HN, Saidi N, Leiutaud T, Bensaid S, Menival V, Duvaldestin P. Nitrous oxide increases endotracheal cuff pressure and the incidence of tracheal lesions in anesthetized patients. Anesth Analg. 1999;89(1):187-90. [PubMed ID: 10389801].
  • 11.
    Chen JD, Shanmuganathan K, Mirvis SE, Killeen KL, Dutton RP. Using CT to diagnose tracheal rupture. AJR Am J Roentgenol. 2001;176(5):1273-80. [PubMed ID: 11312194]. https://doi.org/10.2214/ajr.176.5.1761273.
  • 12.
    Gomez-Caro Andres A, Moradiellos Diez FJ, Ausin Herrero P, Diaz-Hellin Gude V, Larru Cabrero E, de Miguel Porch E, et al. Successful conservative management in iatrogenic tracheobronchial injury. Ann Thorac Surg. 2005;79(6):1872-8. [PubMed ID: 15919275]. https://doi.org/10.1016/j.athoracsur.2004.10.006.
  • 13.
    Schneider T, Storz K, Dienemann H, Hoffmann H. Management of iatrogenic tracheobronchial injuries: a retrospective analysis of 29 cases. Ann Thorac Surg. 2007;83(6):1960-4. [PubMed ID: 17532378]. https://doi.org/10.1016/j.athoracsur.2007.01.042.
  • 14.
    Fong PA, Seder CW, Chmielewski GW, Welsh RJ. Nonoperative management of postintubation tracheal injuries. Ann Thorac Surg. 2010;89(4):1265-6. [PubMed ID: 20338349]. https://doi.org/10.1016/j.athoracsur.2009.07.093.

Copyright

Copyright © 2016, Iranian Society of Regional Anesthesia and Pain Medicine (ISRAPM). This is an open-access article distributed under the terms of the Creative Commons Attribution-NonCommercial 4.0 International License (http://creativecommons.org/licenses/by-nc/4.0/) which permits copy and redistribute the material just in noncommercial usages, provided the original work is properly cited.

Similar Articles

25
Feb
2014
A Case of Death Caused by Tracheal Tube Aspiration

A Case of Death Caused by Tracheal Tube Aspiration

Alireza Mirkheshti,
Morteza Jabbary Moghadam,
Mohamad Shahab Kalantar,
Dariush Abtahi,
Elham Memary

Mirkheshti A, Jabbary Moghadam M, Kalantar MS, Abtahi D, Memary E. A Case of Death Caused by Tracheal Tube Aspiration. Anesth Pain Med. 2014;4(1):e13152. doi: https://doi.org/10.5812/aapm.13152

5
Jul
2020
Emergency Tracheostomy in Two Airway Trauma Patients Suspected of COVID-19: A Case Report

Emergency Tracheostomy in Two Airway Trauma Patients Suspected of COVID-19: A Case Report

Valiollah Hassani,
Saied Amniati,
Aslan Ahmadi,
Masood Mohseni,
Saloome Sehat-Kashani,
Nasim Nikoubakht
,et al.

Hassani V, Amniati S, Ahmadi A, Mohseni M, Sehat-Kashani S, et al. Emergency Tracheostomy in Two Airway Trauma Patients Suspected of COVID-19: A Case Report. Anesth Pain Med. 2020;10(4):e104648. doi: https://doi.org/10.5812/aapm.104648

10
Sep
2014
Use of two Endotracheal Tubes to Perform Lung Isolation and One-Lung Ventilation in a Patient With Tracheostomy Stenosis: A Case Report

Use of two Endotracheal Tubes to Perform Lung Isolation and One-Lung Ventilation in a Patient With Tracheostomy Stenosis: A Case Report

Mehryar Taghavi Gilani,
Mehdi Fathi,
Majid Razavi

Taghavi Gilani M, Fathi M, Razavi M. Use of two Endotracheal Tubes to Perform Lung Isolation and One-Lung Ventilation in a Patient With Tracheostomy Stenosis: A Case Report. Anesth Pain Med. 2014;4(4):e18280. doi: https://doi.org/10.5812/aap.18280

16
Apr
2016
Severe Respiratory Event Initially Thought to be Inadvertent Endobronchial Intubation: Possible Complications From Using of a Topical Metered-Dose of 8% Lidocaine Pump Spray

Severe Respiratory Event Initially Thought to be Inadvertent Endobronchial Intubation: Possible Complications From Using of a Topical Metered-Dose of 8% Lidocaine Pump Spray

Young-Chang P. Arai,
Jun Kawanishi,
Yoshikazu Sakakima,
Koichi Ohmoto,
Akihiro Ito,
Yuki Maruyama
,et al.

Arai YP, Kawanishi J, Sakakima Y, Ohmoto K, Ito A, et al. Severe Respiratory Event Initially Thought to be Inadvertent Endobronchial Intubation: Possible Complications From Using of a Topical Metered-Dose of 8% Lidocaine Pump Spray. Anesth Pain Med. 2016;6(3):e33771. doi: https://doi.org/10.5812/aapm.33771

1
Jan
2011
Laryngospasm Induced Pulmonary Edema: A Case Report.

Laryngospasm Induced Pulmonary Edema: A Case Report.

M Jafari Javid

Jafari Javid M. Laryngospasm Induced Pulmonary Edema: A Case Report.. Shiraz E-Med J. 2011;12(1):. doi:

More by these authors

Joo Hyeon OhPubMedScholar
Sung Jun HongPubMedScholar
Sang Soo KangPubMedScholar
Sung Mi HwangPubMedScholar
Share
Cited by
Metrics