1. Background
Nonalcoholic steatohepatitis (NASH) is a progressive form of non-alcoholic fatty liver disease (NAFLD). The pathogenesis of NASH is multifactorial, indicating a significant association with inflammation. In its severe form, NASH can lead to cirrhosis, with permanent liver damage (1, 2). Patients with NASH show significantly higher serum levels of tumor necrosis factor-alpha (TNF-α) and interleukin-6 (IL-6), compared with patients with simple steatosis (3). Tumor necrosis factor-alpha is produced by several types of inflammatory cells and tissues, such as monocytes, macrophages, neutrophils, endothelial cells, neuronal tissue, T cells, hepatocytes, and Kupffer cells (4). The TNF-α is significantly involved in the development of NASH and NAFLD in animal models and humans (5-8). Interleukin-6 plays a pivotal role in liver pathology and synthesis of acute phase proteins, such as C-reactive protein and serum amyloid A (9). Several reports have shown a confounding influence of IL-6 on NASH. On one hand, IL-6 can improve liver regeneration in IL-6 knockout mice with diet-induced NASH and, on the other hand, it can promote hepatocyte apoptosis in patients with NASH (10-12). Interleukin 8 (IL-8) is produced by peripheral blood mononuclear cells, macrophages, and infiltrated lymphocytes. Jarrar et al. (13) reported that IL-8, alanine aminotransferase (ALT), age, and adiponectin were independently associated with NASH. Pentoxifylline (PTX) is a methylxanthine derivative and an anti‒TNF-α agent, which is reportedLy administered for the treatment of NASH. It can decrease the production of several pro-inflammatory cytokines, including TNF-α and shows anti-inflammatory properties, through the inhibition of nuclear factor-kappa B (NF-κB) (14-16). The results of several studies, involving the use of PTX in patients with NASH, have shown the effect of PTX in NASH. Published studies have several limitations, due to variation in characterization of patients, such as those with biopsy-proven NASH or NASH based on sonography and ALT and aspartate transaminase (AST) levels. Differences in study designs, such as prospective cohort studies, with control group, or randomized and controlled trials and, also, difference in sample size are other reasons for different findings of studies on the effects of PTX, in patients with NASH (17-24).
2. Objectives
The primary aim of this study was to evaluate the effectiveness of PTX for 6 months, in a randomized, double-blind, placebo-controlled clinical trial, in patients with NASH, in the city of Kerman, in South-Eastern Iran. The other aims were to assess the effect of PTX on the serum levels of ALT, AST, TNF-α, IL-8, and IL-6 in patients with NASH.
3. Patients and Methods
3.1. Characterization of Patients
Thirty patients with NASH were recruited at the Kerman University of Medical Sciences, Besat Clinic, Kerman, South-Eastern Iran. Written informed consent was obtained from each participant in the study and the study protocol conforms to the ethical guidelines of the 1975 declaration of Helsinki. The approval number for the ethics committee was K/91/331. Patients were considered for the study if they had a diagnosis of NASH, based on sonography, and a 1.5-fold mean change from baseline of AST and ALT levels. Patients were excluded if they had a past history of excessive alcohol consumption or any cigarette smoking or narcotics use. Patients were also excluded if they had diabetes and hyperlipidemias. Patients with hypertension (≥ 140/90 mmHg) and those who tested positive for hepatitis C virus or hepatitis B virus infection were also excluded. Additionally, patients were excluded if they had high serum levels of alpha-1-antitrypsin, ceruloplasmin, anti-smooth muscle antibody, and antinuclear antibody. Patients were also excluded if they were taking anti-hypertensive, anti-hyperlipidemic, anti-hyperglycemic medications, or amiodarone or oral contraceptive pills. Patients who were suffering from acute or chronic liver disease were excluded before and during the intervention.
3.2. Study Design and Staging
The study was designed as a randomized, double-blind, placebo-controlled trial. The study protocol was approved by the ethics committee of Kerman University of Medical Sciences, Kerman, Iran.
Registration ID in Iranian Registry of Clinical Trials (IRCT) was IRCT2015033021565N1. Patient enrollment occurred between October 2012 and September 2013. Double blinding was maintained throughout the duration of the randomization phase. The trial was completed in March 2014. The study was designed for 30 patients; 15 patients (frequency: male = 80%, female = 20%, age = 35.7 ± 6.6 years) in the intervention group, who received a PTX dose of 400 mg thrice a day, for 6 months, and 15 patients (male = 80%, female = 20%, age = 39.4 ± 9.4 years) in the placebo group, who received a placebo for 6 months. All patients attended the Gastroenterology Clinic, at Afzalipour Hospital, and were given advice concerning low calorie diet and the importance of daily exercise by a resident in gastroenterology. There were no differences with regard to shape, taste, and color between the placebo and PTX.
The placebo and PTX were labeled by an unblinded pharmacist, as A and B, respectively, before random allocation to the patient. Patients, the medical examiner, laboratory and pharmacy staff did not know the nature of the drugs. On completion of data collection, statistical analysis was performed by a statistician who was unaware of the nature of the compounds represented by A and B. Fifteen untreated healthy subjects were enrolled to determine the serum levels of cytokines, to present a cut-off point when comparing with that of the patients. Demographic data for the 15 controls were as follows: males = 36%, females = 64%. The mean age for control group was (37.37 ± 12.5). The healthy controls, selected from Kerman Blood Transfusion Centre, Kerman, Iran, had no history of systemic or organ specific autoimmune diseases, allergy, infectious diseases, cancer, and metabolic disorders. Laboratory studies were performed to measure levels of AST and ALT, in patients with NASH, at the baseline, 3 months, and 6 months. The serum levels of IL-6, IL-8, and TNF-α were also measured in patients at baseline and 6 months. Weight and height of the patients were measured, to determine body mass index (BMI) at baseline and during the clinical trial at 3 and 6 months. The height of placebo and intervention groups at baseline, 3 months and 6 months was 171.2 ± 9.8 and 172.8 ± 7.2, respectively. The weight of the placebo group at baseline, 3 months and 6 months was 82.2 ± 13, 80.2 ± 13 and 77.7 ± 13.1 kg, respectively, and the weight of the intervention group at baseline, 3 months and 6 months was 80.8 ±12.5, 78.2 ± 13.1 and 73.9 ± 12.7 kg, respectively. The patients were counseled about following a healthy diet and exercise plan. Sampling lasted 6 months. During this period, five patients in the intervention group stopped treatment, four of which because of adverse effects and one for personal reasons. Nine patients in the placebo group stopped treatment, five of which because of problems similar to adverse effects of PTX and four for personal reasons.
3.3. Assessment of Liver Aminotransferases and Serum Cytokines
Liver aminotransferases, including ALT and AST, were measured for patients with NASH by enzymatic photometry. Serum levels of IL-6, IL-8, and TNF-α were determined for patients with NASH and healthy controls by an enzyme-linked immunosorbent assay (ELISA) technique, according to the manufacturer’s instructions (Bosterbio, Pleasanton, CA, USA).
3.4. Sample Size Calculation
According to the previous study (18), by considering alpha error of 5% and the power of 90% and also employing the formula for two-sample comparison of means, the sample size was calculated to be nine, for each group. We entered 15 patients in each group to enhance the statistical power of study.
3.5. Statistics
Statistical analyses, such as descriptive statistics, repeated measurement test, one-way ANOVA, and independent t-test were performed by SPSS software version 17.0 (SPSS Inc., Chicago, IL, USA). A P < 0.05 was considered for statistical significant.
4. Results
The mean ages of the patients in the intervention and placebo groups were 35.7 and 39.4 years, respectively. The difference between the two groups, concerning age, was insignificant (P = 0.220). The means of BMI in the intervention and placebo groups were 26.9 and 26.6, respectively, and the difference was statistically insignificant (P = 0.912). Data regarding laboratory parameters and ultrasonography of the liver, for patients with NASH are presented in Table 1.
Table 1.
Comparison of Laboratory Parameters and Ultrasonography of the Liver Between the Intervention and Placebo Groups at Baseline
| Parameters | Intervention Group | Placebo Group | P |
|---|---|---|---|
| Laboratory tests for patients with NASH before starting the treatment | |||
| Alkaline phosphatase, U/L | 218.06 ± 72 83 | 239.60 ± 95.18 | 0.492 |
| Triglyceride, mg/dL | 175.78 ± 65.18 | 142.33 ± 41.18 | 0.108 |
| Low density lipoprotein, mg/dL | 28.70 ± 109.17 | 106.22 ± 24.20 | 0.767 |
| High density lipoprotein, mg/dL | 39.64 ± 13.18 | 42.13 ± 12.50 | 0.606 |
| Fasting blood sugar, mmol/L | 93.42 ± 8.79 | 96.13 ± 20.19 | 0.648 |
| Cholesterol, mg/dL | 174.57 ± 26.93 | 173.93 ± 26.10 | 0.582 |
| Ultrasonography of the liver | 0.014 | ||
| Fatty liver, mild | 2 a | 9 a | |
| Fatty liver, moderate | 12a | 6a |
aPositive results.
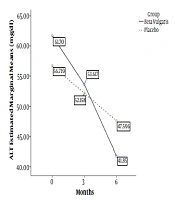
The levels of AST and ALT, measured at the baseline, 3 and 6 months, are presented in Table 2. Results in Table 2 were presented after repeated measure ANOVA with Greenhouse-Geisser correction. Post-hoc tests were performed to obtain mean studied parameters between time points and results were statistically significant after Bonferroni correction.
Table 2.
Comparison of Liver Aminotransferases and Body Mass Index at Different Time Points Between the Intervention and Placebo Groupsa
| Parametersb | Baseline | 3 Months | 6 Months | P |
|---|---|---|---|---|
| ALT, U/L | ||||
| Intervention group | 85.5 ± 38.8c | 49.0 ± 19.4d | 37.0 ± 12.6 | 0.000 |
| Placebo | 80.5 ± 31.2c | 56.9 ± 34.3 | 46.5 ± 27.7 | 0.001 |
| AST, U/L | ||||
| Intervention group | 60.0 ± 27.5c | 38.2 ± 17.3d | 27.3 ± 9.3 | 0.001 |
| Placebo | 51.1 ± 13.6c | 37.2 ± 12.4 | 34.8 ± 15.8 | 0.001 |
| BMI, kg/m2 | ||||
| Intervention group | 26.9 ± 3.1e | 26.1 ± 3.3d | 25.7 ± 3.4 | 0.000 |
| Placebo | 26.6 ± 7.8c | 27.6 ± 3.8d | 27.2 ± 3.7 | 0.000 |
aAbbreviations: ALT, alanine transaminase; AST, aspartate transaminase; BMI, body mass index.
bN = 15.
cSignificant difference was detected from comparison between the baseline and 3 months and also between the baseline and 6 months.
dSignificant difference was detected from comparison between 3 and 6 months.
eSignificant difference was detected from comparison between baseline and 6 months.
There was no significant difference with regard to the serum level of ALT, between the placebo and intervention groups, at baseline (P = 0.217), at 3 months (P = 0.446) or at 6 months (P = 0.236). Similarly, no significant difference was observed in the serum level of AST between the groups, at baseline (P = 0.701), at 3 months (P = 0.857) or at 6 months (P = 0.125).
The BMIs obtained at baseline, 3 and 6 months, are presented in Table 2. There was no significant difference in term of BMI between the groups, at baseline (P = 0.912), at 3 months (P = 0.346), and at 6 months (P = 0.391).
The serum levels of IL-6, IL-8, and TNF-α, as mean ± SD, in healthy controls, were 6.3 ± 3.9, 18.0 ± 7.5, and 16.8 ± 11.3 pg/mL, respectively. Levels of these cytokines were significantly higher in patients with NASH, compared with healthy controls. Serum levels of these cytokines were unchanged between baseline and 6 months in the intervention and placebo groups, with the exception of IL-8, where a statistically lower level in the intervention group at baseline had increased at 6 months (Table 3).
Table 3.
Comparison Between Serum Levels of Cytokines (IL-6, IL-8, and TNF-α) in the Intervention and Placebo Groups and Also Within the Groups at Different Time Pointsa
| Parametersb | Serum Levels of Cytokines, pg/mL | ||
|---|---|---|---|
| Baseline | 6 Months | P Value | |
| IL-6 | |||
| Intervention group | 34.4 ± 26.5 | 24.7 ± 22.7 | 0.009 |
| Placebo | 33.5 ± 20.2 | 21.2 ± 15.4 | 0.045 |
| P Value | 0.916 | 0.63 | |
| IL-8 | |||
| Intervention group | 36.1 ± 10.2 | 48.2 ± 19.7 | 0.478 |
| Placebo | 46.6 ± 16.8 | 49.8 ± 13.1 | 0.585 |
| P Value | 0.048 | 0.789 | |
| TNF-α | |||
| Intervention group | 39.2 ± 23.2 | 35.1 ± 23.1 | 0.028 |
| Placebo | 42.0 ± 27.3 | 31.1 ± 21.2 | 0.174 |
| P Value | 0.763 | 0.626 | |
aAbbreviations: IL-6, Interleukin 6; IL-8, Interleukin 8; TNF‒α, tumor necrosis factor α.
bN = 15.
5. Discussion
Most clinical trials on the effect of PTX in patients with NASH have sufficed to compare the cytokine levels in the intervention and placebo groups, without including the healthy controls. In the present study, patients with NASH had significantly higher serum levels of IL-6, IL-8, and TNF-α, as compared to healthy individuals, which confirmed the important role of inflammation in the pathogenesis and progression of NASH (11, 12). In the present study, PTX decreased the serum levels of liver transferases in patients with NASH, without any significant differences between the intervention and placebo groups. The results of a study by Van Wagner et al. which measured and compared the serum levels of ALT, AST, TNF-α, and IL-6, in patients with NASH during 12 months, shows that their intervention versus placebo clinical trial is in accordance with our findings (25). Lee et al. reported serum levels of liver transferases, as well as serum levels of TNF-α and IL-6 in patients with NASH, which were decreased in intervention and placebo groups in a 3-month, randomized, double-blind, placebo-controlled trial (17). They recommended daily exercise and a low-calorie diet to both the groups and reported no significant difference between the groups, with regard to the serum levels of TNF-α, IL-6, AST, and ALT at the end of the clinical trial. Their results are also in agreement with our findings. However, our findings are in disagreement with the results of another randomized, double-blind, placebo-controlled trial, which was performed by Buranawui et al. on 32 patients with NASH (26). They reported a significant decrease of ALT and AST in the intervention group, as compared to that in the placebo group. They also stated no significant differences in TNF-α and BMI between the groups, at the end of a 6-month clinical trial, which is in agreement with our findings. Our results are in disagreement with the findings of Zein et al., who showed that liver fibrosis and the histological features of NASH could be improved by PTX administration for one year (27).
Georgescu EF and Georgescu M carried out a non-randomized and uncontrolled prospective study on an outpatient database to determine the efficiency of several agents, including PTX, for the treatment of NASH (19). The BMI, serum levels of ALT, glutamyl transpeptidase, alkaline phosphatase, total cholestrol, triglycerides and liver biopsies were determined at baseline and at the end of the treatment. They concluded that PTX showed efficacy in treating non-hypertensive/non-dyslipidemic patients with NASH. However, this study did not control for the confounding effect of dietary and lifestyle interventions.
Li et al. performed a systematic review on the treatment with PTX in patients with NASH until June 2010 (28). They extracted their results from six studies, including two randomized, double-blind, placebo-controlled trials and four prospective cohort studies. They showed that the serum levels of AST and ALT were significantly decreased in PTX-treated patients. However, there were no significant differences between the serum levels of IL-6 and TNF-α, in the intervention group, as compared to that in the placebo group. They have suggested performing more well-designed, randomized, controlled clinical trials, with a larger sample size, as well as more prospective observational studies, to investigate the effect of PTX in reducing levels of cytokines.
A meta-analysis was recently performed by Du et al., on the effect of PTX in patients with NAFLD (29). They reviewed all relevant controlled trials of the effect of PTX in patients with NAFLD/NASH from 1997 to July 2013. Two prospective cohort studies with controls and three randomized, double-blind, placebo-controlled trials were included in their meta-analysis. Their findings indicated that PTX administration results in improved liver function and histological changes, as well as weight loss, in patients with NAFLD/NASH. They suggested that PTX may be a novel optional therapy for NAFLD. One study, which was included in their meta-analysis, had a limitation, as the researchers ignored to evaluate the influence of exercise and a low-calorie diet in PTX-treated patients with NASH. The small sample size of several trials and low number of trials were other limitations of the meta-analysis.
Jamali et al. recently performed a clinical trial to evaluate the effect of PTX on liver aminotransferases, in patients with NAFLD (30). They divided 120 patients to two groups and administered PTX to intervention arm. They measured liver aminotransferases at 2 months and 6 months. Although the levels of liver aminotransferases were reduced during the trial in intervention and control groups, their results did not show significant differences between the groups, which are in agreement with our results.
The lack of biopsies from the liver of patients with NASH, as a gold standard confirmation method, was a limitation in our study. Satapathy et al. showed that five out of six patients with NASH improved histologically and with improved liver aminotransferases, particularly ALT, after 12 months of PTX (21). Therefore, they suggested that measurement of liver transferases can be an acceptable criterion for evaluating patients with NASH.
In general, our results suggest that PTX administration does not significantly help in the treatment of patients with NASH. However, other studies show different results and it might be premature to draw conclusions about the efficacy of PTX in the treatment of NASH. Hence, we suggest that a further randomized, double-blind, placebo-controlled trial should be performed, with the enrolment of more patients with NASH from different races, to confirm the effect of PTX on liver aminotransferases, histological findings, and inflammatory cytokines, in patients with NASH. Longer duration and follow up are suggested too. Employment of modern techniques, such as microarray to evaluate and define more inflammatory cytokines genes, which are potentially involved in NASH, may help scientists and clinicians to address the efficacy of PTX therapy on inflammation in the future.