
Cover image of the article: Fasciola Hepatica in Explanted Cirrhotic Liver of a Patient with Chronic Hepatitis B Virus Infection: An Accidental Finding

Image Credit:Hepat Mon

Fasciola Hepatica in Explanted Cirrhotic Liver of a Patient with Chronic Hepatitis B Virus Infection: An Accidental Finding

Authors

Elham NazarElham Nazar ORCID1, Farid Azmoudeh-ArdalanFarid Azmoudeh-Ardalan ORCID2,*, Iraj Mobedi3, Seyed Habiballah Dashti4, Faeze SalahshourFaeze Salahshour ORCID5, Zahra AhmadinejadZahra Ahmadinejad ORCID6
1Department of Pathology, Cancer Institute, Tehran University of Medical Sciences, Tehran, Iran
2Liver Transplantation Research Center, Department of Pathology, Tehran University of Medical Sciences, Tehran, Iran
3Department of Parasitology, Tehran University of Medical Sciences, Tehran, Iran
4Department of Surgery, Tehran University of Medical Sciences, Tehran, Iran
5Department of Radiology, Tehran University of Medical Sciences, Tehran, Iran
6Department of Infectious Disease, Tehran University of Medical Sciences, Tehran, Iran
*Corresponding Author: Corresponding author: Farid Azmoudeh-Ardalan, Liver Transplantation Research Center, Department of pathology, Tehran University of Medical Sciences, Tehran, Iran. E-mail: Email: azmoudeh@sina.tums.ac.ir

Hepatitis Monthly:Vol. 17, issue 11; e61214
Published online:Oct 28, 2017
Article type:Case Report
Received:Sep 25, 2016
Accepted:Oct 08, 2017
How to Cite:Nazar E, Azmoudeh-Ardalan F, Mobedi I, Dashti SH, Salahshour F, et al. Fasciola Hepatica in Explanted Cirrhotic Liver of a Patient with Chronic Hepatitis B Virus Infection: An Accidental Finding. Hepat Mon. 2017;17(11):e61214. doi: https://doi.org/10.5812/hepatmon.61214

Abstract

Introduction:

Fasciola hepatica infection is frequently asymptomatic and may be neglected. However, severe conditions may be symptomatic due to stimulatory effects of the liver fluke in the liver.

Case Presentation:

The present report describes a rare case of fascioliasis accidentally discovered in the explanted liver of a patient with cirrhosis due to chronic hepatitis B virus (HBV) infection.

Conclusions:

Liver fluke infection may occur in cirrhotic livers. Thus, minute evaluation of liver explants for possible parasitic infestations including F. hepatica is suggested, particularly in endemic areas.

Highlights

1. Introduction

Fascioliasis caused by the liver fluke Fasciola hepatica is an important primary veterinary disorder as well as a human secondary disease (1). This flat-worm trematode enters the human body through digestive tract and lives in the common and hepatic bile ducts (2). The public health importance of human fascioliasis is now increasing due to its global spread as well as appearance of its considerable complications. Early infection with F. hepatica is frequently asymptomatic and may be neglected; however, in more severe conditions, stimulatory effects of the liver fluke can lead to proliferation and inflammation of biliary tracts and subsequently to hepatic fibrosis, biliary tract obstruction, cholangiocarcinoma, and even hepatocellular carcinoma (3). Furthermore, hepatic tissue damage as well as cirrhosis may appear as a result of hepatic cells injury (4). The present report describes a rare case of fascioliasis accidentally discovered in the explanted liver of a patient with cirrhosis due to chronic hepatitis B virus (HBV) infection.

2. Case Presentation

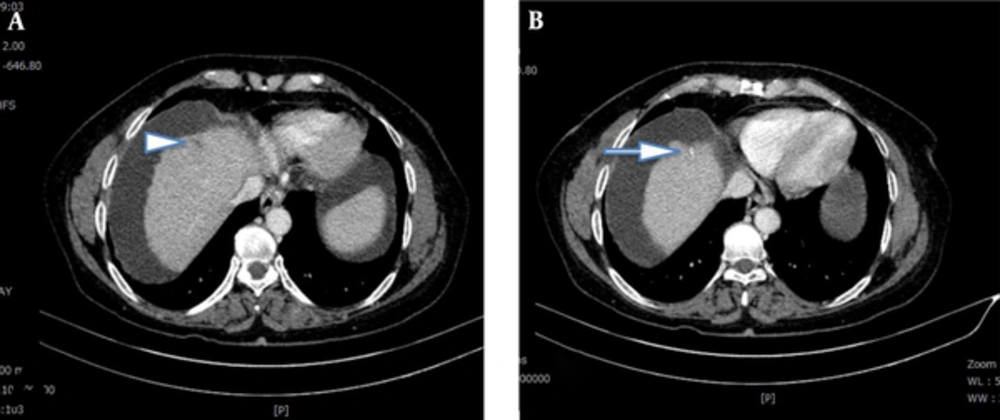
A 58-year-old female with diagnosis of cirrhosis in the background of chronic HBV infection was referred to Imam Khomeini Hospital Complex for orthotopic liver transplantation. Initial laboratory assessment showed a marked increase in alkaline phosphatase (ALP) as well as increased serum total and direct bilirubin level along with slightly elevated alanine aminotransferase (ALT) (aspartate aminotransferase (AST): 33 IU/mL, ALT: 84 IU/mL, ALP: 565 IU/mL, total bilirubin: 3.7 mg/dL, direct bilirubin: 2 mg/dL) and MELD (the model of end-stage liver disease) score of 17. Pre-transplantation evaluations showed a mass (suspected of hemangioma) in segment 4b and a fibrocalcified focus in segment 4a without other remarkable findings (Figure 1). Therefore, the patient underwent orthotopic liver transplantation. The histopathological assessment of explanted liver indicated active cirrhosis with large cell changes in some nodules. Further assessment revealed a necrotic hyalinized nodule harboring non-viable parasite in the peripheral regions of segment 4a (Figure 2). Also, small bile duct hamartoma was identified in a microscopic focus in segment 4a. A hemangioma measuring 1 cm was also found in segment 4b. The extrahepatic biliary tracts were unremarkable. No evidence of malignant change was detected. A demised degenerated worm that was morphologically consistent with F. hepatica was identified in the necrotic hyalinized nodule (Figure 2A and B). Eggs of this parasite were also found in the surrounding tissue (Figure 3). Follow-up of the patient showed good recovery after treatment with triclabendazole. The patient is alive and healthy without any major problems 2 years after transplantation.
CT Scan of Liver Reveals (A) a Small Linear Subcapsular Hypodense Lesion (Arrowhead) (B) Associated with Adjacent Linear Calcification (Arrow)
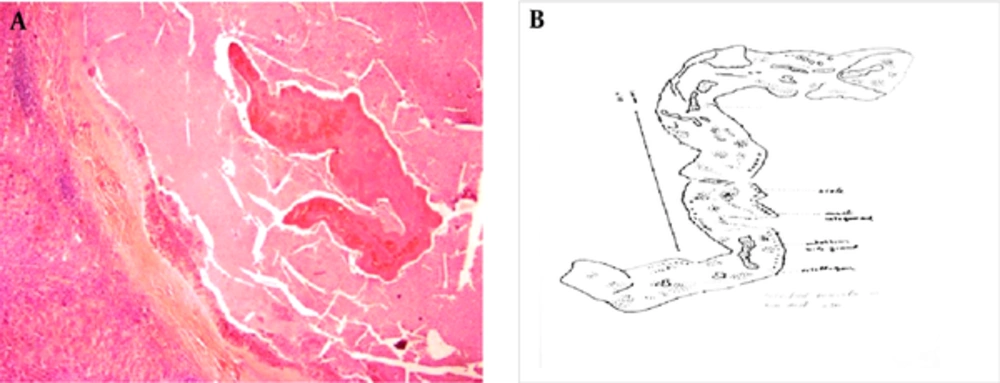
Figure 1.
CT Scan of Liver Reveals (A) a Small Linear Subcapsular Hypodense Lesion (Arrowhead) (B) Associated with Adjacent Linear Calcification (Arrow)
A, Demised fluke is evident in the necrotic background, separated by dense fibrotic tissue from liver parenchyma. H&E, X100. B, Schematic drawing of the worm.
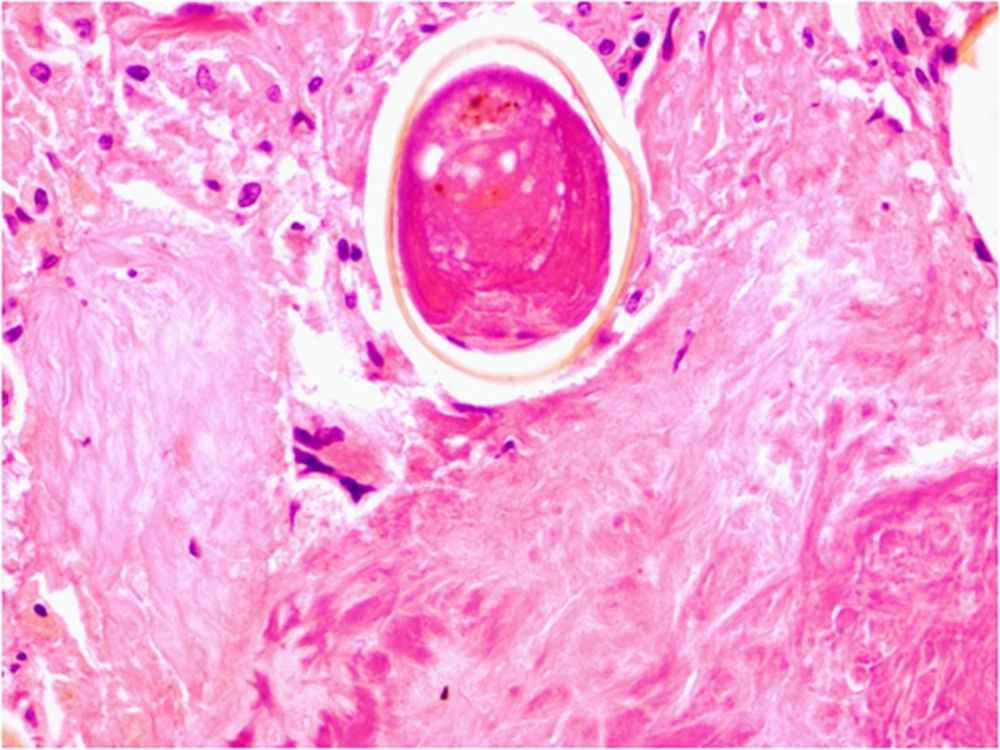
Figure 2.
A, Demised fluke is evident in the necrotic background, separated by dense fibrotic tissue from liver parenchyma. H&E, X100. B, Schematic drawing of the worm.
H and E stain, X400.
Figure 3.
H and E stain, X400.

3. Discussion

Recent studies showed an elevation in the incidence of liver fibrosis, cholangitis, cholecystitis, cholelithiasis, cholangiocarcinoma, and even hepatocellular carcinoma following liver fluke infection (5, 6). A systematic review showed an eightfold risk of cholangitis, fifteen-fold risk of cholecystitis, threefold risk of cholelithiasis, and fivefold risk of hepatocellular carcinoma following fascioliasis. However, the current study could not indicate a powerful relationship between this infection and cirrhosis. In fact, discovering liver fluke infection in patients with cirrhosis is a condition rarely reported (7).
Some probable mechanisms are described for development of cirrhosis following liver fluke infection. A recent study suggested that F. hepatica infection was associated with the upregulation of mRNAs associated with hepatic fibrogenesis in vivo and in activated hepatic stellate cells (8). Furthermore, the liver fluke may secrete some metabolites that can play an immunogenic stimulatory role leading to strong humoral immune responses (9). In fact, the presence of parasite antigens in various hepatobiliary portions such as biliary epithelium and its surrounding tissue can facilitate inflammatory cell infiltration and also activate host immune responses (10).
According to the current study findings, the development of liver fluke infection is expected in patients with cirrhosis, and thus, minute evaluation of liver explants for possible parasitic infestations including F. hepatica, particularly in endemic areas is suggested.


Footnotes

  • Authors’ Contribution:Elham Nazar, collection of clinical data, histopathologic evaluations, and drafting of the manuscript; Farid Azmoudeh-Ardalan, histopathologic evaluations and editing the manuscript; Iraj Mobedi, identification of the parasite and drawings of the worm; Seyed Habiballah Dashti, surgery and pre-operation practices on the patient; Faeze Salahshour, radiologist of the transplantation team and review of diagnostic images; Zahra Ahmadinejad, infectious disease consultant.

  • Implication:F. hepatica may infest cirrhotic livers; post-transplantation flare up of fascioliasis can also be problematic. Therefore, biliary system and liver parenchyma of explanted livers should be comprehensively evaluated for potential infestations in endemic areas.

References

  • 1.
    Keiser J, Utzinger J. Emerging foodborne trematodiasis. Emerg Infect Dis. 2005;11(10):1507-14. [PubMed ID: 16318688]. https://doi.org/10.3201/eid1110.050614.
  • 2.
    Control of foodborne trematode infections. Report of a WHO Study Group. World Health Organ Tech Rep Ser. 1995;849:1-157. [PubMed ID: 7740791].
  • 3.
    Lim JH. Liver flukes: the malady neglected. Korean J Radiol. 2011;12(3):269-79. [PubMed ID: 21603286]. https://doi.org/10.3348/kjr.2011.12.3.269.
  • 4.
    Villegas F, Angles R, Barrientos R, Barrios G, Valero MA, Hamed K, et al. Administration of triclabendazole is safe and effective in controlling fascioliasis in an endemic community of the Bolivian Altiplano. PLoS Negl Trop Dis. 2012;6(8). e1720. [PubMed ID: 22880138]. https://doi.org/10.1371/journal.pntd.0001720.
  • 5.
    Marcos LA, Yi P, Machicado A, Andrade R, Samalvides F, Sanchez J, et al. Hepatic fibrosis and Fasciola hepatica infection in cattle. J Helminthol. 2007;81(4):381-6. [PubMed ID: 17958928]. https://doi.org/10.1017/S0022149X07850231.
  • 6.
    Sripa B, Brindley PJ, Mulvenna J, Laha T, Smout MJ, Mairiang E, et al. The tumorigenic liver fluke Opisthorchis viverrini--multiple pathways to cancer. Trends Parasitol. 2012;28(10):395-407. [PubMed ID: 22947297]. https://doi.org/10.1016/j.pt.2012.07.006.
  • 7.
    Marcos LA, Bussalleu A, Terashima A, Espinoza JR. Detection of antibodies against Fasciola hepatica in cirrhotic patients from Peru. J Helminthol. 2009;83(1):23-6. [PubMed ID: 18817587]. https://doi.org/10.1017/S0022149X08067205.
  • 8.
    Marcos LA, Terashima A, Yi P, Andrade R, Cubero FJ, Albanis E, et al. Mechanisms of liver fibrosis associated with experimental Fasciola hepatica infection: roles of Fas2 proteinase and hepatic stellate cell activation. J Parasitol. 2011;97(1):82-7. [PubMed ID: 21348611]. https://doi.org/10.1645/GE-2420.1.
  • 9.
    Perrigoue JG, Marshall FA, Artis D. On the hunt for helminths: innate immune cells in the recognition and response to helminth parasites. Cell Microbiol. 2008;10(9):1757-64. [PubMed ID: 18505479]. https://doi.org/10.1111/j.1462-5822.2008.01174.x.
  • 10.
    Xia J, Jiang SC, Peng HJ. Association between Liver Fluke Infection and Hepatobiliary Pathological Changes: A Systematic Review and Meta-Analysis. PLoS One. 2015;10(7). e0132673. [PubMed ID: 26186510]. https://doi.org/10.1371/journal.pone.0132673.

Copyright

Copyright © 2017, Hepatitis Monthly. This is an open-access article distributed under the terms of the Creative Commons Attribution-NonCommercial 4.0 International License (http://creativecommons.org/licenses/by-nc/4.0/) which permits copy and redistribute the material just in noncommercial usages, provided the original work is properly cited.

Similar Articles

26
Dec
2014
Fasciola hepatica an Unusual Cause of Chronic Cholecystitis

Fasciola hepatica an Unusual Cause of Chronic Cholecystitis

Hadiseh Hosamirudsari,
Yousef Jalali Roudsari

Hosamirudsari H, Jalali Roudsari Y. Fasciola hepatica an Unusual Cause of Chronic Cholecystitis. Int J Infect. 2015;2(2):e23108. doi: https://doi.org/10.17795/iji-23108

12
Apr
2017
MRCP Findings of Hepatobiliary Fascioliasis : A Case Report

MRCP Findings of Hepatobiliary Fascioliasis : A Case Report

Shaghayegh Sadat Khabbaz

Khabbaz SS. MRCP Findings of Hepatobiliary Fascioliasis : A Case Report. I J Radiol. 2017;14(Special Issue):e48046. doi: https://doi.org/10.5812/iranjradiol.48046

31
Dec
2017
Evaluation of Bilirubin, Phosphorus, Calcium and Cholesterol Levels in Bile of Livers Consistent with Hepatic Fascioliasis

Evaluation of Bilirubin, Phosphorus, Calcium and Cholesterol Levels in Bile of Livers Consistent with Hepatic Fascioliasis

Jasem Saki,
Iman Khodkar,
Mohammad Hossien Razi Jalali

Saki J, Khodkar I, Razi Jalali MH. Evaluation of Bilirubin, Phosphorus, Calcium and Cholesterol Levels in Bile of Livers Consistent with Hepatic Fascioliasis. Jentashapir J Cell Mol Biol. 2017;8(5):e65813. doi: https://doi.org/10.5812/jjhr.65813

22
May
2013
A Case of Fascioliasis from South-East of Iran

A Case of Fascioliasis from South-East of Iran

Roya Alavi-Naini,
Batool Sharifi-Mood,
Ali Reza Khazaei,
Parisa Khorgami

Alavi-Naini R, Sharifi-Mood B, Khazaei AR, Khorgami P. A Case of Fascioliasis from South-East of Iran. Zahedan J Res Med Sci. 2013;15(12):e4335. doi:

21
May
2013
Isolated Tuberculosis of Transplanted Liver, A Case Report and Review of the Literature

Isolated Tuberculosis of Transplanted Liver, A Case Report and Review of the Literature

Bita Geramizadeh,
Saman Nikeghbalian,
Parisa Janghorban,
Seyed Ali Malekhosseini

Geramizadeh B, Nikeghbalian S, Janghorban P, Malekhosseini SA. Isolated Tuberculosis of Transplanted Liver, A Case Report and Review of the Literature. Hepat Mon. 2013;13(5):e6691. doi: https://doi.org/10.5812/hepatmon.6691

More by these authors

Elham NazarPubMedScholar
Farid Azmoudeh-ArdalanPubMedScholar
Iraj MobediPubMedScholar
Seyed Habiballah DashtiPubMedScholar
Faeze SalahshourPubMedScholar
Zahra AhmadinejadPubMedScholar
Share
Cited by
Metrics