
1. Context
A child’s development can evolve from many interaction of congenital, family cultural, and environmental factors. Cognitive development and a child’s learning abilities can be assigned to different variables. Cognitive performance can be related to physical health (1). For example children who experience medical distress have lower academic achievement (2). Moreover, poor health leads to lower participation in daily school activities (3). Children with medical conditions have difficulties in building critical emotional bonds with their teachers (4).
Therefore, based on the recent studies, students who have medical distress will show low educational level and will experience social and economic inequalities, and behavior problems also in their adulthood (4, 5). Health behavior is closely related to academic achievement (6); so, improving a child’s physical health will lead to the higher level of academic performance (7-9).
A child’s physical health, and in particular physical fitness, is related with improving the child’s confidence, increasing the attention, reducing the health problems, improving social engagement, reducing obesity, increasing organization, and hosting many potentially protective factors for students at risk for poor school outcomes (10). Low levels of physical fitness leads to lower mental health and academic problems (11, 12). Children who are experiencing health problems are at higher risk for school failure, grade retention, and dropout.
Such critical role of health associated with students’ educational development, requires school psychologists to become responsible for improving students’ health which ultimately leads in decreasing the risk associated with various medical issues.
The common manageable factors of student health can be categorized in to nutrition, maintaining healthy weight, and physical fitness. However, school principals neglect and do not promote the school health. Due to societal changes and important school reforms, the job requirements of school principals have dramatically changed (13). Despite the progress school health promotion has made in recent years, surprisingly principals and their roles have scarcely been examined in theory and practice. This might be related to the primary responsibility for most school matters which lies with the school administration.
Thus, it is not surprising that a wealth of educational research has shown that school leaders do make a difference in school effectiveness and school improvement (14). The same can be expected with regard to the success of school health promotion activities.
Recent studies show that principals as “gatekeepers” to school innovations have significant role on whether or not a school will become and remain a healthy organization (15, 16). Within all phases of the school health development process, principals are responsible for e.g. building and maintaining high motivation (e.g. through vision building), supporting their school staff in developing the skills needed for successful change, coordinating the processes and activities, and encouraging the school staff to sustain new practices and activities.
In order to improve the mental health of students, educational and non-educational factors are very important. Providing education consultancy to increase the students’ interest in the field of their study as well as non-educational counseling to reduce problems are important steps in increasing the school health (17).
In examining the relationship between happiness and mental health status among students, Moeini et al. (17), have shown that happiness is related to mental health, therefore planning to increase happiness in students can be considered as one of the ways to improve mental health.
Abassi et al. (18), conduct a study regarding to the mental health of students. They found that students mental health is associated with variety of factors, such as school, home, and more attention to the role of school training. To improve the mental health of students schools should establish appropriate settings, as well as providing conditions that school authorities, psychologists and other educators can be familiar with mental health topics (18).
In reviewing managerial styles with mental health and creativity by Aftabsavar et al. (19), it was found that there is not a meaningful relationship between managerial styles and mental health, but there is a significant and negative relation between mental authority orientation and mental health. There is also a significant and positive relationship between management styles and creativity, and there is a significant negative relationship between creativity and mental health dimensions (social disorders and depression). However, physical and anxiety disorders do not have a significant relationship with creativity of teachers (19).
2. Objectives
As a result, in the process of school progress and the achievement of a healthy school, the principals are responsible from beginning to end. Therefore, the main purpose of this research is to explain the conceptual framework for the school leadership as health management. Considering the above goal, the following research questions are considered: What are the factors and components of this competence?; What is the validity of the identified factors in the management of schools in the statistical society?
3. Methods
This is a descriptive-analytic study using a cross-sectional method. The research was combined with qualitative and quantitative research in a descriptive-cross-sectional study. The qualitative analysis method, thematic analysis, and quantitative analysis of confirmatory factor analysis were used. The statistical society of the qualitative section is Internet databases and scientific information banks in the period 2000 - 2018 in the field of management competence. For comprehensive review of valid documents in the subject area of research, all scientific productions at the Scopus citation database with keyword searches: “health school”, “student health”, “school happiness”, “student mental health”, “physical fitness”, “school principal”, “school management”, “school leadership” was considered. By referring to these sources, all available information was selected and checked. A total of 200 sources were identified and, after re-examining, there were finally 70 resource-related remained and by studying the line to line in the articles and resources coded manually. In the qualitative section, a comprehensive health management theme was identified. Health management was identified with four pre-organizers of physical health, mental health, happiness and physical safety, which included 11 base themes. Statistical population of the quantitative part of the study was 823 school principal of Kermanshah Province and finally 120 principal randomly participated in this research. The instrument for collecting in this research was a researcher-made questionnaire with 53 items, which, based on thematic analysis and conceptual model of extraction, was prepared with a reliable validity and reliability under the supervision of experts. The multi-item constructs were measured on five-point Likert scales which ranged from “totally agree” (1) to “totally disagree” (5). The pre-organizing of physical health includes individual and general health (questions 1 to 2), nutrition (3 to 9) and physical fitness and physical activity (10 to 13). Mental health dimension includes psychological competence (14-16), mental health education (17 to 25) and psychological intervention and profession treatment (26 to 29). Happiness dimension includes environmental (30 to 34), educational (35 to 40) and emotional (41 to 46). Physical safety includes standards and agronomics (47 to 50), training and preparation contrast disasters (51 to 53). To confirm the validity of the questionnaire, experts were used, and the Cronbach’s alpha was used to determine its reliability. A Confirmatory factor analysis method was used for data analysis using SmartPlus3 software. In the confirmatory factor analysis, the questions that had the most impact were identified and the significance of the research dimensions as well as the severity of the effect of each of its components and its contents on the health management was determined. Finally the final model was confirmed.
4. Results and Discussion
This section consists of a thematic analysis process and consists of two sections of coding and analysis of concepts. In coding, all sources were first reviewed and, after reviewing, related resources were identified. Different content from various articles and books was originally lacking in coherence. Each source and reference looked from different angle to the managerial competencies. In the codification process, individual articles and resources considered and taking into account the general concept, selected parts of the text of the sources that were explicitly or implicitly associated with the code. Given the meaning of each concept, a name is assigned to that concept in the text and is included in the explanation in that section of the relevant source. After, with more text encodings, the file was continually being referred to and examined whether the specified section is related to one of the assigned themes or whether a new topic should be determined. During the work, these themes were revised and changed several times (Table 1).
Table 1.
Related Topics of Health Management
| Variable | Organizing Themes | Frequency of Codes |
|---|---|---|
| Health management | Physical health | 43 |
| Mental health | 23 | |
| Happiness | 66 | |
| Physical safety | 31 |
As shown in the table above, the theme of health management has four dimensions of physical health with 43 codes, mental health with 23 codes, happiness with 66 code and physical safety with 31 codes.
Parts of the content related to the topic “physical health” are from the source text: Scientific evidence about the relation of the children and adult’s health with washing hands, eating safe water and using a suitable sewage system is very high. In 1990, the World Health Organization (WHO) and the UNICEF developed a joint monitoring program for water supply, sanitation, and hygiene (WASH) across the world. Since that time, the program (WASH) has been a world leader in comparing progress in improving drinking water, sewage, and sanitation in the world. Nutrition is associated with the overall physical health and academic performance (20). Nutrition is considering as a problematic issue for school children (21). Food with high sodium, high fat, and low protein profiles are increasingly available and mostly not expensive. Physical activity is related with physical fitness program. However, the children’s consumption of low nutrition-dense foods is increasing and school-aged children spend less hours in doing physical activities (22).
Parts of the material related to the theme “mental health” from the source text are as follows: Mental health as a large part of the students health, has a complex interaction with physical health and greatly relates success of the students’ School, work and society. Both mental and physical health affect how we think, how we feel, as well as our inner and outer behaviors. Therefore, all children have the right to have a happy and healthy life. When we discuss health, many people think physically and they are less concerned about the importance of mental health. Mental health issues such as low self-esteem, stress, coping with emotional issues has a clear impact on physical health, as well as a lack of physical health can impact on mental health such as stress, depression and anxiety (23). Mental health, It does not mean having mental illness, but it includes good social communication, emotions, behavioral health, and the ability to adapt to the challenges of life (24).
Parts of the content related to the theme of “happiness” from the source text are as follows: A high level of happiness is associated with positive outcomes in various aspects of life, such as effective learning, creativity, innovation, good communication, appropriate social behavior, health and longevity (25). In other words, happiness means how much a person likes his life. Research shows happiness is one of the factors that can improve physical health. Lyubomirsky et al. (26) examines the role of individual factor in the happiness of individuals. He found that in particular in schools, students can successfully solve many future problems that may have a negative impact on them if they are raised with positive attitudes. If we want students to experience the process of learning in school, we need to bring joy and happiness to the learning environment for them, as well as review the content of education. Today, the use of schools is not for examinations and lessons, but for human development (27).
Parts of the content related to the topic “physical safety” from the source text are as follows: A secure and safe learning environment suggests that children should be protected from physical harm. Solutions to prevent accidents and injuries in the hands of the “manager” a person who creates calm and security by preventing unsafe situations in school. Unsafe activities and unsafe conditions are one of the major factors in the failure of a manager, which may affect the physical and mental conditions of employees as well as students. Physical infrastructure such as classrooms, staff rooms, toilets, kitchens, drinking rigs, playgrounds and other appliances is proportionate, and adequate to avoid any risk for users. Different standards for building schools are considered, such as: the size of the class with the number of students, the class should have proper roof, window, flooring and also ventilation (28).
In Figure 1, the research model is presented for school health management.
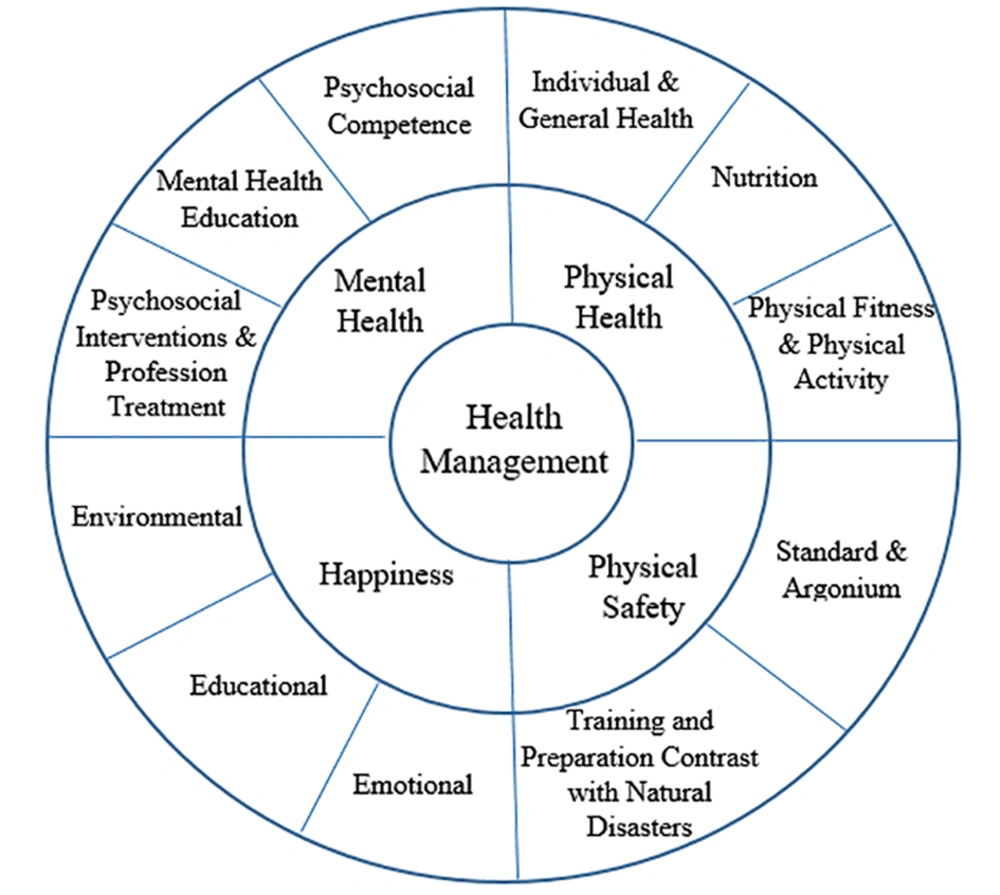
Figure 1.
Conceptual health management model
The evaluation of the modeling of health management in schools using Smart-PLS software was done in two steps: (A) Validity and reliability evaluation of the model; (B) assessing the structural model. The results of the SmartPLS software evaluated the validity and reliability of the measurement model according to the criteria used in the reflexive and developmental exterior models. In this way, first of all, the accuracy of the relationships in the measurement models is ensured by using reliability and validity criteria, and then the relationship between the structural part is examined and interpreted, and in the final stage, the goodness of fit of the research model is examined.
The fitting of measuring models includes reliability and validity of research structures. The reliability of the test relates precisely to its size and stability. Cronbach’s alpha is a classic criterion for measuring reliability and an internal sustainability assessment index. Internal stability indicates the correlation between a structure and its related indexes. In the case of variables with low number of questions, the alpha coefficient of 0.6 is introduced as the threshold limit of the coefficient and more than 0.7 is a reliable indicator.
In order to determine the reliability of each of the structures, in addition to the traditional Cronbach’s alpha, more modern criterion of composite reliability (CR) has been used. The superiority of this criterion to the Cronbach’s alpha coefficient is that the reliability of the structures is calculated not absolute but with respect to the correlation of their structures. To measure better the reliability of both criteria is used. The composite reliability value above 0.7 for each structure indicates an intrinsic stability for measuring models and indicates a value of less than 0.6 in the absence of reliability (29). The combined stability values for research structures are higher than 0.8.
After reviewing the reliability criterion, the second criterion is the average variance extracted (AVE). The AVE criterion represents the average of the variance shared between each construct with its own indexes and it should be at least 0.5. In Table 2. The general criteria of the model’s quality are expressed. Since the values of each of the variables are defined more than the threshold, therefore, the appropriateness of the reliability status and the convergent validity of the research model can be confirmed.
Table 2.
General Criteria for Model Quality
| Variables | AVE | CR | R2 | Cronbach’s Alpha |
|---|---|---|---|---|
| Physical health | 0.429 | 0.904 | 0.810 | 0.883 |
| Individual and general health | 0.715 | 0.834 | 0.417 | 0.606 |
| Nutrition | 0.476 | 0.859 | 0.929 | 0.805 |
| Physical fitness and physical activity | 0.595 | 0.853 | 0.795 | 0.767 |
| Mental health | 0.542 | 0.949 | 0.701 | 0.942 |
| Psychosocial competence | 0.804 | 0.924 | 0.717 | 0.878 |
| Mental health education | 0.601 | 0.931 | 0.954 | 0.916 |
| Psychosocial interventions and profession treatment | 0.629 | 0.869 | 0.713 | 0.798 |
| Happiness | 0.448 | 0.929 | 0.861 | 0.918 |
| Environmental | 0.582 | 0.871 | 0.597 | 0.816 |
| Educational | 0.560 | 0.879 | 0.822 | 0.828 |
| Emotional | 0.665 | 0.922 | 0.792 | 0.897 |
| Physical safety | 0.727 | 0.914 | 0.583 | 0.874 |
| Standard and argonium | 0.727 | 0.914 | 0.999 | 0.874 |
| Training and preparation contrast with natural disasters | 0.772 | 0.910 | 0.620 | 0.8520 |
In Table 3, factor load values and t value for each item are reported. With regard to the results of the output of the SmartPLS software, the perceived school health management framework can be concluded because the magnitude of the load factor of the observed variables and the corresponding variable is appropriate values (mostly higher than 0.7) There are a high correlation and validity between the research questions and sub-components.
Table 3.
Factor Load Values and t Statistics for Each Item
| Pre-Organizing Factor | Base Themes | Indicator | Loading | t Value | Sig. | Decision |
|---|---|---|---|---|---|---|
| Physical health | Individual and general health | IG1 | 0.809 | 13.539 | 0.001 | Supported |
| IG2 | 0.881 | 34.112 | 0.001 | Supported | ||
| Nutrition | N1 | 0.825 | 22.599 | 0.001 | Supported | |
| N2 | 0.858 | 29.703 | 0.001 | Supported | ||
| N3 | 0.748 | 14.268 | 0.001 | Supported | ||
| N4 | 0.535 | 5.341 | 0.001 | Supported | ||
| N5 | 0.700 | 13.044 | 0.001 | Supported | ||
| N6 | 0.459 | 4.245 | 0.001 | Supported | ||
| N7 | 0.612 | 7.975 | 0.001 | Supported | ||
| Physical fitness and physical activity | FA1 | 0.630 | 7.151 | 0.001 | Supported | |
| FA2 | 0.763 | 15.920 | 0.001 | Supported | ||
| FA3 | 0.841 | 23.660 | 0.001 | Supported | ||
| FA4 | 0.834 | 22.091 | 0.001 | Supported | ||
| Mental health | Psychosocial competence | PC1 | 0.890 | 34.233 | 0.001 | Supported |
| PC2 | 0.897 | 30.894 | 0.001 | Supported | ||
| PC3 | 0.903 | 38.460 | 0.001 | Supported | ||
| Mental health education | MHE1 | 0.802 | 10.519 | 0.001 | Supported | |
| MHE2 | 0.771 | 13.192 | 0.001 | Supported | ||
| MHE3 | 0.684 | 8.528 | 0.001 | Supported | ||
| MHE4 | 0.765 | 15.529 | 0.001 | Supported | ||
| MHE5 | 0.811 | 13.933 | 0.001 | Supported | ||
| MHE6 | 0.776 | 13.939 | 0.001 | Supported | ||
| MHE7 | 0.838 | 20.738 | 0.001 | Supported | ||
| MHE8 | 0.730 | 11.535 | 0.001 | Supported | ||
| MHE9 | 0.793 | 14.28 | 0.001 | Supported | ||
| Psychosocial interventions and profession treatment | PIPT1 | 0.853 | 26.662 | 0.001 | Supported | |
| PIPT2 | 0.868 | 32.308 | 0.001 | Supported | ||
| PIPT3 | 0.803 | 18.875 | 0.001 | Supported | ||
| PIPT4 | 0.625 | 7.223 | 0.001 | Supported | ||
| Happiness | Environmental | EN1 | 0.776 | 18.135 | 0.001 | Supported |
| EN2 | 0.809 | 17.618 | 0.001 | Supported | ||
| EN3 | 0.506 | 4.760 | 0.001 | Supported | ||
| EN4 | 0.796 | 16.311 | 0.001 | Supported | ||
| EN5 | 0.875 | 34.220 | 0.001 | Supported | ||
| Educational | ED1 | 0.583 | 6.325 | 0.001 | Supported | |
| ED2 | 0.815 | 16.049 | 0.001 | Supported | ||
| ED3 | 0.422 | 4.607 | 0.001 | Supported | ||
| ED4 | 0.884 | 29.934 | 0.001 | Supported | ||
| ED5 | 0.879 | 28.267 | 0.001 | Supported | ||
| ED6 | 0.792 | 12.915 | 0.001 | Supported | ||
| Emotional | EM1 | 0.686 | 10.690 | 0.001 | Supported | |
| EM2 | 0.753 | 12.824 | 0.001 | Supported | ||
| EM3 | 0.837 | 15.645 | 0.001 | Supported | ||
| EM4 | 0.868 | 33.298 | 0.001 | Supported | ||
| EM5 | 0.870 | 27.216 | 0.001 | Supported | ||
| EM6 | 0.864 | 24.620 | 0.001 | Supported | ||
| Physical safety | Standard and argonium | SA1 | 0.858 | 21.410 | 0.001 | Supported |
| SA2 | 0.882 | 26.813 | 0.001 | Supported | ||
| SA3 | 0.848 | 23.145 | 0.001 | Supported | ||
| SA4 | 0.822 | 19.485 | 0.001 | Supported | ||
| Training and preparation contrast with natural disasters | TPND1 | 0.867 | 22.101 | 0.001 | Supported | |
| TPND2 | 0.865 | 27.274 | 0.001 | Supported | ||
| TPND3 | 0.904 | 28.930 | 0.001 | Supported |
Tables 4 and 5, report the results of a confirmatory factor analysis for the main variables and its sub-components, at the level of dimensions in the school health management model.
Table 4.
Factor Load Values and t Values of Base Themes
| Variable | Indicator | Factor Load | t Value |
|---|---|---|---|
| Physical health | Individual and general health | 0.646 | 7.630 |
| Nutrition | 0.964 | 140.420 | |
| Physical fitness and physical activity | 0.892 | 48.612 | |
| Mental health | Psychosocial competence | 0.847 | 24.306 |
| Mental health education | 0.977 | 159.102 | |
| Psychosocial interventions and profession treatment | 0.844 | 24.465 | |
| Happiness | Environmental | 0.733 | 19.628 |
| Educational | 0.907 | 34.987 | |
| Emotional | 0.890 | 24.253 | |
| Physical safety | Standard and argonium | 1.000 | 8194.908 |
| Training and preparation contrast with natural disasters | 0.788 | 12.981 |
Table 5.
Pre-Organizing Factor Load Values and t Values
| Variable | Indicator | Factor Load | t Value |
|---|---|---|---|
| School health management | Physical health | 0.900 | 39.420 |
| Mental health | 0.837 | 26.907 | |
| Happiness | 0.928 | 52.324 | |
| Physical safety | 0.764 | 12.179 |
To evaluate the fit of the structural model, the several criteria is used, the first and most fundamental of which is the z coefficient, or the values of t values, which are represented by the execution of the bootstrap command of the values on the lines. If the values of t are greater than 1.96, then the correlation between the structures is 95% in the confidence level. In Figure 2, values are shown to evaluate the structural part of the model. Given that all numbers on the paths are higher than 1.96, this indicates the significance of the paths, the appropriateness of the structural model of the research.
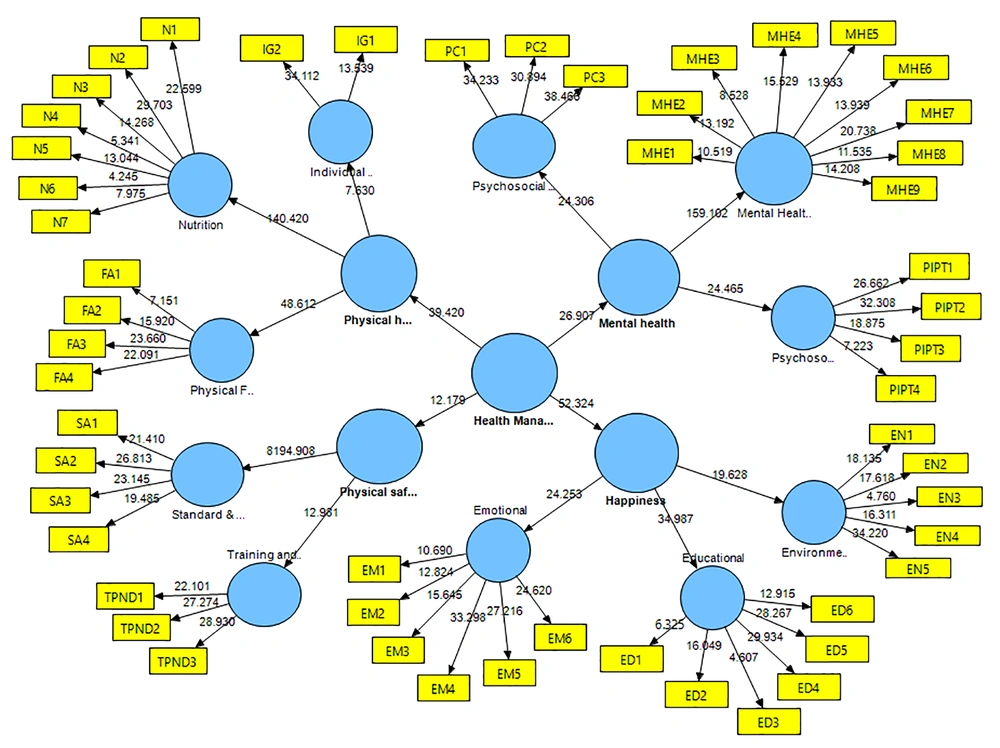
Figure 2.
Confirmatory factor analysis
To evaluate the fit of the model in partial least squares, we use the goodness of fit (GOF). In this model, the GOF is equal to 0.64, indicating an upper general fit for the structural model.
5. Conclusions
During school years of life, children improves their physical, motor, social intelligence, cognitive and language development. So these early childhood growth can open up a window of opportunity to provide a strong foundation for their life and future and protecting them from unsafe condition.
Neuroscience demonstrates great influenced of early experiences in brain development. Attention to health, nutrition and early stimulation in the early years can facilitate brain development and leads to children’s wellbeing. Early care during growth, educational programs can lead to appropriate child development, as well as provide a basis for lifelong learning. If children are exposed to negative conditions and experiences during the early years of life, it negatively impact all aspects of life such as social and economic development and human capital formation of nation.
Schools, as the most important place for future generations, should be a healthy and dynamic environment. Creating a happy and vibrant environment will help a lot of learners to learn. Therefore, more and more effort should be made to improve the health of schools. In an unsafe environment, teaching and learning cannot be appropriate for both students and teachers, school principals have a role to play in creating a safe, secure, and learning environment for students. The purpose of this study was to explain and elaborate a model for the competence of school principals as the health leaders and change agents. In this paper focused on the role of school principals in an effort to manage a healthy school.
In addition to the principles of planning, organizing, commanding, and monitoring, managers also seem to need other skills that support mental, emotional and intuitive performance.
The competency model is the heart of the approach based on the competence of human resources, and it is suggested that the model be used in practice. By giving more authority to school administrators, they will provide the groundwork and conditions for achieving these goals.