1. Introduction
Dextrocardia refers to an abnormal rightward position of the heart within the thorax, with the cardiac axis extending from the base toward the right-sided apex. This malposition is intrinsic to the heart and is not caused by extracardiac abnormalities (1).
Situs describes the arrangement of the asymmetrically positioned thoracoabdominal organs and the heart. It may be categorized into three principal patterns: situs solitus, the usual arrangement of the internal organs; situs inversus, a mirror-image arrangement; and situs ambiguous (heterotaxy), in which organ laterality is variable. In situs solitus, the thoracoabdominal organs have their typical distribution, including a trilobed right lung, a bilobed left lung, a right-sided liver, and a left-sided stomach and spleen, with the atrial arrangement corresponding to the visceral situs.
In situs inversus, this arrangement, including atrial laterality, is completely reversed (2).
Situs ambiguous represents a disordered arrangement in which organ laterality is inconsistent and often symmetric (isomerism). It comprises two major subtypes: asplenia syndrome (right isomerism), characterized by absence of the spleen, bilateral trilobed lungs with eparterial bronchi, right atrial morphology on both sides, and severe associated congenital heart disease; and polysplenia syndrome (left isomerism), characterized by multiple small spleens, bilateral bilobed lungs with hyparterial bronchi, left atrial morphology on both sides, and milder cardiovascular anomalies (3).
Understanding situs patterns is essential when evaluating cardiac malposition, including dextrocardia, because chamber orientation, venous connections, and associated congenital defects depend strongly on the underlying situs.
2. Case Presentation
In May 2025, a 25-year-old man underwent a pre-employment assessment at an occupational medicine clinic as part of the recruitment process for a firefighting position. According to the occupational exposure assessment, the job involves exposure to several workplace factors, including noise, ergonomic stressors such as prolonged standing or sitting, chemical exposures such as dust and solvents, and psychological stress related to occupational demands.
The patient reported no past medical history and no known family history of significant disease. He also denied any history of dyspnea, chest pain, palpitations, or exercise intolerance.
On physical examination, his height was 180 cm and his weight was 80 kg, corresponding to a body mass index (BMI) of 24.7 kg/m². His blood pressure was 125/80 mmHg. Cardiovascular examination revealed predominantly right-sided heart sounds. The remainder of the physical examination was unremarkable.
Routine laboratory investigations, including blood tests and urinalysis, revealed no abnormalities. Spirometry showed normal pulmonary function, and optometric and audiometric evaluations were also unremarkable.
The patient was referred for cardiology consultation because of the unusual cardiac auscultation findings. Chest radiography demonstrated a right-sided cardiac apex, consistent with dextrocardia, without an apparent pulmonary abnormality (Figure 1A). The electrocardiogram showed sinus rhythm with findings compatible with dextrocardia, including predominantly negative QRS complexes in lead I, a positive aVR, and reversed/poor R-wave progression across the standard precordial leads (Figure 1B). Further cardiac evaluation confirmed dextrocardia. Echocardiography demonstrated preserved cardiac function, with a left ventricular ejection fraction (LVEF) of 55%; no significant structural cardiac abnormality was identified on cardiology assessment. The cardiologist considered the dextrocardia isolated, with no clinically significant associated congenital cardiac abnormality identified. Detailed visceral situs was not formally documented in the available clinical records.
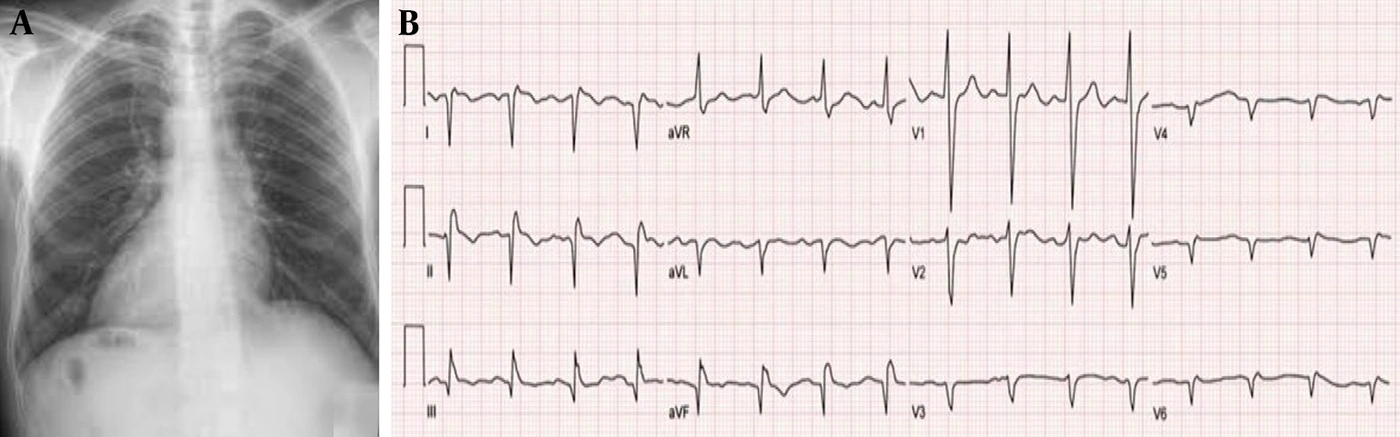
Figure 1.
Cardiovascular investigations demonstrating dextrocardia. (A) Chest radiograph showing rightward cardiac apex and right-sided cardiac silhouette, consistent with dextrocardia, without an apparent pulmonary abnormality. (B) Electrocardiogram showing findings compatible with dextrocardia, including predominantly negative QRS complexes in lead I, positive aVR, and reversed/poor R-wave progression across the precordial leads.
Functional capacity was assessed using the 3-minute Queen's College Step Test (4). After contraindications to the test were assessed, the patient performed the test on a 41.3-cm (16.25-inch) step at a cadence of 24 steps per minute for 3 minutes. Immediately after completion, his recovery heart rate was measured according to the test protocol and used to estimate maximal oxygen uptake (VO₂max) using the sex-specific Queen's College Step Test equation. The estimated aerobic capacity was 18 METs (approximately 63 mL/kg/min). The patient completed the test without exercise-related symptoms or intolerance. No clinically significant abnormal response was reported during the assessment.
Fitness for firefighting duties was determined according to the Guideline for Conducting Medical Examinations and Issuing Medical Fitness Certification for Firefighters in the Oil Industry (WI-08-03-OM), developed by the Occupational Health and HSE Department of the Petroleum Industry Health Organization and last revised in 2021 (5). According to this guideline, the minimum required aerobic capacity for firefighters is 12 METs. The patient's estimated aerobic capacity of 18 METs therefore exceeded the occupational threshold by 50%.
Based on the cardiology assessment, the patient currently has no cardiac limitations, and strenuous physical or occupational activities are not contraindicated. Therefore, from a cardiovascular standpoint, he is considered fit to perform the duties required for firefighting.
At one-year follow-up, the patient remained actively employed as a firefighter and reported no cardiovascular symptoms or work-related limitations. His periodic occupational health examination included repeat cardiovascular evaluation; the cardiologist found no new clinically significant cardiac abnormality and confirmed his cardiovascular fitness. The occupational medicine specialist also confirmed his fitness for continued firefighting duties. No cardiovascular events, exercise intolerance, or occupational difficulties were reported during the first year of employment. A formal patient-perspective statement was not obtained for this case report.
Clinical timeline: The chronological sequence of the clinical evaluation was as follows: pre-employment occupational examination → detection of predominantly right-sided heart sounds on auscultation → chest radiography and ECG → cardiology referral → echocardiographic evaluation and confirmation of isolated dextrocardia → assessment of aerobic capacity by the 3-minute Queen's College Step Test (18 METs) → assessment against the occupational fitness criteria for firefighters (minimum 12 METs) → final cardiovascular fitness determination for firefighting duties.
3. Discussion
Dextrocardia is an uncommon congenital abnormality of cardiac position in which the heart is oriented toward the right side of the thorax. It may occur as an isolated finding or as part of a broader spectrum of congenital cardiac abnormalities. The spectrum of associated abnormalities varies according to the anatomical subtype; septal, atrioventricular, great-vessel, and pulmonary arterial abnormalities have been reported in patients with more complex forms of dextrocardia (1, 2). Its clinical significance depends largely on the underlying visceral situs and the presence or absence of associated structural cardiac abnormalities and conduction disturbances (1, 2). Recent CT angiographic data further demonstrate that associated anomalies can include septal defects, atrioventricular septal defects, transposition of the great arteries, and pulmonary arterial abnormalities, particularly in more complex forms of dextrocardia (2). The spectrum ranges from isolated mirror-image dextrocardia with normal cardiac anatomy to complex malformations such as congenitally corrected transposition of the great arteries (ccTGA) and heterotaxy syndromes (2, 3).
From an embryological perspective, abnormal cardiac looping and laterality determination during early development result in variations in atrioventricular and ventriculoarterial connections. Disruptions in left–right axis formation, including ciliary dysfunction in some cases, may contribute to situs abnormalities and mirror-image anatomy (3, 6). However, in many individuals, particularly those with situs inversus totalis, dextrocardia may occur without clinically significant congenital heart disease and may remain undetected until adulthood (1).
The clinical implications of dextrocardia are highly variable. In individuals with isolated dextrocardia and no significant associated cardiac abnormalities, the clinical course may be favorable, although prognosis depends on the underlying cardiac anatomy and associated conditions (1, 5). In contrast, certain forms—particularly those associated with ccTGA—carry substantial risks of systemic right ventricular failure, atrioventricular valve regurgitation, and progressive conduction system disease, including complete atrioventricular block (7, 8). These complications often develop with age and may significantly affect functional capacity.
In occupational settings such as firefighting, cardiovascular fitness is a critical determinant of safety and performance. Firefighting is classified as a high-intensity, physically demanding occupation associated with substantial cardiovascular strain (9). Sudden cardiac events remain a leading cause of line-of-duty mortality among firefighters, underscoring the importance of thorough cardiovascular evaluation during preemployment screening and periodic medical examinations (10). Current recommendations for adult congenital heart disease emphasize individualized risk assessment based on the underlying cardiac anatomy, ventricular function, exercise capacity, and rhythm status rather than on the congenital diagnosis alone (1).
In the present case, comprehensive cardiovascular evaluation demonstrated isolated dextrocardia without associated structural heart disease, preserved ventricular function, normal rhythm, and excellent exercise capacity. These findings indicate that dextrocardia, in the absence of hemodynamic compromise, arrhythmia, or anatomical complexity, does not necessarily limit occupational performance in physically demanding roles. Therefore, fitness-for-duty decisions should be guided by functional assessment and evidence of cardiac stability rather than by anatomical positioning alone.
This case highlights the importance of systematic cardiovascular evaluation in individuals with dextrocardia, particularly in safety-sensitive occupations. A structured assessment—including echocardiography, electrocardiography, and functional exercise testing when indicated—helps exclude associated anomalies and supports evidence-based occupational decision-making.
An important strength of this case is the availability of one-year occupational follow-up. The patient remained actively employed as a firefighter without reported cardiovascular symptoms or work-related limitations, and subsequent periodic cardiovascular and occupational health assessments continued to support his fitness for duty. Although this follow-up provides useful real-world information about occupational tolerance in this individual, its duration is insufficient to establish long-term cardiovascular prognosis.
In the present case, the patient's preserved cardiac function and excellent exercise capacity, together with the applicable occupational criteria for firefighters, supported his fitness for firefighting duties. However, this finding should not be interpreted as evidence that dextrocardia is compatible with unrestricted employment across all occupations. Occupational fitness is context-dependent and should be determined individually according to the underlying cardiac anatomy, functional capacity, risk of sudden incapacitation, and the physical and safety requirements of the intended occupation.
This case has several limitations. As a single case report, the findings cannot be generalized to all individuals with dextrocardia or to other safety-sensitive occupations. In addition, although one year of follow-up provides evidence of short-term occupational tolerance, it does not allow conclusions about long-term cardiovascular prognosis.
4. Conclusion
In this case, isolated dextrocardia without identified significant structural or functional cardiac abnormalities was compatible with the physical demands of firefighting. The patient demonstrated excellent exercise capacity and remained asymptomatic and fully active in his occupation during one year of follow-up. Subsequent periodic cardiovascular and occupational health assessments confirmed his fitness for continued firefighting duties. However, this finding should not be generalized to all individuals with dextrocardia or to all occupations. Fitness-for-duty decisions should remain individualized and occupation-specific, based on the presence of associated cardiac abnormalities, functional capacity, and the demands and safety requirements of the intended occupation.