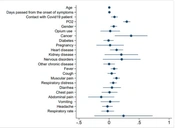
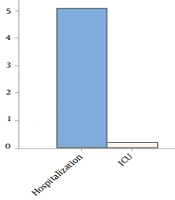
1. Background
Although many characteristics of coronavirus disease 2019 (COVID-19) were unknown at the time of its appearance, it was apparent that there was an ongoing substantial increase in the demand for hospital beds and mechanical ventilators in the infected countries (1-3). However, health systems around the world failed to respond quickly to the COVID-19 challenge. Insufficient hospital beds (general and intensive), mechanical ventilators, medicines, staff, and protective equipment such as masks were some of the health systems' deficiencies in coping with this new enemy. In the situation that there was insufficient treatment capacity, like intensive care beds and ventilators, some countries were imperative to patient selection. Based on the information from early infected countries, 5 - 16% of the infected individuals required admission to the intensive care unit (ICU) that put a massive burden on their health systems, and faced them with insufficient treatment capacity, so some countries were imperative to patient selection (4, 5). According to the existing evidence, lack of hospital admission is related to a higher mortality rate of COVID-19 patients (6).
Determining the future needs for hospital resources requires two kinds of information: the number of patients and the length of stay in hospital (LOSH) (7, 8). Based on the studies of differences in disease severity among COVID-19 patients, factors such as comorbidity and age could predict disease severity (6, 8, 9) and consequently LOSH (3, 10-16). Therefore, understanding these factors could help the health system meet the future demand for hospital beds and other resources through evidence-based planning for the future demand (7, 8).
The overwhelming increase in the number of COVID-19 patients causes a considerable demand for hospital beds and equipment, and other health services, which may force the health system to do some rationing of its capacity (5, 17-19). Besides, the future disease waves may lead to the need for more hospital beds, as the experience of influenza virus type H1N1 disease demonstrated that the second wave of disease required more hospital beds (20). Therefore, it is necessary to ensure how well the health system can deal with the probable future waves of this disease.
2. Objectives
This study aimed to determine the factors affecting the hospitalization days of COVID-19 patients in Hamadan city, the west of Iran.
3. Methods
This retrospective observational study recruited 512 COVID-19 patients who had positive real-time reverse-transcriptase polymerase chain reaction (RT-PCR) test of upper respiratory nasopharyngeal swab samples. The confirmed patients in this study were hospitalized from 1 March to 18 June 2020 in Sina hospital in Hamadan, the west of Iran. Data were gathered from patients’ medical records by a trained nurse using a predetermined checklist, as follows:
3.1. Demographic Characteristics
Gender, age (older or younger than 60 years), marital status (married, single, divorced/dead spouse), residence (rural, urban), contact with infected cases, opioid consumption, and duration of symptoms before referring to the hospital (lower or higher than 48 hours)
3.2. Clinical Manifestations
Comorbid diseases (none, diabetes, cardiovascular, both), systolic blood pressure (lower or higher than 90 mmHg), breathing patterns (normal, tachypnea, dyspnea/distress), auscultation of the lungs (normal, abnormal (crackling/rales/wheezing)), respiratory rate (lower or higher than 30 per minute), heart rate (lower or higher than 125 per minute), and electrocardiogram results (ECG: normal, abnormal);
3.3. Laboratory Findings
Peripheral oxygen saturation with pulse oximeter (SPO2: lower or higher than 88%), C-reactive protein (CRP: negative, positive), Erythrocyte Sedimentation Rate (ESR: 0-10 mm/h, higher than 10 mm/h), Creatinine (lower than 0.8 mg/dL, 0.8 - 1.3 mg/dL, higher than 1.3 mg/dL), Blood Urea Nitrogen (BUN: lower or higher than 20 mg/dL), Partial Thromboplastin Time (PTT: lower or higher than 35 s), platelet count (130 - 400 × 1000 µL, lower than 130 × 1000 µL), Prothrombin Time (PT: 11 - 13 s, higher than 13 s), the count of White Blood Cells (WBC: 4.5 - 11 × 1000 µL, lower than 4.5 × 1000 µL, higher than 11 × 1000 µL), neutrophils (40 - 60%, lower than 40%, higher than 60%), lymphocytes (20 - 40%, lower than 20%, higher than 40%), monocytes (2 - 8%, lower than 2%), hematocrit (HCT with normal range: 37 - 47% for women and 42 - 52% for men), hemoglobin (Hb with normal range: 12 - 16 g/dL for women and 14 - 18 g/dL for men), Lactate Dehydrogenase (LDH: lower or higher than 2 × ULN (942 U/L)), Creatine Phosphokinase (CPK: lower or higher than 342 IU/L), glutamic-pyruvic transaminase or Serum Glutamic-Pyruvic Transaminase (SGPT: lower or higher than 37 U/L), Serum Glutamic-Oxaloacetic Transaminase (SGOT: lower or higher than 45 U/L), Alkaline Phosphatase (ALP: lower or higher than 270 U/L), Potassium (K: 3.5 - 5.1 mEq/L, lower than 3.5 mEq/L, higher than 5.1 mEq/L), Sodium (Na: 136 - 145 mEq/L, lower than 136 mEq/L), and Blood Sugar (BS, 70 - 105 mg/dL, higher than 105 mg/dL);
3.4. Hospitalization in the ICU, Survival Status (Alive or Dead), and LOSH
Some descriptive statistics such as median and interquartile range (IQR) were carried out for all variables. Poisson regression is a known model for counting data such as LOSH under the assumption that the variance is equal to the mean made by the Poisson model. Due to the lack of this assumption in the present data, a negative binomial model was used as an alternative model. Unadjusted incidence risk ratio (IRR) estimates of LOSH were calculated using the simple negative binomial regression for discharged and total patients. Then, we selected variables with P-values of less than 0.3 to include in the multiple regression analysis. After fitting to the multiple negative binomial regression model, the variables with P-values of more than 0.3 whose elimination led to better-fitting were removed from the model. Moreover, adjusted IRR estimates of LOSH were calculated using the multiple negative binomial regression through the backward model for discharged and total patients (alive and deceased), separately. All analyses were performed at the 0.05 significance level using Stata 12 (21).
The Research Council of Hamadan University of Medical Sciences approved the protocol of this study with research ID 9903201588 and ethics code IR.UMSHA.REC.1399.269.
4. Results
The characteristics of alive and total patients (including alive and dead patients) are shown in Table 1. The individuals were primarily males, less than 60 years old, married, urban residents with no comorbid diseases. Moreover, the clinical manifestations and laboratory findings can be observed in Table 1. The median of LOSH was significantly (P = 0.023) lower in the discharged patients (5 days, range: 1 to 33 days) than in the deceased patients (7 days, range: 0 to 47 days); it was five days (range: 0 to 47) in the total patients.
During the study period, 57 (11.1%) patients were deceased, and 455 (88.9%) patients were discharged. The characteristics and the effects of various potential risk factors on LOSH using unadjusted IRR are presented in Table 1 for discharged and total patients. As observed in Table 1, the IRRs of LOSH in patients with age more than 60 years, divorced or deceased spouse, rural residence, comorbidity, pulmonary involvement, SPO2 lower than 88%, Cr lower than 0.8 mg/dL, platelets lower than 130 (× 1000 µL), lymphocytes lower than 20%, CPK higher than 342 IU/L, BS higher than 105 mg/dL, and ICU experience were significantly than their reference levels. Moreover, the respiratory rate of more than 30 per minute, abnormal ESR, BUN higher than 20 mg/dL, and referring to the hospital after 48 hours of being symptomatic significantly increased the IRRs for discharged patients. Besides, neutrophils lower than 40%, high HCT percentage, and high HB significantly increased the IRRs for total patients. However, the IRRs of LOSH in discharged patients with neutrophils lower than 40%, LDH higher than 942 U/L ( > 2 × ULN), and SGOT were higher than their reference levels, but the differences were not statistically significant (P = 0.073, P = 0.083, and P = 0.051, respectively) (Table 1).
Table 1.
Association Between LOSH of COVID-19 Patients and Potential Risk Factors Using Unadjusted Incidence Rate Ratio with Negative Binomial Regression
| Covariates | Alive and Dead (N = 512) | Alive (N = 455) | ||
|---|---|---|---|---|
| No. (%) | IRR (95% CI) | No. (%) | IRR (95% CI) | |
| Gender | ||||
| Male | 266 (52.0) | 1.00 | 235 (51.7) | 1.00 |
| Female | 246 (48.0) | 1.05 (0.94,1.17) | 220 (48.4) | 1.06 (0.95,1.19) |
| Age | ||||
| < 60 years | 287 (56.3) | 274 (60.4) | ||
| ≥ 60 years | 223 (43.7) | 1.32* (1.18,1.47) | 180 (39.7) | 1.26* (1.13,1.41) |
| Marital status | ||||
| Married | 430 (84.3) | 1.00 | 384 (84.6) | 1.00 |
| Single | 28 (5.5) | 0.92 (0.72,1.17) | 26 (5.7) | 0.92 (0.72,1.17) |
| Divorced or dead spouse | 52 (10.2) | 1.27* (1.07,1.51) | 44 (9.7) | 1.25* (1.05,1.5) |
| Residence | ||||
| Urban | 428 (83.6) | 1.00 | 380 (83.5) | 1.00 |
| Rural | 84 (16.4) | 1.26* (1.09,1.46) | 75 (16.5) | 1.26* (1.09,1.46) |
| Contact with infected cases | ||||
| No | 378 (73.8) | 1.00 | 340 (74.7) | 1.00 |
| Yes | 134 (26.2) | 0.97 (0.85,1.1) | 115 (25.3) | 0.97 (0.85,1.1) |
| Consumption of opioids | ||||
| No | 487 (95.1) | 1.00 | 432 (94.5) | 1.00 |
| Yes | 25 (4.9) | 0.77 (0.59,1.00) | 23 (5.5) | 0.84 (0.64,1.09) |
| Duration of symptoms | ||||
| ≤ 48 hours | 34 (7.2) | 1.00 | 26 (5.7) | 1.00 |
| > 48 hours | 437 (92.8) | 0.92 (0.74,1.14) | 392 (94.3) | 1.33* (1.03,1.71) |
| Comorbidity | ||||
| No | 368 (71.9) | 1.00 | 333 (73.2) | 1.00 |
| Diabetes | 63 (12.3) | 1.16 (0.99,1.37) | 57 (12.5) | 1.23* (1.04,1.45) |
| Cardiovascular disease | 60 (11.7) | 1.20* (1.01,1.41) | 48 (10.6) | 1.1 (0.92,1.32) |
| Both | 21 (4.1) | 1.45* (1.12, 1.88) | 17 (3.7) | 1.58* (1.21,2.07) |
| Systolic BP (mmHg) | ||||
| > 90 | 501 (98.2) | 1.00 | 448 (98.9) | 1.00 |
| ≤ 90 | 9 (1.8) | 0.76 (0.49,1.17) | 5 (1.1) | 0.76 (0.43,1.34) |
| Breathing patterns | ||||
| Normal | 91 (17.8) | 1.00 | 81 (17.8) | 1.00 |
| Tachypnea | 403 (78.7) | 0.93 (0.80,1.07) | 361 (79.3) | 0.91 (0.79,1.05) |
| Dyspnea and distress | 18 (3.5) | 0.90 (0.66,1.24) | 13 (2.9) | 0.93 (0.65,1.32) |
| Pulmonary involvement | ||||
| Normal | 380 (74.2) | 1.00 | 345 (75.8) | 1.00 |
| Abnormal | 132 (25.8) | 1.26* (1.11,1.42) | 110 (24.2) | 1.27* (1.12,1.43) |
| Respiratory rate (per minute) | ||||
| ≤ 30 | 492 (96.3) | 1.00 | 442 (97.4) | 1.00 |
| > 30 | 19 (3.7) | 1.19 (0.99,1.43) | 12 (2.6) | 1.44* (1.04,1.99) |
| Heart rate (per minute) | ||||
| ≤ 125 | 496 (97.5) | 1.00 | 440 (97.4) | 1.00 |
| > 125 | 13 (2.6) | 0.86 (0.60,1.22) | 12 (2.7) | 0.80 (0.55,1.15) |
| SPO2 (%) | ||||
| > 88 | 294 (57.4) | 1.00 | 278 (61.1) | 1.00 |
| ≤ 88 | 218 (42.6) | 1.46* (1.31,1.62) | 177 (38.9) | 1.53* (1.37,1.7) |
| ECG | ||||
| Normal | 411 (80.3) | 1.00 | 374 (82.2) | 1.00 |
| Abnormal | 101 (19.7) | 1.09 (0.95,1.25) | 81 (17.8) | 1.11 (0.96,1.28) |
| CRP | ||||
| Negative | 172 (36.1) | 1.00 | 156 (37.1) | 1.00 |
| Positive | 304 (63.9) | 1.00 (0.90,1.13) | 264 (62.9) | 0.99 (0.88,1.11) |
| ESR (mm/h) | ||||
| 0 - 10 | 56 (11.8) | 1.00 | 49 (11.6) | 1.00 |
| > 10 | 418 (88.2) | 0.99 (0.83,1.18) | 373 (88.4) | 1.22* (1.01,1.47) |
| BUN (mg/dL) | ||||
| 5 - 20 | 419 (82.6) | 1.00 | 394 (87.6) | 1.00 |
| > 20 | 88 (17.4) | 1.15 (0.99,1.32) | 56 (12.4) | 1.24* (1.05,1.46) |
| Cr (mg/dL) | ||||
| 0.8 - 1.3 | 369 (72.9) | 1.00 | 336 (74.8) | 1.00 |
| < 0.8 | 62 (12.3) | 0.78* (0.66,0.93) | 58 (12.9) | 0.82* (0.69,0.98) |
| > 1.3 | 75 (14.8) | 1.02 (0.87,1.19) | 55 (12.3) | 1.03 (0.86,1.22) |
| PT (s) | ||||
| 11 - 13 | 231 (55.1) | 1.00 | 205 (56) | 1.00 |
| > 13 | 188 (44.9) | 0.86* (0.76,0.97) | 161 (44) | 0.83* (0.73,0.94) |
| PTT (s) | ||||
| 25 - 35 | 247 (59.7) | 1.00 | 218 (60.4) | 1.00 |
| > 35 | 167 (40.3) | 1.06 (0.94,1.20) | 143 (39.6) | 1.05 (0.92,1.19) |
| Platelet (× 1000 µL) | ||||
| 130 - 400 | 91 (18.1) | 1.00 | 370 (83) | 1.00 |
| < 130 | 412 (81.9) | 1.25* (1.09,1.43) | 76 (17) | 1.23* (1.07,1.43) |
| WBC (× 1000 µL) | ||||
| 4.5 - 11 | 320 (63.5) | 1.00 | 287 (64.2) | 1.00 |
| < 4.5 | 155 (30.8) | 1.07 (0.95,1.20) | 147 (32.9) | 1.05 (0.93,1.19) |
| > 11 | 29 (5.8) | 1.15 (0.91,1.45) | 13 (2.9) | 1.08 (0.78,1.51) |
| Lymphocytes (%) | ||||
| 20 - 40 | 274 (54.7) | 1.00 | 260 (58.4) | 1.00 |
| < 20 | 175 (34.9) | 1.14* (1.00,1.28) | 134 (30.1) | 1.15* (1.02,1.31) |
| > 40 | 52 (10.4) | 1.08 (0.90,1.30) | 51 (11.5) | 1.06 (0.88,1.27) |
| Monocytes (%) | ||||
| 2 - 8 | 218 (51) | 1.00 | 204 (52.8) | 1.00 |
| < 2 | 209 (49) | 0.96 (0.86,1.08) | 180 (47.2) | 0.97 (0.86,1.09) |
| Neutrophils (%) | ||||
| 40 - 60 | 113 (22.6) | 1.00 | 110 (24.7) | 1.00 |
| < 40 | 12 (2.4) | 1.56* (1.10, 2.20) | 11 (2.5) | 1.38 (0.97,1.97) |
| > 60 | 376 (75.1) | 0.99 (0.87, 1.13) | 324 (72.8) | 2.98 (0.86, 1.12) |
| HCT | ||||
| Normal | 365 (73) | 1.00 | 333 (75.2) | 1.00 |
| Low | 104 (20.8) | 0.98 (0.85,1.12) | 88 (19.9) | 0.98 (0.85,1.13) |
| High | 31 (6.2) | 1.45* (1.17, 1.80) | 22 (5) | 1.17 (0.91,1.51) |
| Hb | ||||
| Normal | 382 (75.6) | 1.00 | 350 (78.1) | 1.00 |
| Low | 107 (21.2) | 1.02 (0.89,1.17) | 86 (19.2) | 1.02 (0.89,1.18) |
| High | 16 (3.2) | 1.45* (1.08, 1.95) | 12 (2.7) | 2.97 (0.68, 1.37) |
| LDH (U/L) | ||||
| ≤ 942 | 427 (96.8) | 1.00 | 389 (98.5) | 1.00 |
| > 942 | 14 (3.2) | 0.99 (0.71,1.38) | 6 (1.5) | 1.5 (0.95,2.36) |
| CPK (IU/L) | ||||
| ≤ 342 | 328 (88.4) | 1.00 | 297 (88.9) | 1.00 |
| > 342 | 43 (11.6) | 1.23* (1.01,1.50) | 37 (11.1) | 1.29* (1.06,1.57) |
| SGOT (U/L) | ||||
| ≤ 45 | 316 (70.9) | 1.00 | 291 (74.1) | 1.00 |
| > 45 | 130 (29.2) | 1.06 (0.93,1.20) | 102 (26) | 1.14 (1,1.31) |
| SGPT (U/L) | ||||
| ≤ 37 | 369 (84.4) | 1.00 | 327 (84.5) | 1.00 |
| > 37 | 68 (15.6) | 0.96 (0.82,1.14) | 60 (15.5) | 1.02 (0.86,1.2) |
| Alp (U/L) | ||||
| < 270 | 369 (88.7) | 1.00 | 326 (89.3) | 1.00 |
| ≥ 270 | 47 (11.3) | 1.00 (0.99,1.00) | 39 (10.7) | 1 (1,1) |
| K (mEq/L) | ||||
| 3.5 - 5.1 | 460 (93.3) | 1.00 | 414 (94.3) | 1.00 |
| < 3.5 | 23 (4.7) | 1.19 (0.92,1.54) | 21 (4.8) | 1.21 (0.94,1.57) |
| > 5.1 | 10 (2) | 1.07 (0.72,1.58) | 4 (0.9) | 1 (0.55,1.82) |
| Na (mEq/L, n = 440) | ||||
| 136 - 145 | 378 (76.1) | 1.00 | 340 (77.3) | 1.00 |
| < 136 | 119 (23.9) | 1.11 (0.97,1.26) | 100 (22.7) | 1.1 (0.96,1.26) |
| BS (mg/dL, n = 311) | ||||
| 70 - 105 | 145 (40.96) | 1.00 | 131 (42.12) | 1.00 |
| ≥ 105 | 209 (59.04) | 1.21* (1.05,1.39) | 180 (57.88) | 1.26* (1.09,1.45) |
| ICU admission | ||||
| No | 386 (75.5) | 1.00 | 385 (84.8) | 1.00 |
| Yes | 125 (24.5) | 1.74* (1.56, 1.95) | 69 (15.2) | 1.92* (1.68,2.18) |
Abbreviations: Systolic BP, systolic blood pressure; ECG, electrocardiogram; CRP, c-reactive protein; ESR, erythrocyte sedimentation rate; BUN, blood urea nitrogen; Cr, creatinine; PT, prothrombin time; PTT, partial thromboplastin time; WBC, white blood cells; HCT, hematocrit; Hb, hemoglobin; LDH, lactate dehydrogenase; CPK, creatine phosphokinase; SGOT, serum glutamic-oxaloacetic transaminase; SGPT, serum glutamic-pyruvic transaminase; Alp, alkaline phosphatase; BS, blood sugar; IRR, incidence risk ratio; CI, confidence interval; SPO2, Peripheral oxygen saturation with pulse oximeter; K, Potassium; Na, Sodium.
The effects of various potential risk factors on the LOSH of discharged and total patients (alive and deceased) are given in Table 2 using adjusted IRR. Based on the reported results for discharged patients in the first panel of this table, the adjusted IRR estimates of LOSH were 1.16 (95% CI: 1.01, 1.32) for females versus males, 1.22 (95% CI: 1.03, 1.44) for rural residents versus urban residents, and 1.43 (95% CI: 1.07, 1.92) for patients with diabetes and cardiovascular disease versus patients with no comorbidity. This estimate was 1.41 (95% CI: 1.23, 1.61) for patients with SPO2 lower than 88%, 0.82 (95% CI: 0.71, 0.93) for PT higher than 13 s, 1.32 (95% CI: 1.11, 1.56) for platelet counts lower than 130 × 1000 µL, 1.85 (95% CI: 1.59, 2.17) for ICU experience, and 1.18 (95% CI: 1.03, 1.36) for BS higher than 105.
Table 2.
Association Between LOSH of COVID-19 and Potential Risk Factors Using Adjusted Incidence Rate Ratio with Negative Binomial Regression
| Covariate | Alive | Alive and Dead | ||
|---|---|---|---|---|
| IRR (95% CI) | P-Value | IRR (95% CI) | P-Value | |
| Gender | ||||
| Male | 1.00 | - | 1.00 | - |
| Female | 1.16 (1.01, 1.32) | 0.032 | 1.1 (0.98, 1.24) | 0.092 |
| Age | ||||
| < 60 years | 1.00 | - | 1.00 | - |
| ≥ 60 years | 1.02 (0.89, 1.17) | 0.774 | 1.14 (1.01, 1.28) | 0.037 |
| Residence | ||||
| Urban | 1.00 | - | 1.00 | - |
| Rural | 1.22 (1.03, 1.44) | 0.024 | 1.12 (0.97, 1.29) | 0.121 |
| Comorbidity diseases | ||||
| No | 1.00 | - | 1.00 | - |
| Diabetes | 1.05 (0.87, 1.27) | 0.611 | 1.07 (0.9, 1.27) | 0.474 |
| Cardiovascular | 0.96 (0.77, 1.21) | 0.745 | 1.09 (0.92, 1.29) | 0.335 |
| Both | 1.43 (1.07, 1.92) | 0.016 | 1.4 (1.08, 1.81) | 0.011 |
| SPO2 (%) | ||||
| > 88 | 1.00 | - | 1.00 | - |
| ≤ 88 | 1.41 (1.23, 1.61) | < 0.001 | 1.36 (1.21, 1.53) | < 0.001 |
| BUN (mg/dL) | ||||
| 5 - 20 | 1.00 | - | 1.00 | - |
| > 20 | 1.11 (0.91, 1.35) | 0.291 | 0.91 (0.78, 1.07) | 0.244 |
| PT (s) | ||||
| 11 - 13 | 1.00 | - | 1.00 | - |
| > 13 | 0.82 (0.71, 0.93) | 0.003 | 0.87 (0.78, 0.98) | 0.018 |
| Platelets (× 1000 µL) | ||||
| Normal | 1.00 | - | 1.00 | - |
| Abnormal | 1.32 (1.11, 1.56) | 0.001 | 1.33 (1.16, 1.53) | < 0.001 |
| Respiratory rate (per minute) | ||||
| < 30 | 1.00 | - | 1.00 | - |
| ≥ 30 | 1.33 (0.93, 1.89) | 0.114 | 0.85 (0.64, 1.12) | 0.254 |
| K (mEq/L) | ||||
| 3.5 - 5.1 | 1.00 | - | 1.00 | - |
| < 3.5 | 1.35 (0.99, 1.86) | 0.059 | 1.29 (1.01, 1.64) | 0.042 |
| > 5.1 | 0.96 (0.52, 1.79) | 0.907 | 0.98 (0.67, 1.44) | 0.929 |
| ICU admission | ||||
| No | 1.00 | - | 1.00 | - |
| Yes | 1.85 (1.59, 2.17) | < 0.001 | 1.72 (1.48, 2) | < 0.001 |
| BS (mg/dL) | ||||
| 70 - 105 | 1.00 | - | - | - |
| ≥ 105 | 1.18 (1.03, 1.36) | 0.017 | - | - |
| Outcome | ||||
| Alive | - | - | 1.00 | - |
| Dead | - | - | 0.77 (0.63, 0.94) | 0.011 |
Abbreviations: BUN, blood urea nitrogen; PT, prothrombin time; BS, blood sugar; IRR, incidence risk ratio; CI, confidence interval; SPO2, Peripheral oxygen saturation with pulse oximeter; K, Potassium.
We observed the significant effects of some factors such as residence, comorbidity, SPO2, PT, platelet, K, and ICU admission on LOSH in all patients, similar to discharged patients (Table 2). However, their IRR estimates were slightly lower than those of discharged patients. Moreover, the adjusted IRR estimate was 1.14 (95% CI: 1.01, 1.28) for patients older than 60 years against younger patients. Although the adjusted IRR estimates of LOSH were higher for females and rural residents than in males and urban residents in all patients, the differences were not statistically significant (P = 0.092, and P = 0.121, respectively). In addition, the adjusted IRR of LOSH was 0.77 (95% CI: 0.63, 0.94, P = 0.011) for deceased patients versus discharged patients. There were no significant associations between the LOSH and other parameters such as BUN and respiratory rate.
5. Discussion
This study aimed to describe the COVID-19 patients’ characteristics in Hamadan city and evaluate the influential factors on the LOSH. The median LOSH was five and seven days, respectively, for survived and deceased patients. The IRRs of LOSH were significantly higher for the survived group than the dead group. Age differences between the dead and alive groups could be one possible reason for our findings (22).
In univariate regression, patients with pulmonary involvement and elevated ESR were more likely to have extended hospitalization. There were other significant variables for the LOSH in the survived patients, including clinical symptoms, BUN, Cr, PT, lymph, CPK, SGOT, and BS. Being a woman increased LOSH in multivariate regression. The IRR of LOSH was higher in the survived group than in the alive/dead group. Based on Pettit et al., gender was not associated with the duration of patient hospitalization (23). In another study, unadjusted estimates showed that being a man was a prominent predictor of hospitalization and disease severity; however, after adjusting for other variables, including comorbidities, this effect was no longer statistically significant (24). The differences between other studies and the present study could be attributed to the dissimilarities of treatment guidelines and study populations.
Increasing age was not associated with LOSH in the survived group; however, this variable increased the IRR of higher LOSH in the negative binomial regression for the alive/dead group. It seems that dead cases were older than survived patients. Pierce et al. similarly showed that pediatric patients had a shorter LOSH than adult patients (25). Another study showed that higher age was related to hospitalization and severe outcome in COVID-19 patients (24). In another study, patients’ age was not related to more extended hospitalization (23).
Rural residence increased the IRR of extended hospitalization for alive cases. A study in the USA showed that COVID-19 patients from low-income areas were more likely to be hospitalized (25). The longer LOSH of residents of disadvantaged areas could be attributed to the barriers to access to health care providers in villages and remote areas, lower perception of disease severity, and disease significance that might lead them to postpone seeking timely treatment.
Unadjusted regression showed that diabetes and cardiovascular disease patients had higher LOSH in alive and alive/dead groups, respectively. After adjusting for other variables, these comorbidities individually were not statistically significant, but morbidity to at least one of them increased the LOSH in two negative binomial regressions. Pettit et al. showed no statistically significant relationship between diabetes and cardiovascular disease and LOSH (23). Al-Salameh et al. examined the impact of diabetes on different clinical outcomes and found that the primary and final outcomes of COVID-19 were not statistically related to the diabetic situation of patients; however, patients with diabetes had higher LOSH than patients without diabetes (26). Mallow et al. measured the outcomes of COVID-19 patients across US hospitals and showed that patients with CRD risk factors stayed longer at the hospital than patients without CRD risk factors (27). Using self-reported data on comorbidities and population differences could explain the differences between our study findings and others.
The hospitalization period increased with decreasing SPO2. As known, SPO2 less than or equal to 93% could be related to the severity of COVID-19 (28) and admission to the ICU (29). A study in the USA showed that hypoxia was independently correlated with hospitalization (30). Benito et al., in a large cohort of patients admitted to a hospital in Spain, found that patients with Pulmonary Embolism (PE) had a lower PaO2:FiO2 ratio and more ICU admission, mechanical ventilator use, and more extended hospitalization than patients without PE (31).
In both regressions, as PT increased to more than 13, the IRR of a more extended stay at the hospital decreased. Wan et al. showed that severely infected patients had a lower level of PT (32). Another study outside Wuhan, China, showed that hospitalization for more than 14 days was associated with a higher level of PT (33). Based on a meta-analysis to examine the hemostatic parameter changes concerning the severity of COVID-19, PT was higher among severe patients than in mild cases. In addition, the elevation of PT was related to non-survive outcomes (34).
Regarding platelets, abnormality in platelet could increase the LOSH. In another study in France, COVID-19-infected patients had statistically significantly lower platelets and PT than COVID-19 patients without severe respiratory complications (35). A meta-analysis showed that the risks of severe disease and higher mortality rates were associated with low platelet counts (36). Qu et al. found that platelets and the platelet to lymphocyte ratios were related to extended hospitalization (37). Carallo et al. studied the predictors of LOSH in uncomplicated COVID-19 patients. They observed that the platelet count was inversely related to hospitalization duration (38).
Surprisingly, increasing the respiratory rate per minute, as a sign of disease severity, did not increase the LOSH. Our findings are not in line with Al-Omari et al.’s study. Their patients were not admitted to the ICU, and one of the most common symptoms was dyspnea (39). Another study in the Netherland revealed that most critically ill patients admitted to the ICU had short breaths (40).
Patients with K < 3.5 were more likely to be hospitalized for a longer time. However, K of more than 5.1 did not have a statistically significant relationship with LOSH. Liu et al. examined the lopinavir-combined regimen in COVID-19 patients. They found that many surveyed patients had hypokalemia during the early stages of hospitalization (41). Li et al. showed that hypokalemia in COVID-19 patients was related to a severe condition of this disease (42).
Patients with ICU hospitalization had more LOSH than patients without ICU hospitalization. Another study showed that young patients had longer LOSH at the ICU (22). The LOSH was different based on the level of BS. Increasing the BS level to more than 105 could lead to more extended hospitalization in alive patients. This variable did not include in the alive/dead regression model. The pathogenesis of infectious diseases could be one explanation for the way that BS could increase the LOSH due to COVID-19.
The final outcome (alive or dead) was statistically associated with LOSH in alive/dead regression. Unsurprisingly, dead cases had a lower IRR for staying at the hospital, which could be explained by more disease severity. As Rees et al. showed, the dead infected cases had a shorter LOSH than survived patients (43).
In our study, the LOSH data suffered from censoring. Many cases would be admitted lately to the hospital, which might lead to the underestimation of LOSH. Second, because of data limitations, we did not adjust the LOSH for treatment regimens of COVID-19 patients. Third, our study was retrospective, and we could not access the history of illness and variables such as the time of symptom onset. Despite these limitations, our study is one of the first studies in Iran and the only study in Hamadan province that described patient characteristics and examined driving factors for more extended hospitalization.
5.1. Conclusions
Our study added new insight into LOSH determining factors that could be used for future planning in combating the need for hospital beds. The present study revealed that some demographic, social, and clinical variables increased the IRR of more extended hospital stays. However, further studies are needed to compare the LOSH in different COVID-19 variants.