1. Introduction
Open fractures and soft tissue injuries are among the most common conditions in traumatic orthopedics. While these injuries can often be resolved through surgical treatment, postoperative complications such as bone infections and bone nonunion present significant challenges for orthopedic surgeons. Among these complications, osteomyelitis caused by infections is particularly serious, severely affecting patients' quality of life and increasing their economic and psychological burden. Although chronic osteomyelitis is typically caused by Staphylococcus aureus or Escherichia coli infections, there are reports of rare bacterial infections, such as candidiasis.
Pseudomonas luteola is a Gram-negative bacterium that was classified as a genus in 1987. It is primarily found in soil, water, and humid environmental areas. This bacterium rarely infects humans and exhibits a high degree of drug resistance (1-3). Since 1980, fewer than 30 cases of P. luteola infections have been reported worldwide, with less than five cases occurring in immunocompetent patients (4). Infections caused by P. luteola include bacteremia, sepsis, endocarditis, osteomyelitis, and peritonitis (4-9). Chronic osteomyelitis is mainly associated with Pseudomonas aeruginosa infection, and osteomyelitis caused by P. luteola is extremely rare and has not been previously reported (10).
We report a case of chronic osteomyelitis of the left tibia caused by P. luteola in a patient with normal immune function. Our aim is to increase awareness of this microorganism to facilitate early diagnosis and prevent further disease deterioration.
2. Case Presentation
A 71-year-old woman was admitted to our hospital with a sinus tract in her left calf, discharging pus for over five months. Forty years prior, the patient experienced trauma resulting in severe pain, deformity of her left calf, swelling of the affected limb, inability to stand, and limited limb movement, without symptoms such as headache, dizziness, nausea, vomiting, or altered consciousness. She underwent surgical treatment at a local hospital. Five months ago, she developed swelling and a skin ulceration approximately 0.5 cm in size, with yellowish pus discharge and dead bone at the distal end of her left calf. Seeking further diagnosis and treatment, she was admitted to our hospital with osteomyelitis of the left tibia.
Upon admission, the examination revealed a body temperature of 36.6°C, pulse of 70 beats per minute, respiration of 20 breaths per minute, blood pressure of 100/70 mmHg, and a pain score of 3. The patient's left thigh and calf muscles exhibited atrophy. The distal anterior of the left calf had a surgical scar approximately 12 cm in length. A sinus tract approximately 0.5 cm in size, with yellowish purulent secretion and dead bone outflow, surrounded by red, swollen skin, was found on the distal anterior of the left calf.
Admission blood tests showed a leukocyte count of 4.10 × 10⁹/L, neutrophil count of 2.53 × 10⁹/L, lymphocyte count of 1.26 × 10⁹/L, neutrophil percentage of 61.8%, lymphocyte percentage of 30.6%, C-reactive protein level of 0.437 mg/L, calcitoninogen level of 0.021 ng/mL, and erythrocyte sedimentation rate of 10.0 mm/h. Imaging examinations provided the following results:
2.1. X-ray Examination of the Left Lower Limb
The lower section of the left tibia was thickened with reduced bone density and a thin bone cortex, suggesting osteomyelitis (Figure 1).
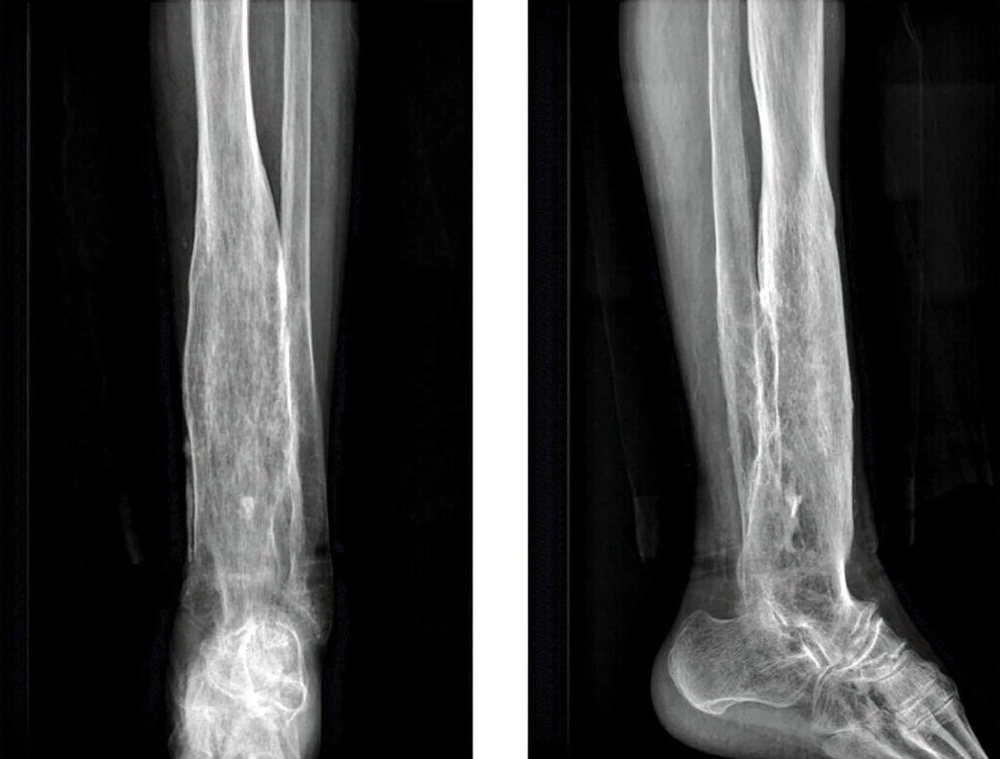
Figure 1.
X-ray frontal; X-ray lateral
2.2. CT Examination of the Left Lower Limb
The middle and distal sections of the left tibia were obviously thickened, with a thickened and rough bone cortex. The middle and distal sections of the fibula were also thickened, with a thickened and rough bone cortex. The thickened bone cortex was connected to the adjacent tibial cortex, with the thickened tibia and fibula medulla exhibiting reduced intraosteoporotic density and thinned trabeculae, along with nodular high-density shadows. Sparse and multiple nodular high-density shadows were seen in the medullary bone of the tibia and fibula, considered as a deformity of healing after chronic osteomyelitis.
2.3. MRI Examination of the Left Lower Limb
The middle and distal parts of the left tibia were obviously thickened, with a thickened and rough bone cortex. A patchy, slightly long T1 signal was observed in the medullary bone of the distal tibia. The PDWI showed low density, with a slightly high-signal shadow observed circumferentially; the edges were blurred. The adjacent medial skin and soft tissues were partially absent, with strips of long PDWI signal shadow seen in the interstitial space of the subcutaneous fat. A patchy long PDWI signal shadow was also seen in the subcutaneous fat space. The middle and distal part of the fibula was similarly thickened, with a thickened and rough bone cortex, and numerous bony fusions were present between the thickened tibia and fibula. This finding was considered a deformity of healing after a traumatic fracture with chronic osteomyelitis and sinus tract formation.
The patient exhibited symptoms of infection for over five months, characterized by persistent pus secretion from the sinus tract with dead bone, redness, and swelling around the wound, alongside normal infection indexes, consistent with chronic osteomyelitis. Cefuroxime (1.5 g) was administered intravenously one day prior to the operation. During the procedure, debridement of the left tibia and soft tissue was performed, the chronic ulcer wound was repaired, bone marrow mud was applied, and a skin flap was transplanted using a tibial flap. Necrotic material and secretions from various levels were cultured multiple times before and during the operation, revealing an abundance of P. luteola.
Drug sensitivity testing indicated that P. luteola was sensitive to piperacillin, tazobactam, tigecycline, cotrimoxazole, ceftriaxone, cefepime, imipenem, amoxicillin, amikacin, ampicillin, cefepime, and clavulanic acid, but resistant to gentamicin and ciprofloxacin (Table 1). Pathological examination of the tibia lesion tissue revealed three pieces of gray-white to gray-red irregular tissue measuring 3.5 cm × 3 cm × 1 cm, and four pieces of bone tissue measuring 6 cm × 2 cm × 1 cm. The medullary cavity contained a pile of gray-yellow crushed tissues measuring 2 cm × 1 cm × 0.3 cm.
Table 1.
Pseudomonas aeruginosa Drug Sensitivity Test
| Antibiotics | K-B Method | Sensitivity |
|---|---|---|
| Piperacillin/tazobactam | ≤ 4 | S |
| Tigecycline (antibiotic) | ≤ 0.5 | S |
| Cotrimoxazole | ≤ 20 | S |
| Gentamycin (antibiotic) | ≥ 16 | R |
| Ceftriaxone | ≤ 1 | S |
| Imipenem | ≤ 1 | S |
| Amoxicillin/clavulanic acid | ≤ 2 | S |
| Amikacin(loanword) | ≤ 2 | S |
| Ampicillin (loanword) | ≤ 2 | S |
| Ciprofloxacin | ≥ 4 | R |
| Cefepime | ≤ 1 | S |
| Tobramycin (antibiotic) | 8 | I |
| Levofloxacin | 2 | S |
Abbreviations: S, sensitive; R, resistant; I, intermediary.
Postoperatively, the patient received intravenous ceftriaxone sodium (2 g) and vancomycin (1 g) for two weeks. The patient recovered well and requested discharge from the hospital. The wound was dry, with no bloody or purulent discharge. After discharge, the patient continued with levofloxacin anti-infection treatment for six weeks. Currently, the wound is healing well, with no pain, swelling, or secretion.
3. Discussion
Pseudomonas luteola infection has a very low prevalence in the general population and is therefore often not taken seriously by patients or physicians (1, 5, 6, 11, 12). Patients with chronic osteomyelitis typically present with sinus tract abscesses that have a foul odor, elevated skin temperature, and increased levels of neutrophils, C-reactive protein (CRP), erythrocyte sedimentation rate (ESR), and procalcitonin. However, in this case, the patient's skin temperature and infection markers were all within normal ranges.
Steroid use, immunosuppressive therapy, and the presence of foreign bodies following trauma are known risk factors associated with P. luteola infection. Individuals with normal immune function are less likely to be infected with this pathogen, while immunocompromised patients or those with implanted foreign material are at significantly higher risk (2, 4, 6, 10, 13). As such, these high-risk patients must remain vigilant, and clinicians should conduct thorough medical histories and physical examinations to avoid misdiagnosis.
In this case, the patient was immunocompetent and had only undergone debridement after her initial injury. She exhibited no signs of infection for 40 years, until she developed a sinus tract abscess five months prior to presentation. Studies by Bayhan et al. (4), Connor et al. (14), Tsakris et al. (15), Berger et al. (16), and Rahav et al. (17) have demonstrated that P. luteola is generally sensitive to gentamicin. However, in this case, antimicrobial susceptibility testing showed that the pathogen was resistant to gentamicin. Globally, susceptibility patterns of P. luteola to antibiotics vary, and there is currently no consensus on optimal antibiotic selection. These discrepancies may be influenced by geographic, racial, climatic, and lifestyle factors.
To date, no reports in the international literature have documented gentamicin resistance in P. luteola. For example, Alhalimi et al. (1) summarized susceptibility results from various regions and consistently found the organism to be sensitive to gentamicin. Similarly, Tan et al. (10) described a rare case of P. luteola bacteremia with cerebral venous sinus thrombosis in a patient from the Dominican Republic, where the pathogen was sensitive to gentamicin. Su et al. (12) also reported a case of peritoneal dialysis-associated peritonitis caused by P. luteola in a patient from Taiwan, again showing sensitivity to gentamicin in antimicrobial testing.
This rare case emphasizes the potential for chronic osteomyelitis caused by P. luteola, a pathogen not commonly associated with such infections. Its management strategy remains to be clearly defined due to the rarity of such cases. This case highlights the need for trauma and orthopedic surgeons to remain aware of uncommon bacterial pathogens, as they may underlie seemingly routine infections. Heightened awareness can help reduce both underdiagnosis and misdiagnosis.