1. Introduction
The mean duration of a normal pregnancy is 40 weeks of gestation. Based on the World health organization (WHO) definitions, postdate delivery lasting 42 weeks or more is referred to postterm, and the pregnancies between 40 and 41 + 6 weeks as late-term deliveries (1). Full term pregnancy is defined by the American Congress of Obstetricians and Gynecologists as 39 to 40 weeks of gestation (2, 3).
More than 40% of all pregnant mothers give birth after 40 weeks (1). The pregnant population > 41 weeks constitutes 15% - 20% of all pregnancies (4) and postterm birth rates is observed in a range of 0.4% to 8.1% (5). Postdate deliveries are associated with fetal, neonatal, and maternal risks (6, 7).
Fetal and neonatal complications of postterm and late-term pregnancies are macrosomia, fetal dysmaturity, increased risk of umbilical cord compression due to oligohydramnios, abnormal antepartum or intrapartum fetal heart rate patterns due to placental insufficiency or cord compression, meconium passage and aspiration, and prenatal deaths (6-8). The long-term effects of postterm birth are unclear, but may include neurologic risks such as epilepsy and cerebral palsy (9, 10).
Maternal risks of postterm pregnancy include an increased frequency of failed induction, 3rd and 4rd degree perinea lacerations, infection, and postpartum hemorrhage (9-12). Management of pregnant mothers with no onset of labor ranges from expectant management consisting of intensive monitoring of mother and fetus to induction of labor (1). The American College of Obstetricians and Gynecologists recommends induction of labor after 42 weeks of gestation, but considers induction at 41 to 42 weeks reasonable (13).
Most of the obstetricians prefer expectant management with monitor fetal well-being, twice weekly in 40 to 41weeks and they choose induction of pregnancies at 41weeks of gestation to reduce prenatal mortality and morbidity. They suggest that induction of labor at 40 to 41weeks in uncomplicated pregnancy has overall similar outcomes compared with expectant management and termination of the pregnancy, which is indicated when results of the recent examinations indicate a risk for mother or child. They believe that this is a reasonable approach, because of the low absolute rate of fetal death in late-term and the relatively high number of inductions that would be required to prevent one prenatal death (14-18).
In contrast, prenatal mortality and morbidity increase with increasing gestational age after 40 weeks (5). For mothers at 40 weeks of gestation, some obstetricians suggest induction rather than expectant management to reduce prenatal mortality and morbidity or cesarean delivery rates (14, 17, 19).
The current study compared neonatal and maternal complications in mothers with 38 to 40, 40 to 41, and > 41 weeks of gestation.
2. Methods
After approval by the ethics committee, the current prospective, cohort study was performed on1180 singleton and uncomplicated pregnant mothers admitted for labor in Arash hospital in Tehran, Iran, from 2014 to 2015. Mothers with singleton, cephalic, and low risk pregnancies ≥ 38 weeks of gestation were included.
Females with underlying diseases, drug users, previous cesarean delivery, and fetus with anomaly in ultrasound, multiple gestations, non-cephalic presentations, and complicated pregnancies were excluded.
Pregnant mothers were divided into 3 groups: Group 1 included 750 cases in 38 to 40 weeks, group 2 included 250 cases in 40 to 41weeks, and group 3 included 180 cases in more than 41 weeks of gestation. Pregnant females were observed for vital signs, progress of labor, and electronic monitoring of fetal heart rate. Mode of delivery, fetal weight, Apgar score in 1 and 5 minutes, fetal distress, meconium passage, meconium aspiration in fetus, neonatal intensive care unit (NICU) admission, maternal infection, and postpartum hemorrhage were recorded as outcomes of the study.
2.1. Data Analysis
All data analyses were conducted using SPSS version 21.0 for Windows (SPSS Inc., Chicago, IL, USA). Descriptive statistics for continuous variables were presented as mean ± standard deviation (SD) and for categorical variables as numbers (percentage). The baseline characteristics, primary and secondary outcomes of the 3 groups were compared using one-way ANOVA test (followed by Scheffe post hoc test) for continuous variables and the Chi-square test for categorical variables. All statistical tests were 2-sided and the level of statistical significance was 0.05.
3. Results
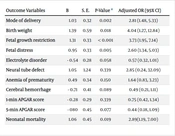
Baseline and demographic characteristics are shown in Table 1. There was significant statistical differences in the rate of fetal distress (P < 0.001), meconium passage (P = 0.001), meconium aspiration syndrome (P < 0.001), Apgar score ≤ 3 in new born at 1 (P = 0.025) and 5 minutes (P < 0.001), and required NICU admission (P < 0.001) among the 3 groups (Table 1).
Table 1.
Baseline and Demographic Characteristics in the Study Groupsa
| 38 - 40 Weeks of Gestation (n = 750) | 40 - 41 Weeks of Gestation (n = 250) | Above 41 Weeks of Gestation (n = 180) | P Value | |
|---|---|---|---|---|
| Age, y | 27.06 ± 5.73 | 27.50 ± 5.34 | 27.41 ± 5.39 | 0.487 |
| Birth weight, g | 3398.13 ± 619.84 | 3433.00 ± 542.88 | 3421.11 ± 554.63 | 0.693 |
| Parity | 0.123 | |||
| 1 | 382 (50.9) | 128 (51.2) | 92 (51.1) | |
| ≥ 2 | 368 (49.1) | 122 (48.8) | 88 (48.9) | |
| Birth weight ≥ 4000 g | 0.959 | |||
| Yes | 147 (19.6) | 50 (20) | 34 (18.9) | |
| No | 603 (80.4) | 200 (80) | 146 (81.1) | |
| 1-Minute Apgar score | 0.025 | |||
| 0 - 3 | 18 (2.4) | 12 (4.8) | 11 (6.1) | |
| 4 - 6 | 116 (15.5) | 42 (16.8) | 37 (20.6) | |
| ≥ 7 | 616 (82.1) | 196 (78.4) | 132 (73.3) | |
| 5-Minute Apgar score | < 0.001 | |||
| 0 - 3 | 5 (0.7) | 7 (2.8) | 6 (3.3) | |
| 4 - 6 | 12 (1.6) | 10 (4) | 13 (7.2) | |
| ≥ 7 | 733 (97.7) | 233 (93.2) | 161 (89.4) | |
| Fetal distress | < 0.001 | |||
| Yes | 12 (1.6) | 11 (4.4) | 19 (10.6) | |
| No | 738 (98.4) | 239 (95.6) | 161 (89.4) | |
| Meconium passage | < 0.001 | |||
| Yes | 12 (1.6) | 20 (8) | 25 (13.9) | |
| No | 737 (98.4) | 230 (92) | 155 (86.1) | |
| Meconium aspiration | < 0.001 | |||
| Yes | 7 (0.9) | 14 (5.6) | 18 (10) | |
| No | 743 (99.1) | 236 (94.4) | 162 (90) | |
| NICU admission | < 0.001 | |||
| Yes | 12 (1.6) | 10 (4) | 12 (6.66) | |
| No | 738 (98.4) | 240 (96) | 168 (93.34) | |
| Cesarean section | < 0.001 | |||
| Yes | 102 (13.6) | 62 (24.8) | 60 (33.3) | |
| No | 648 (86.4) | 188 (75.2) | 120 (66.7) | |
| Postpartum hemorrhage | 0.412 | |||
| Yes | 20 (2.66) | 7 (2.8) | 5 (2.77) | |
| No | 730 (97.34) | 243 (97.2) | 175 (97.23) | |
| Maternal infection | < 0.001 | |||
| Yes | 25 (3.33) | 30 (12) | 28 (15.55) | |
| No | 725 (96.67) | 220 (88) | 152 (84.45) |
aValues are expressed as mean ± SD or No. (%).
Also, there were significant differences among the 3 groups in the rate of cesarean section (P < 0.001) and maternal infection (P = 0.001) (Table 1). There were no significant difference in the fetal weight ≥ 4 kg and postpartum hemorrhage among females (Table 1).
Results were also compared between group 1 and group 2 (Table 2).
Table 2.
Baseline and Demographic Characteristics in Groups 1 and 2 of the Studya
| 38 - 40 Weeks of Gestation (n = 750) | 40 - 41 Weeks of Gestation (n = 250) | P Value | |
|---|---|---|---|
| Age, y | 27.06 ± 5.73 | 27.50 ± 5.34 | 0.287 |
| Birth weight, g | 3398.13 ± 619.84 | 3433.00 ± 542.88 | 0.428 |
| Parity | 0.312 | ||
| 1 | 382 (50.9) | 128 (51.2) | |
| ≥ 2 | 368 (49.1) | 122 (48.8) | |
| Birth weight ≥ 4000 g | 0.890 | ||
| Yes | 147 (19.6) | 50 (20) | |
| No | 603 (80.4) | 200 (80) | |
| 1-Minute Apgar score | 0.127 | ||
| 0 - 3 | 18 (2.4) | 12 (4.8) | |
| 4 - 6 | 116 (15.5) | 42 (16.8) | |
| ≥ 7 | 616 (82.1) | 196 (78.4) | |
| 5-Minute Apgar score | 0.002 | ||
| 0 - 3 | 5 (0.7) | 7 (2.8) | |
| 4 - 6 | 12 (1.6) | 10 (4) | |
| ≥ 7 | 733 (97.7) | 233 (93.2) | |
| Fetal distress | 0.011 | ||
| Yes | 12 (1.6) | 11 (4.4) | |
| No | 738 (98.4) | 239 (95.6) | |
| Meconium passage | < 0.001 | ||
| Yes | 12 (1.6) | 20 (8) | |
| No | 738 (98.4) | 230 (92) | |
| Meconium aspiration | < 0.001 | ||
| Yes | 7 (0.9) | 14 (5.6) | |
| No | 743 (99.1) | 236 (94.4) | |
| NICU admission | < 0.001 | ||
| Yes | 12 (1.6) | 10 (4) | |
| No | 738 (98.4) | 240 (96) | |
| Postpartum hemorrhage | 0.314 | ||
| Yes | 20 (2.66) | 7 (2.8) | |
| No | 730 (97.34) | 243 (97.2) | |
| Maternal infection | < 0.001 | ||
| Yes | 25 (3.33) | 30 (12) | |
| No | 725 (96.67) | 220 (88) | |
| Cesarean section | < 0.001 | ||
| Yes | 102 (13.6) | 62 (24.8) | |
| No | 648 (86.4) | 188 (75.2) |
aValues are expressed as mean ± SD or No. (%).
The frequency of fetal distress was lower in group 1 compared with group 2 (1.6% versus 4.4%; P = 0.011). The meconium passage and meconium aspiration syndrome were statistically lower in group 1 as compared with group 2 (1.6% versus 8%; P <0.001 for meconium passage, and 0.9% versus 5.6%; P < 0.001 for meconium aspiration syndrome).
The rate of cesarean section was more frequent in group 2 compared with group 1 (24.8% versus 13.6%; P < 0.001).
Results were also compared between group 1 and group 3 (Table 3).
Table 3.
Baseline and Demographic Characteristics in Groups 1 and 3 of the Studya
| 38 - 40 Weeks of Gestation (n = 750) | Above 41 Weeks of Gestation (n = 180) | P Value | |
|---|---|---|---|
| Age, y | 27.06 ± 5.73 | 27.41 ± 5.39 | 0.451 |
| Birth weight, g | 3398.13 ± 619.84 | 3421.11 ± 554.63 | 0.649 |
| Parity | 0.412 | ||
| 1 | 382 (50.9) | 92 (51.1) | |
| ≥ 2 | 368 (49.1) | 88 (48.9) | |
| Birth weight ≥4000 g | 0.829 | ||
| Yes | 147 (19.6) | 34 (18.9) | |
| No | 603 (80.4) | 146 (81.1) | |
| 1-Minute Apgar score | 0.006 | ||
| 0 - 3 | 18 (2.4) | 11 (6.1) | |
| 4 - 6 | 116 (15.5) | 37 (20.6) | |
| ≥ 7 | 616 (82.1) | 132 (73.3) | |
| 5-Minute Apgar score | < 0.001 | ||
| 0 - 3 | 5 (0.7) | 6 (3.3) | |
| 4 - 6 | 12 (1.6) | 13 (7.2) | |
| ≥ 7 | 733 (97.7) | 161 (89.4) | |
| Fetal distress | < 0.001 | ||
| Yes | 12 (1.6) | 19 (10.6) | |
| No | 738 (98.4) | 161 (89.4) | |
| Meconium passage | < 0.001 | ||
| Yes | 12 (1.6) | 25 (13.9) | |
| No | 738 (98.4) | 155 (86.1) | |
| Meconium aspiration | < 0.001 | ||
| Yes | 7 (0.9) | 18 (10) | |
| No | 743 (99.1) | 162 (90) | |
| NICU admission | < 0.001 | ||
| Yes | 12 (1.6) | 12(6.66) | |
| No | 738 (98.4) | 168 (93.34) | |
| Postpartum hemorrhage | 0.254 | ||
| Yes | 20 (2.66) | 5 (2.77) | |
| No | 730 (97.34) | 175 (97.23) | |
| Maternal infection | < 0.001 | ||
| Yes | 25 (3.33) | 28 (15.55) | |
| No | 725 (96.67) | 152 (84.45) | |
| Cesarean section | < 0.001 | ||
| Yes | 102 (13.6) | 60 (33.3) | |
| No | 648 (86.4) | 120 (66.7) |
aValues are expressed as mean ± SD or No. (%).
The rate of fetal distress was significantly lower in group 1 than group 3 (1.6% versus 10.9%; P < 0.001).
Also meconium passage and meconium aspiration syndrome were significantly lower in group 1 than group 3(1.6% versus 13.9%; P < 0.001 for meconium passage, and 0.9% versus 10%; P < 0.001 for meconium aspiration syndrome).
The rate of cesarean section was significantly higher in group 3 compared with group 1 (5.6% versus 10%; P < 0.001).
The rate of fetal distress (4.4% versus 10.6%; P = 0.013) and meconium passage (33.3% versus 13.6%; P < 0.001) were significantly higher in group 3 compared with group 2. There were no significant difference in the rate of meconium aspiration syndrome, Apgar score ≤ 3 of newborn at 1and 5 minutes, NICU admission, rate of cesarean section, maternal infection, and postpartum hemorrhage between the groups 2 and 3 (Table 4).
Table 4.
Baseline and Demographic Characteristics in Groups 2 and 3 of the Studya
| 40 - 41 Weeks of Gestation (n = 250) | Above 41 Weeks of Gestation (n = 180) | P Value | |
|---|---|---|---|
| Age, y | 27.50 ± 5.34 | 27.41 ± 5.39 | 0.874 |
| Birth weight, g | 3433.00 ± 542.88 | 3421.11 ± 554.63 | 0.824 |
| Parity | 0.584 | ||
| 1 | 128 (51.2) | 92 (51.1) | |
| ≥ 2 | 122 (48.8) | 88 (48.9) | |
| Birth weight ≥ 4000 g | 0.774 | ||
| Yes | 50 (20) | 34 (18.9) | |
| No | 200 (80) | 146 (81.1) | |
| 1-Minute Apgar score | 0.474 | ||
| 0 - 3 | 12 (4.8) | 11 (6.1) | |
| 4 - 6 | 42 (16.8) | 37 (20.6) | |
| ≥ 7 | 196 (78.4) | 132 (73.3) | |
| 5-Minute Apgar score | 0.318 | ||
| 0 - 3 | 7 (2.8) | 6 (3.3) | |
| 4 - 6 | 10 (4) | 13 (7.2) | |
| ≥ 7 | 233 (93.2) | 161 (89.4) | |
| Fetal distress | 0.013 | ||
| Yes | 11 (4.4) | 19 (10.6) | |
| No | 239 (95.6) | 161 (89.4) | |
| Meconium passage | 0.049 | ||
| Yes | 20 (8) | 25 (13.9) | |
| No | 230 (92) | 125 (86.1) | |
| Meconium aspiration | 0.041 | ||
| Yes | 14 (5.6) | 18 (10) | |
| No | 236 (94.4) | 162 (90) | |
| NICU admission | |||
| Yes | 10 (4) | 12 (6.66) | 0.612 |
| No | 240 (96) | 168 (93.34) | |
| Postpartum hemorrhage | 0.387 | ||
| Yes | 7 (2.8) | 5 (2.77) | |
| No | 243 (97.2) | 175 (97.23) | |
| Maternal infection | 0.213 | ||
| Yes | 30 (12) | 28 (15.55) | |
| No | 220 (88) | 152 (84.45) | |
| Cesarean section | 0.053 | ||
| Yes | 62 (24.8) | 60 (33.3) | |
| No | 188 (75.2) | 120 (66.7) |
aValues are expressed as mean ± SD or No. (%).
4. Discussion
In the current study, the rate of fetal distress, meconium passage, meconium aspiration syndrome, and required NICU admission increased after 40 weeks, compared with earlier weeks of gestation; there was significant differences in the rate of cesarean section and maternal infection among the 3 groups, but prenatal adverse outcomes, in group 2 with 40 to 41 weeks of gestation, such as the rate of meconium aspiration syndrome, Apgar score ≤ 3 of newborn at 1 and 5minutes, NICU admission, and the rate of cesarean section were similar to those of group 3 with > 41 weeks of gestation.
Some researchers suggest that induction of labor and early termination of term pregnancies had a lower incidence of meconium aspiration, low Apgar scores, postmaturity syndrome, and fetal distress than the patients managed with antepartum fetal testing (15-17).
Mishanina et al. presented benefits for the fetus and no increased risk of maternal death among females with induced labor than the ones with managed expectantly in term and postterm gestations (19).
The results of the current study were similar to those of the following studies.
Gulmezoglu et al. showed that the risk of prenatal mortality was lower in pregnancy termination at 41 to 42 weeks of gestation than with expectant management, but did not achieve statistical significance (15). Fortunately, the current study did not have prenatal mortality.
Also, Caughey et al. suggested that females who were expectantly managed were more likely to have meconium-stained amniotic fluid than the ones who were electively induced (17). Similarly in the current study, the rate of meconium-stained amniotic fluid was higher in mothers > 40 weeks compared with that of the ones with less than 40 weeks of gestation.
But others reported induction of labor at full term in uncomplicated singleton has overall similar outcomes compared to expectant management (14, 19, 20). In addition, meta-analysis did not find a significant difference in NICU admissions between pregnancies induced at 41 weeks of gestation and the ones with managed expectantly (15), which suggest that neonatal morbidity does not rise substantially postterm. There were significant differences in NICU admissions among the 3 groups.
Some researchers reported that the risk of cesarean delivery was lower among females whose labor was induced than among the ones with managed expectantly in term and postterm gestations. There were benefits for the fetus, and no increased risk of maternal death. They presented that the low cesarean rate with earlier gestational age may be due to lower rates of macrosomia and abnormal intrapartum fetal heart rate tracings with earlier delivery (14, 19, 21).
In the current study, the rate of cesarean delivery was lower before 40 weeks of gestation compared with 40 to 41 weeks and also, in 40 to 41 weeks compared with above 41 weeks; the rate of newborn with the weight > 4000 g was similar in the 3 groups, but the rates of fetal distress and meconium passage were significantly different among the 3 groups, and were the cause of increased cesarean section in groups 2 and 3 compared with group 1. In the current study, the rate of fetal distress and meconium passage were similar in group 40 to 41 weeks and the group above 41 weeks; therefore, the rate of cesarean delivery was also similar between the 2 groups.
Also, some researchers reported that the rate of operative vaginal deliveries increased with delivery after 40 weeks, and the higher incidence of 3rd or 4rd degree lacerations, secondary postpartum bleeding, and prolonged labor were observed between 40 and 42 weeks, compared with before 40 weeks of gestation (1, 14, 19).
In contrast, some studies reported no difference in the risk of cesarean delivery among females who delivered at term, compared with females who delivered late-term and postterm (15, 22). Thangarajah et al. reported that induction of labor in late- and postterm pregnancies was associated with a significantly higher cesarean section rate, compared with expectant management (23).
4.1. Conclusions
Results of the current study suggested that prenatal and maternal morbidity and the rate of cesarean sections increased after 40 weeks of gestation, compared with 38 to 40 weeks; therefore, planned early delivery is recommend versus expectant management of term and full term pregnancies.