
1. Background
Pulmonary hypoplasia is a significant decrease in lung volume in comparison to the normal volume for gestational age (1). Depending on the severity of the condition it could lead to impaired respiratory function, postnatal intensive care or incompatibility with life. Pulmonary hypoplasia can be caused by various etiologies such as oligohydramnios, congenital diaphragmatic hernia, pulmonary masses, chest wall deformities, and hydrothorax (2). For some of these conditions, prenatal intervention is available based on the degree of pulmonary hypoplasia. In all these conditions, prognosis and proper management depends on the volume of remaining normal lung tissue. Thus, precise prenatal diagnosis and quantification of pulmonary hypoplasia is particularly crucial.
Three-dimensional ultrasound and magnetic resonance imaging (MRI) are the two well-established modalities that are clinically used to measure fetal lung volume. While MRI is not universally available, ultrasound is generally limited by poor acoustic distinction of the lung tissue from adjacent structures (3, 4). Ultrasound might also be technically challenging or impossible to perform with diagnostic quality in patients with oligohydramnios or large abdomen.
Technical advances in MRI including fast pulse sequences (5), especially single-shot fast spin echo imaging (6-8) has made MR imaging of the moving fetus possible. These sequences are less motion sensitive than older sequences and could lead to detailed anatomical evaluation including lung volume measurement. The possibility for pulmonary hypoplasia could be evaluated by comparing the fetal lung volume with a normal range for gestational age. Multiple studies have tried to establish normal lung volumes for various gestational ages (9-13). However, the results are not uniform between studies; with variations most noticeable between different populations (14, 15). Moreover, due to paucity of data on early gestation and widespread second trimester screening, there is an increasing need for establishing normal values for early mid-trimester lung volume.
2. Objectives
In the present study, we aimed to measure the volume of the fetal lung using MR imaging to establish a reference data in our population. To our knowledge no such study has been performed in the Middle East.
3. Patients and Methods
3.1. Patient Population
Between April 2014 and March 2017, 342 pregnant women were referred to a single tertiary care hospital (Shahid Faghihi Hospital, Shiraz, Iran) for fetal MRI. Suspicion for central nervous system diseases such as ventriculomegaly and morbidly adherent placenta were the most frequent indications for referral. Other morphologic abnormalities such as renal disease, echogenic bowel, dilated stomach, abdominal mass, intrauterine growth retardation (IUGR), inadequate amniotic fluid, hydropes, and polydactyly were the remaining causes of referral. Among them, some were excluded due to intervening factors (which are shown in Figure 1) and the total number of 241 cases, aged 30.5 ± 5.51 years (range: 18 - 45) with a gestational age of 26 ± 5.86 weeks (18 - 36), were recruited at the end. All the participants had singleton pregnancies. Gestational age was confirmed and determined with routine first-trimester US. Normality of fetuses was confirmed by a minimum of one year postpartum follow-up. The study protocol was approved by the local institutional review board and informed consent was waived by the institutional ethics committee. MRI was performed within 10 days of the ultrasound.
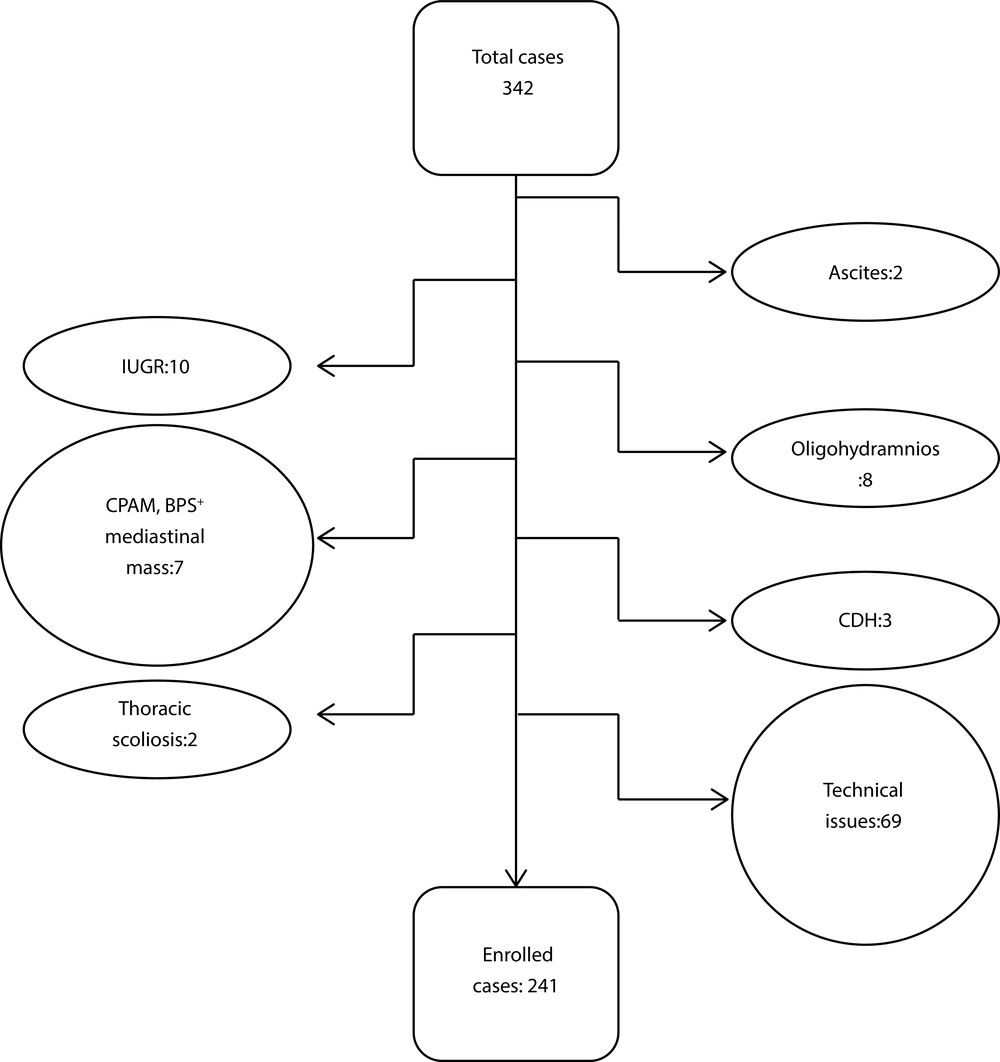
Figure 1.
Flow chart illustrates study selection based on the exclusion criteria (Abbreviations: BPS, bronchopulmonary sequestration; CDH, congenital diaphragmatic hernia; CPAM, congenital pulmonary airway malformation; IUGR, intrauterine growth retardation).
3.2. MRI
A 1.5 T Siemens Avanto scanner with a 4-channel body coil was used for all MRIs.
Sequences including T2 half-Fourier acquisition single-shot turbo spin-echo (HASTE) images were obtained with 4-6.5-mm-thick slices in the axial planes to the fetus’s lung. A single radiologist with 7 years’ experience in fetal imaging investigated the existing images for possible abnormality meeting the exclusion criteria.
T2-weighted images were obtained by using T2W HASTE images, half-fourier acquisition single-shot turbo spin echo images with a matrix of 256 × 160 - 256. A minimal bandwidth was used for all sequences. The acquisition time was 15 - 30 seconds. Section thickness and intersection gap were 4 - 6.5 mm and 4.4 - 14.4 mm, respectively. T2-weighted images were acquired in transverse planes with respect to the fetal thorax. In the presence of fetal anomalies, additional MR imaging of the fetus in a transverse, coronal and axial plane was performed. If a particular sequence had too much motion, then it was not used for the review.
3.3. Variables
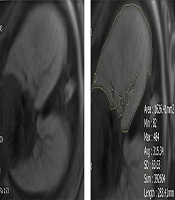
One reader selected images acquired with HASTE sequences that contained the complete fields of both lungs without motion artifacts. The cross-sectional area of the lung was measured on each transverse section by manual tracing (Figure 2). The hila of the lung, mediastinum and heart were excluded from lung volume measurement. Fetal lung volume (FLV) measurements were performed twice on separate episodes without knowledge of prior measurements. Average of the two separate measurements was considered the lung volume.
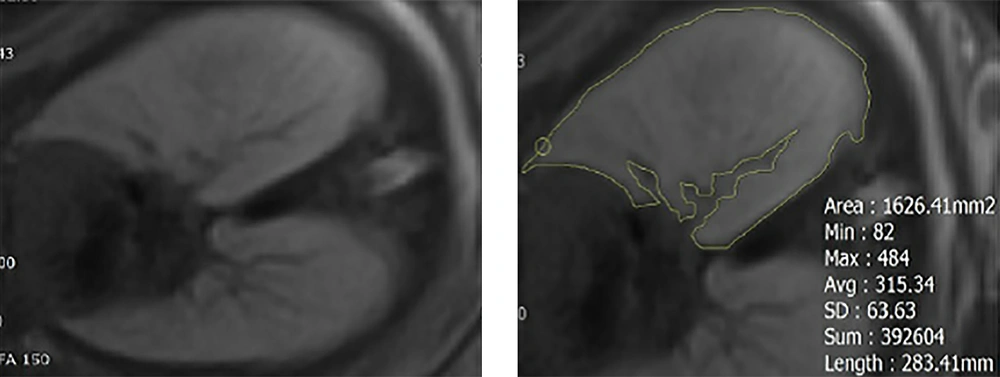
Figure 2.
Fetal MRI demonstrating appropriate measurement of lung in the cross-sectional plane
To calculate the volume for each section, we multiplied the value of the sums of cross-sectional areas of different slices by the sum of the section thickness and intersection gap.
3.4. Statistical Analysis
Statistical analyses were performed using SPSS software (Statistical Package for the Social Sciences, version 10.5; Chicago, Ill). Mean total fetal lung volume, median, standard deviation (SD), minimum, and maximum were calculated for each gestational week. Afterwards, a one-sample t-test was done to compare the mean total fetal lung volume at each gestational week with the expected mean total fetal lung volume predicted by the formula by Rypens et al. (16), Meyers et al. (17), and Osada et al. (9). P value was considered statistically significant for values less than 0.05. To acquire a best-fit formula for the mean total fetal lung volume based on each gestational week with 95% CI, we used the regression model applied by Rypens et al. (16).
4. Results
Total lung volume ranged from 3.82 to 109.5 mL from 18 to 36 weeks GA (Table 1). The relationship between the total lung volume and gestational age is shown in Figure 2 The best fit for the lung volume was the regression line represented by the equation V = 0.002 × (GA2.913), in which V is the lung volume and GA is the gestational weeks.
Table 1.
Lung Volume (LV) Based on Gestational Age (GA)
| GA | Mean LV | Number | Standard deviation | Median | Minimum | Maximum |
|---|---|---|---|---|---|---|
| 18.00 | 6.8382 | 9 | 1.97930 | 6.5611 | 3.82 | 9.97 |
| 19.00 | 9.5792 | 24 | 3.04680 | 9.0430 | 5.52 | 19.12 |
| 20.00 | 11.1818 | 28 | 2.53224 | 10.6112 | 7.54 | 17.33 |
| 21.00 | 12.4675 | 17 | 2.08773 | 12.5720 | 8.25 | 17.07 |
| 22.00 | 15.0990 | 10 | 4.20479 | 14.9434 | 9.21 | 22.85 |
| 23.00 | 16.7634 | 11 | 2.51566 | 17.1626 | 12.59 | 20.88 |
| 24.00 | 21.2190 | 11 | 4.20695 | 20.1747 | 15.11 | 31.12 |
| 25.00 | 21.6821 | 13 | 1.80661 | 22.5837 | 18.38 | 23.61 |
| 26.00 | 29.4592 | 9 | 5.46292 | 29.4306 | 22.29 | 37.13 |
| 27.00 | 34.9165 | 5 | 4.98786 | 35.4412 | 26.92 | 40.53 |
| 28.00 | 28.1973 | 9 | 7.03799 | 27.6728 | 16.76 | 35.97 |
| 29.00 | 37.0923 | 10 | 10.54665 | 36.9234 | 20.62 | 51.69 |
| 30.00 | 38.9204 | 9 | 10.42489 | 41.5136 | 26.24 | 59.55 |
| 31.00 | 40.5029 | 11 | 12.34308 | 40.3449 | 18.94 | 62.59 |
| 32.00 | 43.3220 | 19 | 8.16032 | 42.4672 | 31.24 | 62.91 |
| 33.00 | 47.7547 | 14 | 9.24501 | 51.6251 | 30.32 | 58.27 |
| 34.00 | 56.7422 | 7 | 24.78870 | 52.4480 | 36.32 | 109.50 |
| 35.00 | 58.2047 | 9 | 11.89166 | 57.4312 | 43.44 | 79.48 |
| 36.00 | 52.8723 | 11 | 13.98617 | 52.8900 | 32.53 | 76.03 |
| Total | 27.6343 | 236 | 18.09921 | 22.3696 | 3.82 | 109.50 |
FLV increased with gestational age, as illustrated in the Figures 3 and 4, from 18 weeks of GA to 36 weeks, but not with a linear distribution. A decrease in the mean total fetal lung volume from 27 to 28 weeks and 35 to 36 weeks was noted. The later one was also reported in Meyers et al. (17).
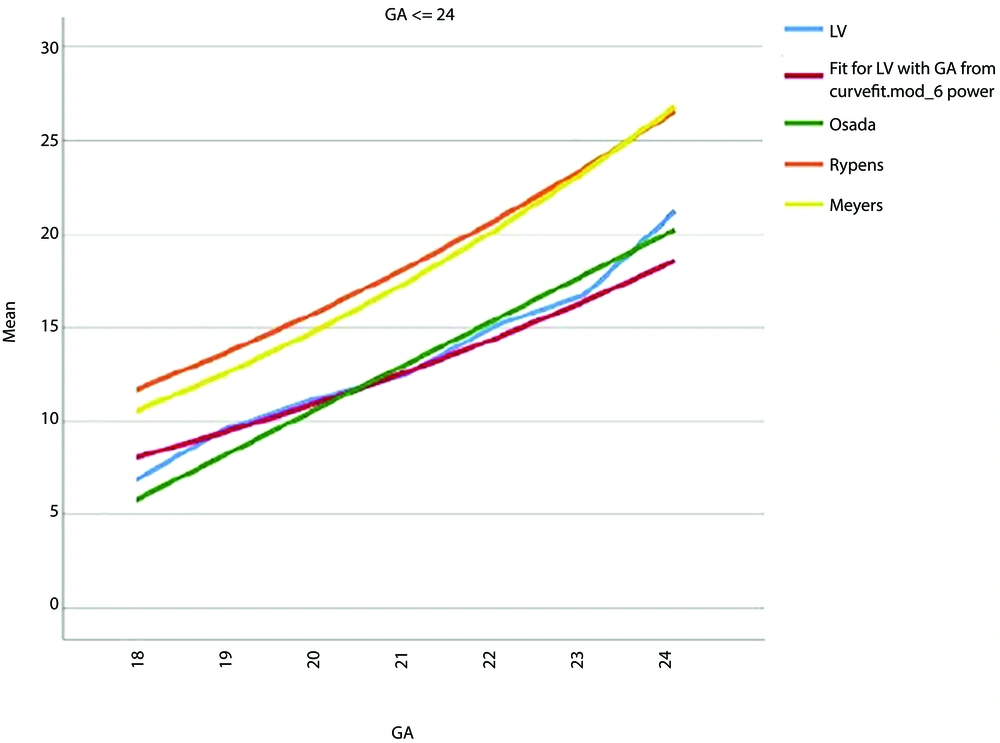
Figure 3.
Comparison of normal fetal lung volume at different gestational ages (GA ≤ 24 w). The blue line is indicating the raw data of acquired lung volume in the fetuses. By means of the regression model applied by Rypens et al. (16), a best-fit formula for the mean total fetal lung volume based on each gestational week with 95% CI (shown by the red line) was achieved.
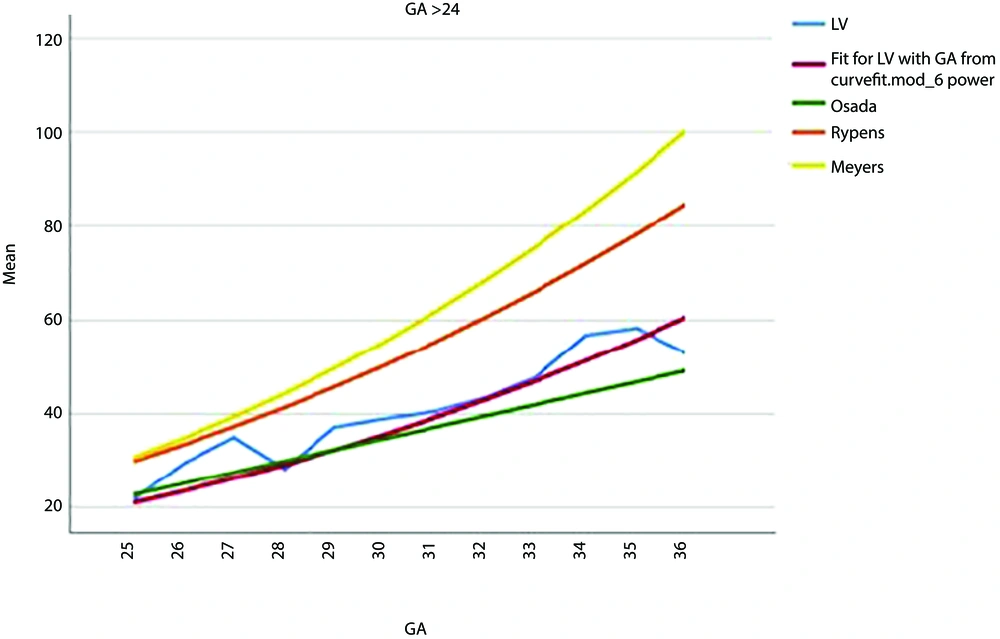
Figure 4.
Comparison of normal fetal lung volume at different gestational ages (GA > 24 w). The blue line is indicating the raw data of acquired lung volume in the fetuses. By means of the regression model applied by Rypens et al. (16), a best-fit formula for the mean total fetal lung volume based on each gestational week with 95% CI (shown by the red line) was achieved.
Based on Table 2, comparing the mean total fetal lung volume with the expected total fetal lung volume for each gestational age week by the Osada et al. (9), we found that our data distribution resembled those of Osada et al. (9) at every gestational age week except for weeks 19, 26, 27, 33, and 35. The differences between the two data sets were not statistically significant, except for the mentioned weeks. Comparison of our data with those of the studies conducted by Rypens et al. (16) and Meyers et al. (17) revealed a noticeable difference in the acquired lung volume except for week 26, and 27 [compared to Rypens et al. (16)] and 27 [compared to Meyers et al. (17)].
Table 2.
| GA | Mean | Rypens et al. (16) | P value | Meyers et al. (17) | P value | Osada et al. (9) | P value |
|---|---|---|---|---|---|---|---|
| 18.00 | 6.8382 | 11.6735 | 0.000 | 10.5117 | 0.001 | 5.7800 | 0.147 |
| 19.00 | 9.5792 | 13.6256 | 0.000 | 12.5337 | 0.000 | 8.1900 | 0.036 |
| 20.00 | 11.1818 | 15.7785 | 0.000 | 14.8104 | 0.000 | 10.6000 | 0.235 |
| 21.00 | 12.4675 | 18.1413 | 0.000 | 17.3587 | 0.000 | 13.0100 | 0.300 |
| 22.00 | 15.0990 | 20.7229 | 0.002 | 20.1957 | 0.004 | 15.4200 | 0.815 |
| 23.00 | 16.7634 | 23.5322 | 0.000 | 23.3388 | 0.000 | 17.8300 | 0.190 |
| 24.00 | 21.2190 | 26.5782 | 0.002 | 26.8055 | 0.001 | 20.2400 | 0.458 |
| 25.00 | 21.6821 | 29.8696 | 0.000 | 30.6135 | 0.000 | 22.6500 | 0.077 |
| 26.00 | 29.4592 | 33.4153 | 0.061 | 34.7808 | 0.019 | 25.0600 | 0.042 |
| 27.00 | 34.9165 | 37.2239 | 0.360 | 39.3255 | 0.120 | 27.4700 | 0.029 |
| 28.00 | 28.1973 | 41.3041 | 0.001 | 44.2658 | 0.000 | 29.8800 | 0.494 |
| 29.00 | 37.0923 | 45.6646 | 0.030 | 49.6203 | 0.005 | 32.2900 | 0.184 |
| 30.00 | 38.9204 | 50.3139 | 0.011 | 55.4075 | 0.001 | 34.7000 | 0.259 |
| 31.00 | 40.5029 | 55.2606 | 0.003 | 61.6463 | 0.000 | 37.1100 | 0.383 |
| 32.00 | 43.3220 | 60.5132 | 0.000 | 68.3556 | 0.000 | 39.5200 | 0.057 |
| 33.00 | 47.7547 | 66.0802 | 0.000 | 75.5545 | 0.000 | 41.9300 | 0.035 |
| 34.00 | 56.7422 | 71.9699 | 0.155 | 83.2623 | 0.030 | 44.3400 | 0.234 |
| 35.00 | 58.2047 | 78.1908 | 0.001 | 91.4984 | 0.000 | 46.7500 | 0.020 |
| 36.00 | 52.8723 | 84.7513 | 0.000 | 100.2823 | 0.000 | 49.1600 | 0.399 |
Abbreviations: GA, gestational age.
aP value < 0.05 is significant.
5. Discussion
One of the main predictors of respiratory function in the newborn is presence of an adequate area of the gas-exchanging epithelium. This surface area is directly correlated with fetal lung volume. Therefore, it is rational to evaluate the fetal lung volumes in the uterus with the purpose of detection of hypoplastic lungs (18).
Pulmonary hypoplasia is associated with a high rate of neonatal morbidity and mortality. For selected causes of pulmonary hypoplasia, prenatal intervention is available. For all prognoses, management and follow-up schedules depend on the degree of hypoplasia and volume of the remaining lung tissue. Thus, such fetuses could benefit from antenatal detection of restricted pulmonary development. In order to call a lung small-sized or underdeveloped, comparison with a valid, population based, normal reference value is necessary.
Since the 1980s (19), fetal MR has been used as a competent, non-invasive, and harmless modality to study fetal lung development after 18 gestational weeks (GW) in the uterus. In addition to the prior role of MRI in the evaluation of lung growth, the high resolution and tissue contrast of MRI allows us to study the structure of the fetal lung and more detailed fetal pulmonary pathologies. So far, few studies have applied fetal MR lung volumetry to evaluate the lung volume of normal fetuses (12, 20) to establish a reference data for detection of fetuses with abnormally small lungs (9, 21).
Fetal MRI is typically performed due to abnormal results found at anatomical surveys generally performed around 18 weeks of gestation. Before 18 weeks of gestation, because of the limitations in spatial resolution and difficulty in the diagnosis of anomalies including congenital diaphragmatic hernia (CDH), fetal MRI is hardly used. Although fetal MRI becomes increasingly more accurate in the later gestational ages, restrictions imposed by age of legal abortion in most countries necessitate earlier diagnosis. However, in most studies of normal fetal lung volumes- this early period (18 - 22 weeks GA) is under-represented despite its significance (13, 16).
Our study complements previous research of the volumetric assessment of fetal lung growth.
There is high inconsistency in total lung volumes as reported by different investigators. In the lack of universally accepted standardized values, this wide range of data generates the likelihood of overlap between normal and abnormal fetal lung volume values.
Rypens et al. (16) estimated FLV at 21 - 38 weeks gestation in 215 fetuses without thoracoabdominal malformations and with normal US biometric findings (range, 16 - 150 mL) increased with gestational age. However, Meyers et al. (17) showed that the measured mean total fetal lung volume values at 19 - 22 weeks were significantly lower than those predicted by the Rypens formula. Although the obtained volumes in our study were lower than the data of mentioned studies at every gestational week, the differences are much noticeable at older gestational age which could be due to biologic variation. This will enhance the possibility of overlap with hypoplastic lung volumes in late pregnancy. At 19 - 22 weeks, our results were more similar to those of Meyers et al. (17) than Rypens et al. (16) There was a higher number of measurements made in this gestational age range in our study and the study performed by Meyers et al. (17) compared to the study conducted by Rypens et al. (16). Our data in this time period was closer to Meyers dataset. Meanwhile, our data set later in pregnancy was significantly lower than both studies. This difference between our study and the two mentioned studies could be related to many factors including the different ethnicities, and different measurement techniques.
On the other hand, several studies have also stated race-based variances in gestational age-specific birth weights. Wang et al. (22) showed that the gestational age-specific mean birth weights of white American babies were higher than those of Japanese babies. The mentioned relationship could be extended to the lung volume, considering the different results of studies for estimation of the normal lung volume in each country. As described before, our result showed the most similarity to the study conducted by Osada et al. (9) which owned the closest match to the race of our population compared to European and American populations in a study performed by Rypens et al. (16) and Meyers et al. (17), respectively. Therefore, it could be concluded that offering a single worldwide practical data base for fetal lung volume is not rational.
As one of the limitations of our study, it should be mentioned that sampling was not performed among a strictly healthy population and it may involve fetuses with structural abnormalities outside the chest cavity referred for prenatal MR imaging. However, this selection limitation was minimized by excluding the fetuses with thoracic abnormalities and other intervening factors, and the measurements obtained in the subjects of the study represent rational estimates of normal lung development.
Second, lung volume measurements may alter with the cardiac cycle or fetal breathing. In this study, such effect tried to be degraded via the acquisition time and by multiple measurements and obtaining a mean fetal lung volume. Third, two plane measurement and 3-D volumetry were not accessible for comparison.
In conclusion, the lung volume can be predicted with a high degree of accuracy in fetuses with the same biological alterations through each gestational age by developing prenatal MR imaging lung volumetry to avoid and prepare for neonatal respiratory problems which are responsible for a high rate of mortality and morbidity.