1. Background
Type 2 diabetes (T2D) is a common metabolic disease caused by insulin secretion defects, which is associated with a variety of complications such as retinopathy, nephropathy, and neuropathy (1, 2). Its worldwide prevalence is estimated to reach around 438 million people in 2030 (3) and a combination of genetic and environmental elements have been suggested in this regard (4). Several studies have found that higher body iron stores are related to the pathogenesis of T2D (5-7). Meanwhile, genome wide association studies suggested a number of genes associated with iron metabolism and the risk of monogenic and/or syndromic forms of T2D (8).
HFE, which is also responsible for hereditary hemochromatosis (HH), is one of those genes. It has revealed that there is a link between T2D and HH so that 20% to 50% of patients with HH also develop T2D (9-11). According to the Ensembl database (http://www.ensembl.org/index.html), HFE gene also called HLA-H and located on the small arm of chromosome 6 (6: 26,087,509-26,098,571), has 14 transcripts, 12 of them could be translated into protein. Two up-stream, missense variants of this gene known as C282Y, which converts 845G→A, and H63D exchanges 187 C→G have been under examination in different studies showing their clinical significance. Investigations on problems such as coronary heart disease (12, 13), cardiomyopathy (14), myocardial infarction (15), hepatic fibrosis (16, 17), colon cancer (18), atherothrombotic cerebral infarction (19), cumulative lead exposure (20), atherosclerosis (21), nonalcoholic fatty liver disease (22), gestational diabetes (23), type 1 diabetes (24), and type 2 (25) have found significant results.
2. Objectives
As studies on T2D showed inconsistent data, we aimed to investigate whether there is any relationship between HFE mutations and the risk of type 2 diabetes in Iranian population.
3. Patients and Methods
3.1. Study Population
Diabetic patients were selected according to standard international guidelines of diagnosis among those referring to the outpatient diabetes clinic of Golestan Hospital Ahvaz, Khuzestan, Iran. A total of 145 patients and 145 matched control subjects (with regard to ethnicity, sex, and age) were enrolled in our study. All the participants signed the informed consent forms prior to enrollment. The local Ethics Committee and appropriate institutional review board approved the study.
3.2. Sample Preparation
Three milliliter peripheral blood was collected in EDTA containing tubes and stored at -20°C. DNA extraction performed using a DNA extraction kit (Bioneer, Korea) under manufacturer protocol and DNA samples were stored at -70°C until the time of experiments.
3.3. Genotyping
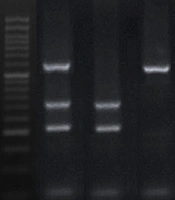
Polymerase chain reaction (PCR) was performed using a PCR kit (Fermentas, Germany) via a thermocycler (Eppendorf, Germany). Restriction fragment length polymorphism (RFLP) was performed using RsaI and MboI restriction enzymes (Bioneer, Korea) (Table 1). Enzyme treated products were run on a 8% polyacrylamide gel visualized by a gel document (CAUTION-ST4, France) and sizes of DNA bands were distinguished using a 50 base pair ladder (GeneOn GmbH, Germany). Ten samples were sequenced by an ABI 3730 sequencer in order to confirm the RFLP data. The investigator responsible for genotype analysis was blinded to this study.
Table 1.
PCR-RFLP Test Information a
| SNP | Primer | Product Length | Restriction Enzyme | Fragment Length |
|---|---|---|---|---|
| H63D (rs799945) | 294 | MboI | 138 | |
| F: ATGGTTAAGGCCTGTTGCTCTGTC | 99 | |||
| R: CCCTTGCTGTGGTTGTGATTTTC | 57 | |||
| C282Y (rs1800562) | 489 | RsaI | 245 | |
| F: TCCTCTTTCCTGTCAAGTGC | 244 | |||
| R: GATGACTCCAATGACTAGGG |
a Abbreviations: SNP, Single nucleotide polymorphism; F, Forward primer; R, Reverse primer.
3.4. Statistical Analysis
Statistical analysis was accomplished using an SPSS (v16) software and OpenEpi online tool. Allele and genotype frequencies were determined by direct gene counting and analyzed by chi-square test. All of the alleles evaluated in this study complied with Hardy-Weinberg equilibrium. Odds ratios (OR) and 95% confidence intervals (CI) were estimated. All the tests were two-sided and the probability of less than 0.05 was considered as statistically significant.
4. Results
Genotyping results extracted from 145 Iranian patients (72 males and 73 females), with the mean age of 53.9 ± 9 years compared to healthy controls with the same sex ratio and the mean range of 51.3 ± 10 years are shown in Tables 2-5. 2-5. Differences between genotypes in diabetic patients and controls are illustrated in Table 2. As it has been shown, the frequency of GG genotype related to polymorphism C282Y is significantly higher, and the GA genotype is lower among patients in comparison with the controls (P < 0.001). Also, regarding the H63D, the differences between CG and CC genotypes are statistically significant in patients compared to healthy controls (P = 0.013). Tables 3 and 4 demonstrate patients who are classified in two groups with nephropathy and retinopathy complications, respectively; in 45 patients with nephropathy, C282Y genotypes were significantly different between patients with nephropathy and controls while the difference between H63D genotypes was not statistically significant. In addition, differences in genotypes of both C282Y and H63D were significant comparing our nephropathic patients and controls (P value < 0.001 and 0.006, respectively). Despite increased homozygote and heterozygote alleles at studied positions in patients with nephropathy compared to the retinopathic patients, it did not achieve significance (Table 5).
Table 2.
Genotype Frequencies of C282Y and H63D Genes in Patients With Type 2 Diabetes and Controls a
| Position | Genotypes | Type 2 Diabetes, (n = 145) | Controls, (n = 145) | P Value b | Odds Ratio (95% Confidence Interval) |
|---|---|---|---|---|---|
| C282Y | 0.000 | ||||
| GA | 97 (67) | 58 (40) | 3.01 (1.87 - 4.90) | ||
| GG | 48 (33) | 87 (60) | 0.33 (0.20 - 0.53) | ||
| H63D | 0.013 | ||||
| CG | 75 (52) | 54 (37) | 1.80 (1.12 - 2.89) | ||
| CC | 70 (48) | 91 (63) | 0.55 (0.34 - 0.88) |
a Data are presented as No. (%).
b Values less than 0.05 are considered significant.
Table 3.
Genotype Frequencies of C282Y and H63D Genes in Diabetic Patients With Retinopathy and Controls a
| Position | Genotypes | Retinopathy (n = 45) | Controls (n = 145) | P Value b | Odds Ratio (95% Confidence Interval) |
|---|---|---|---|---|---|
| C282Y | 0.020 | ||||
| GA | 27 (60) | 58 (40) | 2.24 (1.13 - 4.50) | ||
| GG | 18 (40) | 87 (60) | 0.44 (0.22 - 0.88) | ||
| H63D | 0.393 | ||||
| CG | 20 (44) | 54 (37) | 1.34 (0.67 - 2.66) | ||
| CC | 25 (56) | 91 (63) | 0.74 (0.37 - 1.47) |
a Data are presented as No. (%).
b Values less than 0.05 are considered significant.
Table 4.
Genotype Frequencies of C282Y and H63D Genes in Diabetic Patients With Nephropathy and Controls a
| Position | Genotypes | Nephropathy (n = 100) | Controls (n = 45) | P Value b | Odds Ratio (95% Confidence Interval) |
|---|---|---|---|---|---|
| C282Y | 0.000 | ||||
| GA | 70 (70) | 58 (40) | 3.48 (2.03 - 6.04) | ||
| GG | 30 (30) | 87 (60) | 0.28 (0.16 - 0.49) | ||
| H63D | 0.006 | ||||
| CG | 55 (55) | 54 (37) | 2.05 (1.22 - 3.46) | ||
| CC | 45 (45) | 91 (63) | 0.48 (0.28 - 0.81) |
aData are presented as No. (%).
b Values less than 0.05 are considered significant.
Table 5.
Genotype Frequencies of C282Y and H63D Genes in Nephropathic and Retinopathic Patients a
| Position | Genotypes | Nephropathy (n = 100) | Retinopathy (n = 45) | P Value | Odds Ratio (95% Confidence Interval) |
|---|---|---|---|---|---|
| C282Y | 0.245 | ||||
| GA | 70 (70) | 27 (60) | 1.55 (0.73 - 3.24) | ||
| GG | 30 (30) | 18 (40) | 0.64 (0.30 - 1.35) | ||
| H63D | 0.246 | ||||
| CG | 55 (55) | 20 (44) | 1.52 (0.74 - 3.12) | ||
| CC | 45 (45) | 25 (56) | 0.65 (0.31 - 1.33) |
aData are presented as No. (%).
5. Discussion
This is the first study evaluated HFE gene polymorphisms among Iranian patients with type 2 diabetes. Our results suggested that both heterozygous and homozygous genotypes related to HFE gene polymorphisms are associated with T2D. We showed that only genotypes of C282Y are related to the retinopathy while there is an association between both studied SNPs and the nephropathy seen in T2D patients. The comparison between genotype frequency of T2D patients with retinopathy and those suffering from nephropathy indicated no significant outcome. These variations were subject of several studies.
Sampson et al. (26) found no excess of these HFE mutations in males with T2D. Also, study on 714 diabetic woman in the United States of America showed a significant relationship between higher body iron stores and HFE mutations while there were no significant difference in genotypes between case and controls (27). Similarly, Gomes et al. were unable to find a link between development of T2D and mentioned genotypes in Brazilian women (11). In addition, study on 167 diabetic African-American women declared no difference between frequency of C282Y and H63D between the case and control groups (28). Kankova et al. detected no difference between patients with type 2 diabetes mellitus and controls in Czech population. They found that ferritin levels were significantly higher in woman, but there is no relationship between these genotypes and ferritin levels (29). Study on Hellenic population showed similar results. The authors concluded that increased iron load in their patients linked to C282Y and H63D mutations while there is no difference in the frequency of genotypes between cases and controls (30). In another study, it is indicated that there is no association between distribution of these HFE mutations and T2D, but a relationship exists between H63D mutation and pathogenesis of late onset of disease in polish population (31).
These studies are in contrast with our data. Such discrepancies may have caused by the heterogeneity between different ethnic groups. In 2008, Sharifi et al. (32), which studied the association between mentioned genotypes with T2D in Iranian population could not find any significant correlation. In this case, while their study population was the same as ours, there are some statistical differences such as smaller population and different sex ratio, which caused such incongruity in results. Our data accord with Moczulski et al. (33) study on polish population, which demonstrated that hemochromatosis-causing mutations frequencies may play a role as T2D risk factors when 282Y and 63H mutations were greater in patients than healthy controls. A prospective cohort study, also, suggested an association between C282Y mutation and the incidence of the disease (34). In contrast, 63D allele, not C282Y related alleles, considered as a risk factor for Type 2 diabetes in a recent meta-analysis (25). By comparing genotypes of the two polymorphism with pathophysiological consequences of diabetes such as nephropathy and retinopathy (Tables 2 and 3), we found some significant data. Previously, it has been reported that 63D carriers have an elevated risk for nephropathy in type 2 diabetes (33), which is in consistent with our study and contrary to another study (35). Results from multivariate logistic regression in the Spanish population also approved the role of both C282Y alleles and H63D/H63D genotype in higher incidence of nephropathy (36). Retinopathy, which is another complication of type 2 diabetes, was also considered in some papers. We found that being a carrier of at least one C282Y allele (not H63D) boosts the risk of retinopathy, which is in agreement with previous study (36). It has been demonstrated that heterozygotes for C282Y might be under the risk for the development of proliferative diabetic retinopathy (PDR) (37). These findings showed that H63D plays no role in the incidence and development of retinopathy.
In conclusion, we observed that H63D and C282Y variants in HFE was in association with an increased risk of type 2 diabetes mellitus in Iranian patients. Future studies with a larger sample size and more rigorous study design are warranted.