
1. Background
Spinal cord injury (SCI) is a debilitating neurological condition that results in motor and sensory function impairment, as well as damage to the autonomic nervous system (1), leading to abnormalities across all body systems. Annually, 250,000 to 500,000 individuals worldwide sustain SCI, with two to three million people globally living with disabilities related to spinal cord injuries (2, 3).
According to the National Spinal Cord Injury Statistical Center (NSCISC), based on the current population of the United States, the annual incidence of SCI in the country is approximately 54 cases per million people, or about 17,730 newly reported cases. These figures do not include individuals who sustain SCI and die at the scene of the accident (4). In Iran, approximately 40 to 50 individuals per million are affected by SCI annually, resulting in over 3,000 reported cases each year. A study in Tehran reported an annual incidence of 44 cases per million individuals with SCI (5).
The symptoms of SCI depend on the severity and location of the injury on the spinal cord and may include partial or complete loss of sensory function or motor control in the arms, legs, and/or body. The most severe forms of SCI can disrupt the control systems of the intestine, bladder, breathing, heart rate, and blood pressure. Chronic pain is a common experience among individuals with SCI (3). Loss of urinary and intestinal function is one of the most significant complications of SCI due to its profound impact on quality of life (QOL) (6). Pelvic/visceral organ dysfunction after SCI manifests in various ways, including bladder failure to store urine (reduced capacity) or incomplete emptying, increased tone of the large intestine and anus leading to constipation and fecal retention, and disruptions in reproductive system responses and sexual stimulation. These disruptions may include an inability to maintain an erection or loss of ejaculation in men (7).
Sexual activity is a vital aspect of life, and SCI causes changes in physiological sexual responses, negatively impacting sexual interest and satisfaction (6). Despite being understudied due to stigma (8), there is a genuine need for education on this topic (9). Depending on the level and severity of the injury, changes in reproductive system functions, such as ejaculation in men and lubrication in women, may occur. Additionally, changes in the ability to achieve orgasm and respond sexually are related to the control of sympathetic and parasympathetic nervous systems above the spinal cord (7).
Sexual impotence resulting from SCI leads to changes in relationships, intimacy, and sexual performance, which can ultimately increase anxiety and reduce self-esteem and QOL (10). Research indicates that sexual satisfaction among individuals with SCI decreases post-injury, with women experiencing less sexual satisfaction than men. However, limited research has been conducted on strategies to improve sexual satisfaction in people with SCI (11).
The prevalence of sexual dysfunction following SCI has been reported as 32.4% in men and 13.9% in women. Another study indicated that the prevalence of sexual dysfunction in SCI patients was 6.87% (12). Sexual relationships in women with SCI have been largely overlooked, potentially due to the higher prevalence of SCI among men. Despite this, most para-tetraplegic women retain menstrual and fertility functions (13).
However, due to involuntary bladder or bowel movements, muscle spasticity, pain, or difficulties with social interactions, the sexual activity of individuals with SCI may be affected, leading to decreased sexual desire or frequency of sexual activity (14). Sexual health care involves promoting sexual well-being through prevention and intervention when problems arise (15).
Regarding anxiety disorders and sexual dysfunction, studies have shown that anxiety is a risk factor for sexual dysfunction in individuals with SCI. A higher prevalence of anxiety disorders has been observed among individuals with SCI, ranging from 20% to 48% (16).
Sexual satisfaction refers to an individual's contentment with sexual activity and is influenced by factors such as gender, relationship status, sexual activity, and expectations regarding the relationship's duration (12). Research indicates that sexual satisfaction decreases in individuals with SCI, with women experiencing lower levels of satisfaction. However, limited research has explored methods to improve sexual satisfaction in women with SCI (17).
It is important to note that this study was conducted during the COVID-19 pandemic. According to patient statements, corroborated by other studies (18), limited access to health care during the pandemic increased anxiety and burden on patients and their families (19). In such circumstances, tele-rehabilitation has proven to be significantly beneficial for individuals with SCI, as shown in the same country (20). Therefore, online educational sessions became the only viable intervention method during this period (21).
Research has demonstrated that SCI patients participating in structured rehabilitation programs experience significant improvements in various aspects of QOL (22). Consequently, numerous rehabilitation interventions have been widely implemented to enhance QOL for individuals with SCI (23). As Bober et al. assert, "Sexual rehabilitation interventions that include education about sexual health, experiential exercises for body awareness, including pelvic floor exercises, cognitive exercises based on mindfulness, and individual goal planning lead to significant improvements in anxiety" (24).
Moreover, nurses play a pivotal role in this process. They spend the most time with patients and are well-positioned to establish relationships that foster trust and confidence. Their role in providing sexual counseling, sexual management, anxiety reduction, and sexual rehabilitation education is therefore critical (25).
2. Objectives
Considering the above, the role of nurses in sexual rehabilitation within the interdisciplinary team, despite the critical importance of sexual function for individuals with spinal cord injuries, remains inadequately addressed in nursing care. Given the significant impact of sexual dysfunction on anxiety, sexual satisfaction, and ultimately the QOL of individuals with spinal cord injuries, there is a pressing need for research in the field of sexual rehabilitation alongside physical rehabilitation, starting from the early stages of injury onset. Therefore, this study aims to investigate the effectiveness of sexual rehabilitation education on anxiety and sexual satisfaction in women with spinal cord injuries.
3. Methods
3.1. Study Design
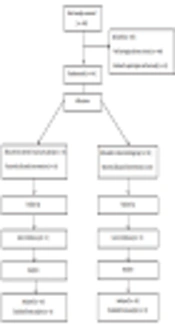
This semi-experimental study with a control group was conducted at the Iranian Spinal Cord Injury Support Society in Tehran. The research population included all individuals with spinal cord injuries that resulted in sexual dysfunction. The sample for this study comprised women with spinal cord injuries and associated sexual dysfunction who were selected based on the study’s inclusion criteria. The inclusion criteria required participants to be literate, not using any medications, free from underlying diseases such as heart and lung conditions, and to have passed the spinal shock phase (exhibiting muscle tone and deep tendon reflexes). Participants were excluded from the study if they expressed dissatisfaction with continuing their participation or failed to attend at least one educational session. The flowchart of the study is presented in Figure 1.

Figure 1.
CONSORT flowchart of the study
3.2. Sampling
The sampling method was continuous and random, conducted over a three-month period. With the cooperation of the center's officials, individuals suffering from dementia or with unstable cognitive conditions (such as intellectual disabilities), as indicated in their medical documents, were excluded from the sampling population (n = 0). Additionally, since the questionnaires were completed online, only those with the mental ability to use technology were included in the study. To prevent data contamination, participants were randomly allocated into two groups. Randomization was conducted by the author with the assistance of a statistics consultant using a simple random method and a table of random numbers. The primary criterion for group stratification was marital status. A minimum of 45 individuals per group was estimated as the sample size based on a 95% confidence level and 80% power. Considering potential sample loss, prior studies similar to this one (26), and the formula shown below, a total of 50 individuals were calculated for each group.
Z1-α/2 = 1.96, Z1-β = 0.84, σ1 = 13, σ2 = 11, d = 7
3.3. Ethical Considerations
In the first step, to comply with ethical principles, permission to conduct the research was obtained from the Ethics Committee of Iran University of Medical Sciences (IR.IUMS.REC.1400.399), along with a letter of introduction from Iran's Faculty of Nursing and Midwifery. The author then introduced herself to the research environment and explained the research objectives. The voluntary nature of participation was emphasized, and written consent was obtained from all research participants.
3.4. Instruments
In this study, a demographic questionnaire was utilized to collect information related to personal details, including age, gender, education, marital status, employment status, economic status, and income. The 21-Item Anxiety Questionnaire featured a four-point scale ranging from 0 to 3, where option 1 scored zero and option 4 scored three. The total score ranged from 0 to 63, with scores of 0 to 21 indicating very mild anxiety, 22 to 35 representing moderate anxiety, and scores above 36 indicating severe anxiety. Validity and reliability were established based on a study by Kaviani and Mousavi, which reported a validity of 72%, reliability of 83%, and internal consistency (Cronbach's alpha = 92%) (27). Content validity was verified and confirmed by three faculty members from Iran University of Medical Sciences. In this study, the reliability coefficient (Cronbach's alpha) was reassessed and found to be 82% within the target population.
The sexual satisfaction questionnaire, designed by Larson, consisted of four components: Inclination towards sexual relations, sexual attitude, quality of sexual life, and sexual compatibility. It employed a Likert scale with five response options (never, rarely, sometimes, often, always) for each of its 25 questions, comprising 13 negative and 12 positive items. Scores ranged from 25 to 125, with scores below 50 indicating sexual dissatisfaction, 51 to 75 indicating low satisfaction, 76 to 100 representing moderate satisfaction, and scores above 100 indicating high sexual satisfaction (28). In this study, the Cronbach's alpha coefficient exceeded 0.7. An exploratory factor analysis using principal component analysis with varimax rotation extracted three latent factors, explaining 73% of the total variance. Content validity was reviewed and confirmed by three faculty members of Iran University of Medical Sciences. Confirmatory factor analysis supported the final structural model of Larson's Sexual Satisfaction Questionnaire, with a Cronbach's alpha coefficient of 78% achieved in this study.
3.4.1. Educational Intervention
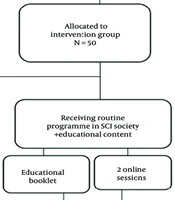
To prepare the educational content of the booklet, reliable information was extracted from scientific evidence and resources, including peer-reviewed journals and reputable books related to the subject. The information was taught to patients in two online sessions, and a physical booklet was provided to the center's patients. Content validity was ensured by having the material reviewed by three faculty members of the School of Nursing and Midwifery at Iran University of Medical Sciences, as well as a group of women with spinal cord injuries. The educational content covered topics including an introduction to SCI, sexual dysfunctions due to SCI, body image after injury and recovery, bladder and bowel management, pressure sore prevention, pain management, muscle spasticity, creating a suitable environment, timing and side effects of medications, and personal hygiene. The educational materials were presented over two 90-minute online sessions. These sessions included video conferencing, instructional videos, and opportunities to address participants’ questions. The content was delivered in simple language and supplemented with educational video clips. To adhere to research ethics, the control group, which only received routine education provided by the center, was also given the educational booklet at the end of the study. During the introductory session, the facilitator introduced themselves, explained the study's aims, and became acquainted with the participants. The educational booklet, detailing sexual issues and ways to address them, was distributed to the participants. During the first and second sessions, questions or observations from participants were addressed with tailored responses that directly addressed their concerns. Skills covered included transferring from a wheelchair to a bed, managing medications around sexual activity (e.g., taking pain medication beforehand), strategies for reducing pressure before sexual activity, regulating bladder and bowel routines, choosing a suitable environment for intimacy, selecting appropriate positions to minimize spasticity, techniques for sexual hygiene, positioning to prevent pressure ulcers and pain during sexual activity, preventing involuntary bowel movements or bladder leaks during intimacy, catheterization procedures, regular bowel and bladder maintenance, using warm baths, massage, and stretching before sexual activity, and adjusting room temperature and lighting to set the mood for intimacy. The educational content developed for this study will be made available as a brochure for future patients at the center. Additionally, authors or researchers interested in this field may request the full content by contacting the corresponding author.
3.5. Implementation Method
Following the ethical code IR.IUMS.REC.1400.399 and an introductory letter, women with spinal cord injuries were continuously selected based on the inclusion criteria from the Iranian Spinal Cord Injury Support Society. The person in charge of the Spinal Cord Injury Support Association provided the author with the patients' contact numbers, and the author explained the research objectives to them via phone calls. After detailing the study objectives and seeking their participation, written consent forms were provided and signed online. Data collection was conducted both before the intervention and one month after it. The tools were administered once prior to the intervention and again one month afterward in both the intervention and control groups. Due to the prevalence of the COVID-19 virus and the need to maintain social distancing, the educational sessions were delivered virtually. A group was initially created on the WhatsApp application, and all participants in the intervention group were invited to join. The questionnaires were designed online, and their links were shared with the participants through the WhatsApp group. As a result, the evaluation of the findings was conducted in a double-blind manner.
3.6. Data Analysis
For data analysis, descriptive statistical methods were employed to organize two-dimensional frequency distribution tables and calculate numerical indices of quantitative variables separately for the two groups. Homogeneity tests were conducted to evaluate the comparability of the groups. The data were analyzed using SPSS software version 21, with t-tests, Fisher's exact tests, and paired t-tests applied for statistical analysis.
4. Results
In this study, 100 women with spinal cord injuries participated, with 64% of individuals in both the control and intervention groups experiencing injuries in the chest area. The mean age of participants in the control group was 38 years, while in the intervention group, it was 40 years. Independent t-test results showed no statistically significant difference in age between the groups (P = 0.228). The average duration of illness in the control group was 9.61 years, compared to 12.86 years in the intervention group, with no significant statistical difference (P = 0.092). The average number of hospitalizations was 9.12 in the control group and 6.72 in the intervention group, with no significant statistical difference (P = 0.228). The results of the demographic questionnaire analysis are presented in Tables 1 and 2.
Table 1.
Age and Injury Duration in Patients Under Research a
| Factors | Control Group | Intervention Group | Independent t-Test |
|---|---|---|---|
| Age | 38.04 ± 8.55 | 40.04 ± 7.93 | t = 1.212; df = 98; P = 0.228 |
| Injury duration | 9.61 ± 9.06 | 12.86 ± 9.97 | t = 1.70; df = 98; P = 0.092 |
a Values are expressed as mean ± SD unless otherwise indicated.
Table 2.
Results of the Data Analysis Obtained from the Demographic Questionnaire a
| Variables and Factors | Control Group | Intervention Group |
|---|---|---|
| Location of the lesion | ||
| Cerebral | 10 (20.0) | 10 (20.0) |
| Thoracic | 32 (64.0) | 32 (64.0) |
| Lumbar | 8 (16.0) | 8 (16.0) |
| Total | 50 (100) | 50 (100) |
| Chi-square test | X2 = 0.0; df = 3; P = 0.99 | |
| Educational status | ||
| Illiterate | 0 (0.0) | 1 (2.0) |
| Less than high school | 11 (22.0) | 13 (26.0) |
| High school | 18 (36.0) | 19 (38.0) |
| Academic | 21 (42.0) | 17 (34.0) |
| Total | 50 (100) | 50 (100) |
| Chi-square test | Fisher = 1.574; P = 0.762 | |
| Economic situation | ||
| Weak | 16 (32.0) | 18 (36.0) |
| Medium | 30 (60.0) | 31 (62.0) |
| Good | 4 (8.0) | 1 (2.0) |
| Total | 50 (100) | 50 (100) |
| Chi-square test | P = 0.492; Fisher = 1.80 | |
| Work status | ||
| Disabled due to illness | 1 (2.0) | 4 (8.0) |
| Retired | 2 (4.0) | 2 (4.0) |
| Unemployed | 1 (2.0) | 7 (14.0) |
| Housewife | 33 (66.0) | 33 (66.0) |
| Free | 8 (16.0) | 3 (6.0) |
| Student | 5 (10.0) | 1 (2.0) |
| Total | 50 (100) | 50 (100) |
| Chi-square test | Fisher = 10.85; P = 0.040 | |
| Insurance | ||
| Have insurance | 29 (58.0) | 37 (74.0) |
| No insurance | 21 (42.0) | 13 (26.0) |
| Total | 50 (100) | 50 (100) |
| Chi-square test | X2 = 2.85; df = 1; P = 0.091 | |
| Residential status | ||
| Rental | 23 (46.0) | 30 (60.0) |
| Owner | 27 (54.0) | 20 (40.0) |
| Total | 50 (100) | 50 (100) |
| Chi-square test | X2 = 1.96; df = 1; P = 0.161 | |
| Living condition | ||
| With children | 7 (14.0) | 5 (10.0) |
| With spouse | 37 (74.0) | 33 (66.0) |
| Other family members | 6 (12.0) | 11 (22.0) |
| Total | 0 (0) | 1 (2.0) |
| Other | 50 (100) | 50 (100) |
| Chi-square test | Fisher = 2.94; P = 0.337 | |
a Values are expressed as No. (%) unless otherwise indicated.
The examination of anxiety variables before and after the intervention in the control group, using a paired t-test, showed no significant statistical difference in average anxiety scores before and after the intervention (P = 0.123). However, in the intervention group, this difference was significant (P = 0.045). The average anxiety score for individuals in the control group was 19.66, while for the intervention group, it was 20.92, indicating homogeneity in terms of anxiety before the intervention (P = 0.525). Additionally, the average sexual satisfaction score for individuals in the control group was 67.32, and in the intervention group, it was 67.80, showing homogeneity in terms of sexual satisfaction as well (P = 0.270). After the intervention, the homogeneity was P = 0.163 for anxiety and P = 0.031 for sexual satisfaction between the two groups. Numerical indicators of anxiety and sexual satisfaction in the control and intervention groups, before and after the intervention, are shown in Tables 3 and 4. The results of the analysis of the Beck Anxiety and Sexual Satisfaction Questionnaires are presented in Table 5.
Table 3.
Numerical Indicators of Anxiety and Sexual Satisfaction in the Control and Intervention Groups Before the Intervention a
| Variables | Control Group | Intervention | Test Statistics |
|---|---|---|---|
| Mild anxiety | 29 (58.0) | 58 (54.0) | X2 = 3.88; df = 2; P = 0.143 |
| Moderate anxiety | 20 (40.0) | 40 (34.0) | |
| Severe anxiety | 1 (2.0) | 2 (12.0) | |
| Total anxiety | 19.66 ± 8.97 | 20.92 ± 10.69 | t = 0.638; df = 98; P = 0.525 |
| Sexual desire | 13.38 ± 2.88 | 12.54 ± 2.90 | t = 1.450; df = 98; P = 0.150 |
| Sexual attitude | 15.92 ± 2.98 | 16.92 ± 2.79 | t = 1.736; df = 98; P = 0.086 |
| Sexual quality | 21.98 ± 4.09 | 21.88 ± 3.88 | t = 0.125; df = 98; P = 0.901 |
| Sexual compatibility | 16.04 ± 4.50 | 16.46 ± 4.64 | t = 0.459; df = 98; P = 0.647 |
| Sexual satisfaction | 67.32 ± 8.99 | 67.80 ± 8.81 | t = 0.788; df = 98; P = 0.270 |
a Values are expressed as No. (%) or mean ± SD unless otherwise indicated.
Table 4.
Numerical Indicators of Anxiety and Sexual Satisfaction in the Control and Intervention Groups After the Intervention a
| Variables | Control Group | Intervention | Test Statistics |
|---|---|---|---|
| Mild anxiety | 28 (56.0) | 34 (68.0) | X2 = 2.265; df = 2; P = 0.322 |
| Moderate anxiety | 20 (40.0) | 13 (26.0) | |
| Severe anxiety | 2 (4.0) | 3 (6.0) | |
| Total anxiety | 20.68 ± 8.55 | 18.04 ± 10.17 | t = 1.40; df = 98; P = 0.163 |
| Sexual desire | 12.80 ± 2.57 | 12.74 ± 2.85 | t = 0.11; df = 98; P = 0.912 |
| Sexual attitude | 15.92 ± 3.90 | 17.76 ± 3.08 | t = 2.61; df = 98; P = 0.010 |
| Sexual quality | 21.94 ± 4.15 | 23.28 ± 3.54 | t = 1.735; df = 98; P = 0.086 |
| Sexual compatibility | 16.56 ± 4.21 | 17.02 ± 4.62 | t = 0.519; df = 98; P = 0.605 |
| Sexual satisfaction | 67.22 ± 9.10 | 70.80 ± 7.07 | t = 2.19; df = 98; P = 0.031 |
a Values are expressed as No. (%) or mean ± SD unless otherwise indicated.
Table 5.
Numerical Indicators of Anxiety and Sexual Satisfaction in the Control and Intervention Groups Before and After the Intervention a
| Variables | Control Group | Intervention |
|---|---|---|
| Beck Anxiety Index | ||
| Before | 19.66 ± 8.97 | 20.92 ± 10.69 |
| After | 20.68 ± 8.55 | 18.04 ± 10.17 |
| Paired t-test | t = 1.56, df = 49, P = 0.123 | t = 2.05; df = 49; P = 0.045 |
| Sexual satisfaction | ||
| Before | 67.32 ± 8.99 | 67.80 ± 8.81 |
| After | 67.22 ± 9.10 | 70.80 ± 7.07 |
| Paired t-test | t = 0.112 df = 49 P = 0.912 | t = 2.05; df = 49; P = 0.045 |
| Sexual desire | ||
| Before | 13.38 ± 2.88 | 12.54 ± 2.90 |
| After | 12.80 ± 2.57 | 12.74 ± 2.85 |
| Paired t-test | t = 1.27 df = 49 P = 0.210 | t = 0.473; df = 49; P = 0.638 |
| Sexual attitude | ||
| Before | 15.92 ± 2.98 | 16.92 ± 2.79 |
| After | 15.92 ± 3.90 | 17.76 ± 3.08 |
| Paired t-test | t = 0.0 df = 49 P = 1.0 | t = 1.637; df = 49; P = 0.108 |
| Sexual quality | ||
| Before | 21.98 ± 4.09 | 21.88 ± 3.88 |
| After | 21.94 ± 4.15 | 23.28 ± 3.54 |
| Paired t-test | t = 0.058 df = 49 P = 0.954 | t = 2.80; df = 49; P = 0.007 |
| Sexual compatibility | ||
| Before | 16.04 ± 4.50 | 16.46 ± 4.64 |
| After | 16.56 ± 4.21 | 17.02 ± 4.62 |
| Paired t-test | t = 0.987 df = 49 P = 0.329 | t = 0.868; df = 49; P = 0.390 |
a Values are expressed as mean ± SD unless otherwise indicated.
5. Discussion
The current study aimed to investigate the effectiveness of sexual empowerment education on anxiety and sexual satisfaction in women with spinal cord injuries. The results showed that the average anxiety score in the control group increased from 19.66 to 20.68, whereas in the intervention group, it decreased from 20.92 to 18.04. This reduction in anxiety was significantly more pronounced in the intervention group compared to the control group (P < 0.05). These findings indicate that sexual empowerment education can effectively reduce anxiety in women with spinal cord injuries.
Consistent with these results, a study by Saadatinezhad et al. on men undergoing coronary artery bypass grafting reported a significant reduction in anxiety levels in the intervention group receiving sexual education compared to the control group (29). Similarly, an interventional study conducted by Bober et al. on young breast cancer survivors revealed a substantial improvement in anxiety levels following sexual empowerment interventions within two months (24). In another study, it was demonstrated that sexual empowerment interventions, including education and exercise, significantly reduced anxiety, stress, and depression in men with coronary artery disease, with the intervention group showing notably lower anxiety scores compared to the control group. This underscores the importance of sexual empowerment as a crucial component of overall empowerment (30). Federici et al. also reported similar outcomes in their study on individuals with spinal cord injuries (31). Moreover, Santos et al. highlighted that interventions targeting individuals with spinal cord injuries could reduce stress, anxiety, and pain while improving functionality and QOL (32).
Based on the findings of the current research, anxiety in the intervention group significantly decreased compared to the control group. However, in the control group, the average anxiety score increased from 19.66 before the study to 20.68 after the study. Given that individuals in the control group received routine education provided by the center, it is apparent that the routine education was insufficient in addressing their needs. This may be attributed to the study being conducted during the COVID-19 pandemic, which hindered physical attendance at the center and likely resulted in weaknesses in the delivery of virtual education to the participants.
In line with the study's other objective, the average sexual satisfaction score in the control group decreased slightly from 67.32 to 67.22, while in the intervention group, it increased significantly from 67.80 to 70.80. This improvement in sexual satisfaction was significantly greater in the intervention group compared to the control group (P < 0.05). These findings suggest that sexual empowerment education can effectively enhance sexual satisfaction in women with spinal cord injuries.
Consistent with these results, a study by Rakhshan et al. on patients with cardiac rhythm management devices receiving virtual empowerment reported a significant increase in sexual satisfaction following empowerment in the intervention group (33). Similarly, an interventional study by Pourghane et al. on patients post-coronary artery bypass grafting who underwent at least 10 rehabilitation sessions found that sexual counseling as part of the cardiac rehabilitation program improved sexual satisfaction and performance after surgery (34). Halvorsen et al. assessed the impact of rehabilitation on the QOL in individuals with spinal cord injuries, emphasizing that post-acute rehabilitation, follow-ups, and integrated care should be prioritized to improve the QOL in these patients, aligning with the findings of this study (35).
Moreover, Suvaal et al. demonstrated that sexual empowerment interventions by nurses enhanced sexual function and satisfaction in women undergoing radiotherapy for cancer (36). Similarly, Zarei et al. found that educative empowerment positively influenced the sexual-marital lives of men with spinal cord injuries, including improvements in sexual satisfaction (37). Mohammadzadeh Moghaddam et al. reported that conventional sexual education methods significantly increased sexual satisfaction scores among women with sexual dysfunction (38). Additionally, Rakhshan et al. obtained similar results in their study on patients undergoing coronary artery bypass grafting (39).
Discrepant with the above results, an interventional study on individuals with stroke examined the impact of a sexual empowerment program on sexual performance, anxiety, depression, stress, functional independence, and QOL. The study found no significant differences between the intervention and control groups in terms of outcome measures. A potential reason for this discrepancy could be that a majority of participants in the intervention group were not sexually active, which may have limited the ability to effectively demonstrate improvements in sexual performance and related outcomes.
In the current research, the evaluation of the anxiety variable before and after the intervention in the control group, which received routine center education, showed that the average anxiety score increased slightly after the intervention. However, this change was not statistically significant (P = 0.123). Similarly, regarding the sexual satisfaction variable, the paired t-test indicated no statistically significant difference in the average sexual satisfaction score before and after the intervention in the control group (P = 0.912).
To justify this, it can be stated that, considering the impact of sexual empowerment education on individuals' levels of anxiety and sexual satisfaction, routine center education proved to be ineffective.
5.1. Limitations
One of the reasons for this limitation could be the challenges posed by the COVID-19 pandemic, including the lack of physical attendance at the center and shortcomings in virtual education. Furthermore, the study's restriction to one gender and its focus solely on individuals attending the SCI support group limit the generalizability of the findings to other individuals with spinal cord injuries. It is recommended that future studies be conducted across multiple centers nationwide and include participants of both genders. Additionally, future research should "investigate the effect of rehabilitation in individuals with spinal cord lesions (not limited to women) while considering the level of the lesion."
5.2. Conclusions
This study aimed to investigate the impact of sexual empowerment education on anxiety and sexual satisfaction in women with spinal cord injuries. The data analysis results demonstrated significant differences between pre- and post-intervention in the intervention group, while no significant differences were observed in the control group. Thus, it can be concluded that implementing a sexual empowerment education program by nurses is an effective strategy for reducing anxiety and increasing sexual satisfaction in women with spinal cord injuries.
Based on these findings, it is recommended that rehabilitation centers and hospital staff actively consider patients' satisfaction with the programs and the efficacy of implementing sexual empowerment programs. These initiatives should be integrated into routine care to address the specific needs of individuals with spinal cord injuries.
This study further underscores the importance of the rehabilitation nurse's role as an educator in delivering health education interventions. Such interventions have been shown to effectively reduce anxiety, enhance sexual satisfaction, and improve QOL. Additionally, the use of online sessions during the COVID-19 pandemic provided vital support to patients, demonstrating the potential of virtual education as an accessible and impactful tool during crises.