
1. Background
The diagnosis of neonatal sepsis can be challenging due to its vague symptoms and similarities to other medical conditions. No single test can definitively diagnose neonatal sepsis, so healthcare providers must rely on a combination of clinical signs, laboratory tests, and imaging studies (1). The most effective way to diagnose it is through a positive blood culture, which is only found in 25 - 54% of cases (2). Biochemical parameters such as C-reactive protein and white blood cell count are not sensitive or specific enough for these patients (3). Additionally, the immune system can overreact to an infection, leading to severe changes in plasma amino acid levels (4). As a result, serum amino acid profiling may be used to identify potential biomarkers for sepsis diagnosis.
Carbohydrates, amino acids, and fatty acids are organic molecules classified as metabolites. The measurement of metabolites produced in response to external stimuli or internal messages provides insight into how the metabolic profile is altered. Metabolomics plays a critical role in improving diagnostic support by quantitatively measuring metabolic responses to pathophysiological stimuli or genetic changes (5). Metabolomic techniques allow us to study metabolites less than 1500 Daltons in size. Several metabolomics studies have been conducted on sepsis (6-8), with a focus on serum nutrient metabolites, particularly amino acids, as potential markers of sepsis (8). Amino acids play a critical role in supporting the immune system (9). For example, glycine (10), serine, and glutamic acid (11) have been shown to support immune function.
2. Objectives
Despite these insights, few studies have specifically examined targeted amino acid profiling in neonatal sepsis, and the role of glycine, serine, and glutamic acid remains incompletely defined. Therefore, our primary objective was to determine whether plasma concentrations of glycine, serine, and glutamic acid differ between neonates with sepsis and healthy controls, using targeted metabolomic analysis. We hypothesized that altered levels of these amino acids would reflect sepsis‑associated metabolic dysregulation and could serve as potential diagnostic biomarkers.
3. Methods
3.1. Study Design
This is a case–control study that was conducted on neonates exhibiting clinical symptoms of sepsis and admitted to the Neonatal Intensive Care Unit (NICU) and Neonatal Departments at Children's Medical Center Hospital between September 2021 and September 2022, and healthy neonates. All neonates who presented with clinical symptoms of sepsis in the emergency department were included in the study. Blood samples were taken from the neonates and sent to the laboratory for C-reactive protein (CRP), complete blood count with differential (CBC diff), and blood cultures to diagnose sepsis before antibiotics were prescribed. A single drop of the blood sample was then placed onto dried blood spot (DBS) filter paper. The blood sample was refrigerated at -80°C in the endocrinology research center's refrigerator. The samples were kept in the refrigerator until all the samples were gathered.
Once we confirmed and diagnosed sepsis using clinical and laboratory evidence, we classified the patients into three groups. The initial group labeled as "proven sepsis" included neonates with positive blood cultures. Neonates showing any one positive laboratory symptom but negative culture were categorized as clinical sepsis, while patients exhibiting sepsis-like symptoms but with a different cause were labeled as suspected sepsis (12). Additionally, we sampled healthy neonates from our metabolic research center for screening purposes.
The study excluded infants with metabolic, neurological, or congenital disorders, those who had not been consented to by their parents, and those who had intrauterine growth restriction (IUGR) or had received total parenteral nutrition (TPN) or nothing by mouth (NPO). We also excluded referral patients to control the probable confounding factors.
3.2. Sample Preparation and Metabolomic Analysis
The basis of sample measurement is the mass-to-charge ratio (m/z) of the analyte, and the scanning mode used is the Multiple Reaction Monitoring (MRM) method. To prepare the samples, three 3.2 mm punches of the DBS sample, equivalent to 10 µL of plasma, were transferred into a 1.5 mL microtube. Subsequently, 200 µL of an internal standard solution containing amino acids and acylcarnitines from Chrome System was added, and the mixture was shaken for 30 minutes at 600 rotations per minute. Afterwards, 150 µL of the supernatant was transferred to a glass vial and evaporated for 20 minutes at 45°C under a stream of nitrogen gas. A solution of acetyl chloride and 1-butanol from Chrome System Company, at a ratio of 1:9 (totaling 50 µL), was added to the vial. The mixture was thoroughly shaken for a minute and then incubated at 65°C for 15 minutes. It was further evaporated under a stream of nitrogen gas at 45°C. The sample was then mixed with 100 µL of a 75% acetonitrile solution from Chrome System and shaken for 10 minutes. Lastly, 10 µL of the resulting mixture was injected into the SCIEX 3200 LC-MS/MS machine.
The LC-MS/MS machine utilized two mobile phases: Organic (acetonitrile with 0.1% formic acid) and aqueous (10 mM ammonium acetate buffer with 0.1% formic acid). The mixture of buffer A, which contained 0.1% formic acid in 100% acetonitrile, and buffer B, which had 0.1% formic acid in water, was used as the mobile phase.
The elution process occurred as follows:
(1) 30% of A was used for elution from 0 to 0.3 minutes.
(2) 90% of A was used for elution for 7 minutes, followed by 9 minutes of elution with 90% A.
(3) 30% of A was used for elution at 9.10 minutes.
(4) The process was halted at 11 minutes.
The optimal flow rate was determined to be 0.6 mL/min, with the column oven set at 30°C, resulting in a total analysis runtime of 11 minutes. The study utilized a SCIEX 3200 mass spectrometer in conjunction with an Agilent Series 1200 chromatography system.
3.3. Bias Control Measures
To minimize potential sources of bias, several steps were undertaken in study design and participant selection. Controls were matched to cases by gestational age and birth weight to ensure comparability. Referral patients were excluded to avoid confounding from prior treatments or differing clinical pathways. Infants with metabolic, neurological, or congenital disorders, intrauterine growth restriction, or those receiving total parenteral nutrition or kept nil per os (NPO) were excluded, as these conditions could independently alter amino acid metabolism. Only neonates with parental consent were enrolled, reducing ethical and selection bias. Laboratory measurements were performed using standardized LC/MS/MS protocols with multiple reaction monitoring (MRM), thereby minimizing information bias and ensuring reproducibility. These measures collectively strengthened internal validity and reduced the likelihood of systematic error.
3.4. Statistics
Data were analyzed using IBM SPSS Statistics (version 25). Normality of continuous variables was assessed using the Kolmogorov-Smirnov test. For normally distributed data, results were expressed as mean ± standard deviation; for non‑normally distributed data, the interquartile range was reported. Categorical variables were summarized as frequencies and percentages.
Between‑group comparisons were performed using one‑way analysis of variance (ANOVA) for normally distributed variables, with Levene’s test applied to confirm homogeneity of variances. Post hoc pairwise comparisons were conducted using Bonferroni correction. For non‑normally distributed data, Mann-Whitney U and Kruskal-Wallis tests were used. Effect sizes were calculated using eta squared (η²).
To account for potential confounders, multivariable logistic regression was performed with sepsis status (septic vs. healthy) as the dependent variable. Independent variables included plasma amino acid levels (glycine, serine, glutamic acid) and clinical covariates (sex, gestational age, age of admission). Adjusted odds ratios (ORs) with 95% confidence intervals (CIs) and P‑values were reported. Figures were generated using GraphPad Prism 8.3.0 (GraphPad Software, La Jolla, CA, USA). A two‑sided P‑value < 0.05 was considered statistically significant.
4. Results
A total of 109 neonates were enrolled in the study: Thirty-one normal neonates and 78 septic neonates. Within the septic group, 18 infants had proven sepsis, 31 had clinical sepsis, and 29 had suspected sepsis.
The demographic pattern was not distributed normally in Table 1. Descriptive statistics for each group are presented in Table 2. The one-way ANOVA revealed a significant difference between the groups. Table 3 shows the mean test scores and standard deviations. The Levene's test statistic shows a P-value > 0.05 for glycine, serine, and glutamic acid, so the assumption of homogeneity of variances is fulfilled. We conducted a one-way ANOVA to compare the mean levels between the four groups. The one-way ANOVA revealed a significant difference in the levels of glycine, serine, and glutamic acid between groups, respectively, F (3,105) = 5.49, P-value < 0.002, F (3,105) = 17.46, P-value < 0.001, F (3,105) = 9.32, P-value < 0.001. The results of the homogeneity test showed that we had equal variances. Therefore, post hoc tests were conducted using the Bonferroni test.
Table 1.
Demographic Data a
| Variables | Proven Sepsis (N = 18) | Clinical Sepsis (N = 31) | Suspected Sepsis (N = 29) | Sepsis (N = 78) | Healthy Neonates (N = 31) |
|---|---|---|---|---|---|
| Gender | |||||
| Male | 15 (83) | 16 (52) | 12 (41) | 43 (55.2) | 20 (65) |
| Female | 3 (17) | 15 (48) | 17 (59) | 35 (44.8) | 11 (35) |
| Gestational age (wk) | 38 (36.7, 38.2) | 38 (36, 38) | 38 (38) | 38 (37, 38) | 38 (38) |
| Age of admission, (d) | 24 (12, 26) | 14 (5, 20) | 6 (4, 10) | 10 (5, 20) | 4 (4, 5) |
a Values are expressed as No. (%) or median (IQR).
Table 2.
Inflammatory Markers Data (N = 109)
| Groups/Subgroups | Mean ± SD | Mean Lower-Upper Bound (95% CI) |
|---|---|---|
| CRP (mg/dL) | ||
| Suspected sepsis | 2.28 ± 1.819 | 1.45 - 3.11 |
| Clinical sepsis | 12 ± 22.501 | 3.28 - 20.72 |
| Proven sepsis | 38.74 ± 24 | 26.00 - 51.47 |
| ANC (µL) | ||
| Suspected sepsis | 3798.97 ± 3735 | 2378.15 - 5219.78 |
| Clinical sepsis | 1837.10 ± 1421 | 1296.47 - 2377.74 |
| Proven sepsis | 4995.56 ± 8291 | 872.27 - 9118.84 |
| WBC (µL) | ||
| Suspected sepsis | 18793.45 ± 48632 | 294.48 - 37292.42 |
| Clinical sepsis | 7983.23 ± 4246 | 6425.54 - 9540.91 |
| Proven sepsis | 10895.56 ± 7730 | 7051.28 - 14739.83 |
| PLT (µL) | ||
| Suspected sepsis | 312103.45 ± 91732 | 277210.36 - 346996.54 |
| Clinical sepsis | 319387.10 ± 215457 | 240356.67 - 398417.53 |
| Proven sepsis | 315000 ± 243053 | 194132.28 - 435867.72 |
Abbreviation: CI, confidence interval.
Table 3.
Metabolites Mean Levels in Different Groups (N = 109)
| Groups/Subgroups | Mean ± SD | Mean Lower-Upper Bound (95% CI) |
|---|---|---|
| Glycine (µmol/L) | ||
| Healthy neonates | 305.65 ± 78 | 334.30 - 276.99 |
| Sepsis | 245.8 ± 71 | 230 - 261 |
| Suspected sepsis | 250.52 ± 70 | 277.43 - 223.60 |
| Clinical sepsis | 237.42 ± 63 | 260.73 - 214.11 |
| Proven sepsis | 244.72 ± 80 | 284.59 - 204.85 |
| Serine (µmol/L) | ||
| Healthy neonates | 121.858 ± 33 | 134.168 - 109.548 |
| Sepsis | 82 ± 23 | 77 - 87 |
| Suspected sepsis | 86.097 ± 19 | 93.437 - 78.756 |
| Clinical sepsis | 83.135 ± 24 | 92.245 - 74.026 |
| Proven sepsis | 74.494 ± 24 | 86.634 - 62.355 |
| Glutamic (µmol/L) | ||
| Healthy neonatesacid | 330.6774 ± 91 | 364.3412 - 297.0136 |
| Sepsis | 249.5 ± 84 | 230.8 - 268.2 |
| Suspected sepsis | 260.0345 ± 62 | 283.8575 - 236.2115 |
| Clinical sepsis | 265.4839 ± 97 | 301.3581 - 229.6096 |
| Proven sepsis | 203.6389 ± 71 | 239.3584 - 167.9194 |
Abbreviation: CI, confidence interval.
Post hoc analysis using Bonferroni correction showed no significant difference between glycine levels in proven sepsis with clinical and suspected sepsis (P-value = 0.85). Post hoc analysis using Bonferroni correction showed no significant difference between serine levels in proven sepsis with clinical and suspected sepsis (P-value = 0.7). Post hoc analysis using Bonferroni correction showed no significant difference between glutamic acid levels in proven sepsis with clinical and suspected sepsis (P-value < 0.08). The effect size calculated as eta squared (η²) between glycine, serine, and glutamic acid groups was 0.135, 0.33, and 0.21, respectively. The calculated eta for glycine was medium, while serine and glutamic acid had large effect sizes.
Multivariable logistic regression was performed to assess the independent association between amino acid levels and sepsis status, adjusting for sex, gestational age, and age of admission. Higher serine levels were significantly associated with reduced odds of sepsis (adjusted OR = 0.924, 95% CI: 0.875 - 0.975, P = 0.004). Similarly, higher glutamic acid levels were independently associated with lower odds of sepsis (adjusted OR = 0.992, 95% CI: 0.984 - 1.000, P = 0.046). Age of admission was positively associated with sepsis risk (adjusted OR = 1.129, 95% CI: 1.005 - 1.268, P = 0.040). Glycine, sex, and gestational age were not significant predictors (Table 4).
Table 4.
Multivariable Logistic Regression Analysis of Amino Acid Levels and Clinical Covariates in Relation to Neonatal Sepsis
| Variables | Adjusted OR [Exp(B)] | 95% CI | P-Value |
|---|---|---|---|
| Glycine | 1.014 | 0.996 - 1.031 | 0.126 |
| Serine | 0.924 | 0.875 - 0.975 | 0.004 |
| Glutamic acid | 0.992 | 0.984 - 1.000 | 0.046 |
| Sex | 1.317 | 0.293 - 5.930 | 0.720 |
| Gestational age (wk) | 0.642 | 0.280 - 1.471 | 0.295 |
| Age of admission (d) | 1.129 | 1.005 - 1.268 | 0.040 |
Abbreviations: OR, odds ratio; CI, confidence interval.
5. Discussion
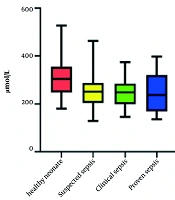
Our study found that levels of glutamic acid, glycine, and serine in the healthy neonates were significantly higher than in the other groups. However, our results did not show a significant difference in these three amino acids between proven, clinical, and suspected sepsis cases. Additionally, we did not find any correlation between these amino acids and inflammatory markers in our study. Our findings also show that the sensitivity and specificity of serine for diagnosing proven and clinical sepsis are higher than those of the other amino acids (Figures 1–3).

Figure 1.
Comparison of glycine levels between groups

Figure 2.
Comparison of serine levels between groups

Figure 3.
Comparison of glutamic acid levels between groups
Sarafidis and colleagues in a case–control study showed urine metabolic changes related to late-onset sepsis. They found an increase in urine glutamic acid levels in these patients compared to the control group (13). Mickiewicz and colleagues reported that the decreased concentration of glutamate is primarily associated with higher utilization of these metabolites in critically ill adult patients (14). Moreover, the role of glutamine in immune health and metabolism is truly remarkable. Glutamine, as the most abundant free amino acid in the body, plays a crucial role in supporting the proliferation of lymphocytes and the production of key immune components such as cytokines, macrophages, and neutrophils. In catabolic and hypercatabolic conditions, where the body is under stress or recovering from injury, the demand for glutamine increases significantly as it becomes essential for maintaining proper metabolism and immune function (11). This mechanism may explain why the level of glutamic acid may decrease during sepsis and stress, which is consistent with our findings.
On the other hand, Eric Newsholme's group has shown that during stressful situations, there is increased production and release of glutamine by lymphocytes, which helps meet the heightened metabolic demands of rapidly dividing cells, supporting their survival and function (15). So, it is possible that the levels of glutamic acid vary on the day of sampling due to compensation mechanisms.
The amino acids serine and glycine are non-essential and can be synthesized in various ways. Serine can be produced by converting glycerate, and this synthesized serine can then be used to create cysteine and glycine. The enzyme serine hydroxymethyl transferase (SHMT) plays a role in converting serine to glycine in a one-step reaction (16). Research has shown that the proliferation of T cells is dependent on the availability of serine and/or glycine (17). In a review of several studies on amino acids, it was noted that there is a discrepancy in the levels of serine and glycine. This difference could be attributed to variations in the APACHE-II score of sepsis patients at the time of sampling (18). Similarly, our study also found discrepancies in the levels of these amino acids.
Our findings contradict a study by Fanos et al., which reported an increase in glycine levels in sepsis (19). This discrepancy could be due to the smaller sample size in Fanos et al.' study (19). Additionally, Dessi et al. reported an increase in serine and glycine levels in sepsis, which is not consistent with our findings (20). However, Dessi et al.'s study had a low sample size, with only one positive fungal patient included (20). It is important to consider these factors when comparing studies on amino acid levels in sepsis patients, as variations in sample size and patient characteristics can impact the results.
Mierzchala-Pasierb et al.'s study on adults admitted to the intensive care unit (ICU) for sepsis showed increased levels of glycine and serine in the septic group. Their study also indicated that amino acid levels vary with the stage of sepsis (21). The main supplier of peptide-bound and free amino acids in humans is skeletal muscles, but extensive catabolism takes place in the small intestine (22). Neonates, however, have less muscle bulk and immature small intestines, so increased levels of glycine and serine may not be observed as in adults. There are several factors that can influence the results of this study, such as the protein supply in adults, the timing of sample collection, compensating mechanisms, the type of microorganisms involved, and the stage of sepsis.
Our regression analysis demonstrated that serine and glutamic acid remained independently associated with sepsis after adjustment, both showing inverse relationships. This suggests that lower levels of these amino acids may contribute to sepsis pathophysiology or reflect metabolic stress in affected neonates. Age of admission also emerged as a significant predictor, consistent with the clinical observation that later presentation may reflect more advanced disease. Glycine, sex, and gestational age were not independently associated. These findings highlight the potential of serine and glutamic acid as candidate biomarkers, although residual confounding and the modest effect sizes warrant cautious interpretation.
5.1. Study Limitation
Our study is unique in that we utilized a larger number of patients compared to other studies on neonates. We also made an effort to categorize our patients based on both culture and clinical sepsis, which is not commonly done in other studies. However, we acknowledge that our patient sample size is still limited, and further research with a larger cohort is needed to draw more definitive conclusions. One limitation of our study is that we did not use standard sepsis scoring systems to classify our patients, which could be a potential confounding factor. Moving forward, we will consider incorporating these scoring systems into our methodology to better align with existing research in the field. Additionally, due to the high cost of these procedures, we recognize that routine use may not be feasible, and alternative cost-effective strategies should be explored.
5.2. Conclusions
Our study demonstrates that plasma levels of serine and glutamic acid are significantly lower in septic neonates and remain independently associated with sepsis after adjustment for confounders, suggesting their potential role as candidate biomarkers. Glycine levels, although reduced in septic neonates compared to controls, did not show an independent association. Age of admission was also positively associated with sepsis risk, highlighting the importance of clinical timing in disease presentation. While these amino acids cannot discriminate between proven, clinical, and suspected sepsis subgroups, their consistent inverse associations with sepsis status underscore their relevance in neonatal metabolic response to infection. Future research should explore their integration into multi‑marker panels or combined with clinical scoring systems to improve diagnostic accuracy. Larger cohorts and longitudinal designs will be needed to validate these findings and clarify residual confounding factors.