
1. Background
Obsessive-compulsive disorder (OCD) is a serious mental disorder that involves unwanted thoughts, obsessions, and compulsions. People with OCD engage in repetitive behaviors to alleviate the anxiety triggered by these thoughts (1). The prevalence of OCD has been reported to be between 1% and 3% in community-based studies (2). The illness typically begins in early adulthood, with the average age at onset ranging from 21.1 to 34.9 years (3). Obsessive-compulsive disorder has a chronic and progressive course, leading to adverse consequences and costs for individuals, families, and health care systems (2, 4). Treatment options for OCD include pharmacotherapy, psychotherapy, and brain stimulation techniques (5-7). However, the response to treatment is often slow and incomplete, with only 40% - 70% of patients responding to initial treatments and a notable number not responding to any form of treatment (8). Treating OCD is one of the most challenging issues in clinical psychiatry (6).
An acceptable treatment response for OCD is typically defined as a 25% - 35% reduction in OCD severity (9). Selective serotonin reuptake inhibitors (SSRIs) remain the most effective and first-line treatment for patients with OCD (10). In cases of insufficient therapeutic response, different strategies may be considered depending on the level of response. These strategies may include dose optimization, augmentation with other drugs, or the use of other techniques (10). In addition to serotonin, other neurotransmitters, such as dopamine and glutamate, are also involved in the pathogenesis of OCD (8). Drug augmentation strategies are one way to increase the likelihood of a therapeutic response. In augmentation, a medication from a different class with a distinct mechanism of action is added to the current treatment regimen (11). Dopaminergic medications, such as haloperidol and newer antipsychotics, particularly risperidone and aripiprazole, are used to complement the initial treatment regimen (10, 12). Unfortunately, many patients do not benefit from these medications because of adverse effects or insufficient response (12, 13).
Regulating glutamate activity in the nervous system is essential because of its neurotoxic effects. Glutamate acts as a key neurotransmitter in the frontostriatal-thalamocortical pathway, which is crucial for habit learning and related disorders. Dysregulated glutamatergic activity manifests as an imbalance in this neural system. It can be hypothesized that the development of obsessive behaviors is a clinical consequence of this dysregulation (14). Evidence from functional imaging studies using magnetic resonance spectroscopy (15) and laboratory findings from cerebrospinal fluid analyses in individuals with OCD indicate disruptions in glutamate metabolism, which is the most important excitatory neurotransmitter in the brain (16). In the study by O’Neill et al. (17), the relationship between treatment response and glutamate levels in the brain was examined in children with OCD after cognitive-behavioral therapy (CBT). The results revealed decreased glutamate levels in the anterior cingulate region, a key anatomical center involved in OCD. Furthermore, the study found that higher levels of glutamate in the posterior-dorsal cortex were associated with a better response to treatment.
Gamma-aminobutyric acid (GABA)-glutamate system modulators, such as memantine (18), lamotrigine (19), riluzole (5), and N-acetylcysteine (20), have been used in clinical studies with varying levels of success. Although first-line medications combined with CBT or exposure and response prevention are the preferred treatment strategies, alternative treatments, such as glutamatergic medications, are recommended for patients diagnosed as treatment-resistant when previous approaches have not been successful (5, 16). Several clinical trials with small sample sizes have investigated the therapeutic effects of medications that regulate glutamate levels. Memantine, in combination with SSRIs, has demonstrated consistent positive effects (21). Memantine is a noncompetitive N-methyl-D-aspartate (NMDA) receptor antagonist primarily used in treating Alzheimer disease. Its ability to regulate glutamate and its good tolerability have made it a viable option for augmentation strategies in treating OCD (12). Initiating treatment with memantine is easier because it does not require a slow titration process like lamotrigine (22) or precise liver monitoring like riluzole (23). Clinical trials, including single-blind, double-blind, and controlled studies, have demonstrated that the combination of memantine and SSRIs is effective in reducing the severity of OCD (16).
Psychiatrists often encounter the challenge of treating patients with OCD who do not respond to standard treatments (24). They use a combination of medications and therapeutic approaches to improve patients’ clinical conditions (14). Since 2018, we have prescribed memantine to treatment-resistant patients because of its favorable safety profile and reported effectiveness in successfully treating cases of OCD. This approach was taken only when patients were unable to tolerate other medications or when following stepwise treatment algorithms did not lead to adequate responses, resulting in a therapeutic impasse. From a clinical perspective, the most useful predictors of treatment response are those that do not require additional costs, such as laboratory tests or imaging studies. Clinical studies have not yet yielded definitive and consistent results regarding variables that predict response to OCD treatments (16). Factors such as clinical disorder severity, early age at onset, duration of illness, and comorbidity with other disorders have been studied in relation to responses to serotonergic medications (24).
2. Objectives
The purpose of this retrospective study was to compare clinical and demographic variables between 2 groups of patients: Those who clinically responded to memantine and those who did not among patients with treatment-resistant OCD.
3. Methods
3.1. Study Design
This was a naturalistic retrospective study conducted in 94 treatment-resistant patients with OCD. This study received Ethics Committee approval from Guilan University of Medical Sciences (code: IR.GUMS.REC.1401.569), and all methods were performed in accordance with the Declaration of Helsinki.
3.2. Participants
The study population included patients from 2 outpatient psychiatric clinics: A private psychiatry clinic and a university clinic at Shafa Hospital in Rasht, Guilan province, northern Iran. Ninety-four patients with OCD who were considered treatment-resistant and received memantine-augmented treatment were recruited using convenience sampling.
3.3. Procedure
Data for this study were collected from patient records at 2 psychiatric clinics from 2018 to 2023. Patients with a history of bipolar disorder, psychotic disorders, intellectual disabilities, or moderate-to-severe substance use disorders were excluded. Clinical interviews were conducted to gather additional information or complete incomplete records when needed. Comorbid diagnoses, including anxiety disorders, major depressive disorder, tic disorders, and OCD-related disorders, were evaluated using the Structured Clinical Interview for DSM-5 Research Version (SCID-5-RV) and documented in patient files to indicate their current status at the last visit.
Patients were treated with the recommended doses of fluoxetine 80 mg, sertraline 200 mg, fluvoxamine 300 mg, or paroxetine 60 mg for at least 12 weeks (25). A reduction in Yale-Brown Obsessive Compulsive Scale (Y-BOCS) symptom severity scores equal to or greater than 35%, 25% or more but less than 35%, and less than 25% was considered a good response, partial response, and no response, respectively. If there was a partial or no response to the first SSRI, treatment was changed to a second SSRI. If there was a partial response to the second SSRI, or if patients had a good response but their Y-BOCS severity score was equal to or greater than 16, augmentation with aripiprazole (10 mg) or risperidone (3 mg) was considered (26, 27) for 12 weeks. If intolerable adverse effects or lack of therapeutic response occurred, augmented treatment with risperidone or aripiprazole was discontinued, and the patient became a candidate for treatment augmentation with memantine plus an SSRI.
Patients who were candidates for memantine augmentation received 10 mg over an 8-week period; if there was no response, they received 20 mg of memantine over another 8-week period. The results of the study by Modarresi et al. (1) showed that although lower doses of memantine had a therapeutic response, a dose of 20 mg provided a more favorable response. As a side report of the current study, clinical response also appeared to occur with lower doses of memantine. A reduction of 30% or more in the Y-BOCS severity score of obsessive symptoms was considered a response to memantine (9, 28, 29). Somnolence and dizziness were the most common adverse effects of memantine augmentation.
Psychotherapy was available at the university outpatient psychotherapy clinic with insurance and government funding. Issues such as difficulty attending sessions and intolerance to anxiety arising during exposure sessions were serious obstacles to starting and continuing sessions (30). Our patients were those who, for any reason, did not accept psychotherapy, did not effectively continue treatment, or did not have an adequate response to psychotherapy.
Patients were divided into 2 groups: Those who exhibited a clinical response were placed in the clinical response group, while those without a response were classified as the no clinical response group. The examined variables, extracted from patient records, included comorbid disorders, type of OCD, duration of OCD, age at onset, family history of OCD, severity of OCD, and current medication regimen.
3.4. Measures
3.4.1. Information Checklist
This checklist contains demographic variables, including age, sex, and education level, and clinical variables, including comorbidities, OCD subtypes, duration of illness, age at onset, family history of OCD, current medication regimen, severity of OCD symptoms, and response to treatment.
3.4.2. Yale-Brown Obsessive Compulsive Scale
The Y-BOCS is a widely used tool for measuring the severity of OCD symptoms. Administered by a clinician, the Y-BOCS comprises 2 components: A frequency checklist for obsessions and compulsions and a severity measure. The classification of obsessive-compulsive symptoms in this research was based on Y-BOCS symptom checklist categories. The total severity score ranges from 0 to 40, with higher scores indicating greater symptom severity. The results of therapeutic interventions were evaluated using the Y-BOCS according to the timelines described for each drug intervention. Its internal consistency in investigations conducted in Iran was found to be 0.97 and 0.95, respectively, with a test-retest reliability of 0.99 (31). Another Iranian study demonstrated excellent concurrent validity with a well-known structured clinical interview for DSM-IV (32).
3.4.3. Structured Clinical Interview for DSM-5 Research Version
The SCID-5-RV is a structured diagnostic tool designed to comprehensively assess a wide range of psychiatric disorders based on the diagnostic criteria outlined in the DSM-5. This clinical interview consists of precise and structured questions that facilitate accurate and reliable diagnosis of various disorders. Due to its comprehensiveness and high reliability, the SCID-5-RV is widely used in clinical research and diagnostic assessments (33). In an Iranian study, its psychometric properties demonstrated an acceptable range for internal consistency (0.95 - 0.99), test-retest reliability (0.60 - 0.79), and kappa reliability (0.57 - 0.72). Furthermore, SCID-5-RV categorical diagnoses indicated acceptable construct validity (34).
3.5. Data Analysis
Statistical analyses were performed using IBM SPSS Statistics version 26. Continuous variables were compared between responders and nonresponders using independent-samples t-tests, and categorical variables were analyzed using the Chi-square test.
To assess the strength of associations, univariate logistic regression was used to calculate odds ratios (ORs) with 95% confidence intervals (CIs). A multivariate logistic regression model was initially considered; however, it was not retained in the final analysis due to the limited sample size of the responder group (n = 42), which did not meet the minimum events-per-variable (EPV) requirement for the number of predictors investigated.
Instead, a post-hoc power analysis was conducted to evaluate the study’s sensitivity. Based on the sample size (N = 94) and the observed response rate, we calculated the minimum detectable effect size for a power of 80% at α = 0.05. This approach was chosen to transparently interpret the nonsignificant results in the context of statistical power limitations.
4. Results
The study sample comprised 94 individuals diagnosed with treatment-resistant OCD, aged between 17 and 71 years, with a mean ± SD age of 45.81 ± 13.44 years. Of the participants, 22 (23.4%) were male and 72 (76.6%) were female. Regarding education, 8 participants (8.5%) were illiterate, 35 (37.2%) had less than a high school diploma, 29 (30.9%) had a high school diploma, and 22 (23.4%) held a university degree. The mean ± SD duration of education was 10.32 ± 4.62 years. While 36 participants (38.3%) had no comorbid conditions, 58 (61.7%) had at least 1 additional diagnosis. A family history of OCD was reported in 71 participants (75.5%), while 23 (24.5%) had no such family history. Sixty-two patients (66%) were taking SSRI medications, and 32 (34%) were additionally using serotonin-dopamine antagonist (SDA) medications.
The most common obsessions were washing (77 participants, 81.9%), symmetry (22 participants, 23.4%), and sexual concerns (23 participants, 24.5%), with smaller groups reporting hoarding, aggression, or other types of obsessions. The mean ± SD age at onset was 22.11 ± 8.48 years. Ultimately, 52 participants (55.3%) did not demonstrate the desired therapeutic response to memantine, while 42 (44.7%) did. Furthermore, the mean ± SD severity of illness was 30.21 ± 3.94, with mean ± SD obsessive-compulsive symptom scores of 15.30 ± 1.61 for obsessions and 15.05 ± 1.83 for compulsions.
Table 1 presents the frequency, percentage, mean, and standard deviation for the 2 groups: Those who responded to memantine and those who did not. To examine the significance of the observed differences between the groups, the Chi-square test (χ²) was used for nominal and ordinal variables, and the independent-samples t-test was used for interval variables. As shown in Table 1, the test results indicated no significant differences between the 2 groups regarding response to memantine (P > 0.05).
Table 1.
| Variables | No Response (N = 52) | Response (N = 42) | χ² / t | P-Value |
|---|---|---|---|---|
| Gender | 0.425 | 0.515 | ||
| Male (n = 22) | 14 (14.9) | 8 (8.5) | ||
| Female (n = 72) | 38 (40.4) | 34 (36.2) | ||
| Education by degree | 1.763 | 0.623 | ||
| Illiterate (n = 8) | 4 (4.3) | 4 (4.3) | ||
| Under diploma (n = 35) | 22 (23.4) | 13 (13.8) | ||
| Diploma (n = 29) | 16 (17.0) | 13 (13.8) | ||
| Academic (n = 22) | 10 (10.6) | 12 (12.8) | ||
| Comorbidity | 0.365 | 0.546 | ||
| No (n = 36) | 18 (19.1) | 18 (19.1) | ||
| Yes (n = 58) | 34 (36.2) | 24 (25.5) | ||
| OCD | ||||
| Washing | < 0.001 | 1.000 | ||
| No (n = 17) | 9 (9.6) | 8 (8.5) | ||
| Yes (n = 77) | 43 (45.7) | 34 (36.2) | ||
| Symmetry | < 0.001 | 1.000 | ||
| No (n = 72) | 40 (42.6) | 32 (34.0) | ||
| Yes (n = 22) | 12 (12.8) | 10 (10.6) | ||
| Taboo | 0.011 | 0.915 | ||
| No (n = 70) | 38 (40.4) | 32 (34.0) | ||
| Yes (n = 24) | 14 (14.9) | 10 (10.6) | ||
| Hoarding | < 0.001 | 1.000 | ||
| No (n = 93) | 51 (54.3) | 42 (44.7) | ||
| Yes (n = 1) | 1 (1.1) | 0 (0.0) | ||
| Aggressive | 1.340 | 0.247 | ||
| No (n = 82) | 43 (45.7) | 39 (41.5) | ||
| Yes (n = 12) | 9 (9.6) | 3 (3.2) | ||
| Others | < 0.001 | 1.000 | ||
| No (n = 79) | 38 (40.4) | 31 (33.0) | ||
| Yes (n = 25) | 14 (14.9) | 11 (11.7) | ||
| Family history | 0.012 | 0.914 | ||
| No (n = 23) | 12 (12.8) | 11 (11.7) | ||
| Yes (n = 71) | 40 (42.6) | 31 (33.0) | ||
| Prescribed medication | 0.277 | 0.599 | ||
| SSRI (n = 62) | 36 (38.3) | 26 (27.7) | ||
| SSRI + SDA (n = 32) | 16 (17.0) | 16 (17.0) | ||
| Age (n = 94) | 45.40 ± 13.26 | 46.31 ± 13.80 | -0.323 | 0.747 |
| Education (y) (n = 94) | 10.10 ± 4.17 | 10.60 ± 5.16 | -0.519 | 0.605 |
| Disorder duration (n = 94) | 22.13 ± 11.44 | 24.95 ± 12.43 | -1.142 | 0.256 |
| Age at onset (n = 94) | 22.90 ± 8.53 | 21.12 ± 8.41 | 1.015 | 0.313 |
| Disorder severity (n = 94) | 30.33 ± 3.49 | 30.07 ± 3.54 | 0.351 | 0.727 |
| Y-BOCS (n = 94) | 30.31 ± 3.47 | 30.40 ± 2.71 | -0.149 | 0.882 |
| Obsession (n = 94) | 15.29 ± 1.73 | 15.31 ± 1.46 | -0.063 | 0.950 |
| Compulsion (n = 94) | 15.02 ± 2.12 | 15.10 ± 1.43 | -0.207 | 0.837 |
Abbreviations: OCD, obsessive-compulsive disorder; SSRI, selective serotonin reuptake inhibitor; SDA, serotonin-dopamine antagonist; Y-BOCS, Yale-Brown Obsessive Compulsive Scale.
a Values are expressed as No. (%) or mean ± SD.
b Percentages appear to be calculated using the total sample denominator (N = 94).
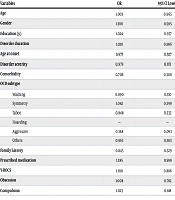
Simple logistic regression was employed to assess the predictability of clinical response to memantine by other variables. The results are presented in Table 2. As shown in the table, none of the variables were significant predictors of clinical response to memantine (P > 0.05). It should be noted that due to a sample size of fewer than 2 individuals for the hoarding subtype of OCD, it was impossible to calculate coefficients for this variable in the regression model.
Post-hoc power analysis revealed that statistical power was approximately 0.05 for detecting small effects and 0.40 for large effects, suggesting that a larger sample size would be required to definitively rule out moderate associations.
Table 2.
Prediction of Clinical Response to Memantine by Demographic and Clinical Variables (Logistic Regression)
| Variables | OR | 95% CI Lower | 95% CI Upper | Wald | P-Value |
|---|---|---|---|---|---|
| Age | 1.005 | 0.965 | 1.026 | 0.107 | 0.744 |
| Gender | 1.566 | 0.585 | 4.190 | 0.797 | 0.372 |
| Education (y) | 1.024 | 0.937 | 1.120 | 0.273 | 0.601 |
| Disorder duration | 1.020 | 0.986 | 1.056 | 1.300 | 0.254 |
| Age at onset | 0.975 | 0.927 | 1.024 | 1.027 | 0.311 |
| Disorder severity | 0.979 | 0.871 | 1.101 | 0.125 | 0.723 |
| Comorbidity | 0.706 | 0.306 | 1.630 | 0.666 | 0.414 |
| OCD subtype | |||||
| Washing | 0.890 | 0.310 | 2.550 | 0.047 | 0.828 |
| Symmetry | 1.042 | 0.399 | 2.719 | 0.007 | 0.934 |
| Taboo | 0.848 | 0.332 | 2.167 | 0.118 | 0.731 |
| Hoarding | — | — | — | — | — |
| Aggressive | 0.368 | 0.093 | 1.456 | 2.031 | 0.154 |
| Others | 0.963 | 0.383 | 2.420 | 0.006 | 0.936 |
| Family history | 0.845 | 0.329 | 2.171 | 0.122 | 0.727 |
| Prescribed medication | 1.385 | 0.588 | 3.263 | 0.554 | 0.457 |
| Y-BOCS | 1.010 | 0.886 | 1.151 | 0.023 | 0.881 |
| Obsession | 1.008 | 0.782 | 1.301 | 0.004 | 0.949 |
| Compulsion | 1.023 | 0.818 | 1.279 | 0.040 | 0.841 |
Abbreviations: OR, odds ratio; CI, confidence interval; OCD, obsessive-compulsive disorder; Y-BOCS, Yale-Brown Obsessive Compulsive Scale.
5. Discussion
The primary aim of this study was to identify clinical or demographic predictors of response to memantine augmentation in patients with treatment-refractory OCD, potentially reducing the risk of treatment ineffectiveness. This fundamentally transforms patient care from a “trial-and-error” process to a more precise, personalized, and effective model. Currently, finding an effective treatment for treatment-resistant OCD is a lengthy and disappointing process of trying one medication after another, each with an 8- to 12-week trial period. Shortening response time is critical and important because prolonged, untreated disorder may lead to greater functional impairment. The increase in the number of agents that are candidates for augmentation of first-line drugs in treatment-resistant OCD highlights the importance of identifying predictors of treatment response.
5.1. Age
A review of studies on pediatric OCD treatment response found limited evidence for age as a predictor (35). One study showed that younger children aged 8 - 12 years had a better response to fluvoxamine. Treating OCD in younger children with milder symptoms may result in better outcomes, but age alone may not reliably predict treatment success (36). Albert et al. (37) noted that the duration of untreated illness may be a predictor of nonresponse to pharmacological therapies, a factor not explored in our study.
5.2. Gender
In a 2019 review by Mathes et al., no significant link was found between patient gender and response to pharmacological treatment. One study suggested that males experienced greater symptom improvement over 2 years, but this effect did not last at the 5-year mark. Interestingly, symptoms tended to decrease more quickly in women (38). In summary, gender does not seem to predict a favorable treatment response, aligning with our study findings. In the Iranian treatment-seeking population, it is important to note that female patients are more willing to seek treatment compared with male patients. This may result in a higher number of female participants in clinical studies, which could affect study outcomes. Our study found no significant relationship between gender and response to memantine treatment. A lower percentage of patients responded to memantine in both gender groups compared with those who did not respond.
5.3. Education
Higher educational attainment may improve knowledge and attitudes, leading to better adherence to treatment and medical recommendations. However, assessing the impact of education on treatment response in patients with OCD is complex because of various confounding factors. Currently, no study has identified education level as a significant predictor of pharmacological treatment response in patients with OCD. Studies on the effectiveness of CBT and behavioral treatments in patients with treatment-resistant OCD have yielded mixed results. One study showed that education level did not have a significant impact on treatment response in patients undergoing CBT (39). Our study did not show a significant relationship between education level and response to memantine. However, when we examined different educational subgroups, we noticed that the proportion of illiterate individuals was similar in both responders and nonresponders. In contrast, there were fewer responders among those with a high school diploma or less, while individuals with advanced degrees had a higher likelihood of responding to treatment.
5.4. Comorbidity
In the study conducted by Farrell et al., comorbidity did not affect treatment response in a pediatric population (40). Similarly, the study by Hojgaard et al. indicated that only the initial severity of OCD predicted posttreatment severity (41). However, in a study by Khalkhali et al. (42), comorbidity between OCD and generalized anxiety disorder was shown to improve treatment prognosis for OCD. The potential for comorbidity to have either a positive or negative impact on response to a specific medication suggests that the medication may exert a therapeutic effect on both the comorbid condition and OCD, or at least not exacerbate the comorbidity. For example, SSRIs may be simultaneously prescribed for patients with both bipolar disorder and OCD. Some studies have indicated the antimanic effects of memantine, while its efficacy in treating OCD remains under discussion (43). In a meta-analysis conducted by Modarresi et al. (1), some studies considered comorbidity as a factor, while others controlled for or excluded it.
In our study, we did not find a significant relationship between comorbidity and treatment response. However, we observed that among patients with comorbid conditions, the percentage of responders was lower than that of nonresponders. In patients without comorbidities, response rates were the same in both groups. The study authors noted significant reductions in mean Y-BOCS scores in both groups, but better outcomes were seen in patients without comorbid disorders. Classifying OCD based on comorbidities, identifying the systems involved, and conducting multicenter clinical trials with sufficient sample sizes may change the future of treatment. For example, dysregulation of excitatory and inhibitory synaptic mechanisms, particularly involving astrocytic glutamate transporter 1, plays a crucial role in the manifestation of obsessive-compulsive and tic disorders (44). Based on these neurobiological models, which are potentially more prominent in OCD with tics, a better response to NMDA antagonists such as memantine may be predicted. Contrary to our hypothesis, the presence of a comorbid disorder did not emerge as a significant predictor of clinical response to memantine, indicating that larger sample sizes and a better understanding of these comorbidity models are needed in further research. Due to the small sample size, the analysis was based only on whether the patient had at least 1 of the 4 psychiatric disorders.
5.5. Obsessions and Compulsions
Some studies have indicated that specific subtypes of OCD can negatively affect the prognosis of OCD treatment (39). Conversely, a review study focusing on a pediatric population found that 2 of 3 studies did not establish a significant relationship between OCD subtype and treatment response, while the third study reported that the contamination subtype had the highest treatment response to pharmacotherapy (36). Obsessive-compulsive disorder subtypes have been proposed as clinical groups linked to distinct neural correlates, and neurobiological differences could translate into differential treatment responses. Contrary to our hypothesis, OCD symptoms did not significantly predict clinical response to memantine. However, our null finding is consistent with a larger body of research on first-line treatments, including serotonin reuptake inhibitors and CBT, where symptom dimensions have generally shown limited and inconsistent value in predicting treatment outcome. This suggests that the mechanism of action of memantine, like that of serotonin reuptake inhibitors, may target a transdiagnostic or core pathophysiology of OCD that is common across dimensions. Patients rarely present with a “pure” symptom. Significant overlap and co-occurrence of symptoms within individuals may obscure any subtle predictive signal that a single dimension might have.
5.6. Duration of Illness
Research has shown that a longer duration of illness is linked to a worse prognosis. In a meta-analysis conducted by Perris et al. (45), patients with a longer duration of untreated illness had poorer treatment outcomes and more severe illness. In a study by Albert et al. (46), a duration of illness exceeding 24 months before starting treatment was linked to poor responses to serotonin reuptake inhibitor medications. However, when duration of illness was analyzed as a continuous variable rather than a categorical one, less than 24 months versus more than 24 months, this relationship was no longer significant. In another study, having an illness duration of less than 5 years was found to be a positive predictor of treatment success (39). In contrast, other studies examining factors that predict response to SSRI medications have produced conflicting results (38).
In our cohort, duration of illness, or the duration of prior unsuccessful treatment, was not a significant predictor of clinical response to memantine augmentation. It can be concluded that the window of therapeutic opportunity may remain open even in cases of long-standing illness. Our sample was already defined as treatment-resistant. Within this narrow band of severe illness, the additional variance explained by duration may be minimal. As a predictor, duration of illness may interact with other factors, such as age at onset. Our study may have been underpowered to detect such complex interactions. Although a longer illness duration may lead to more challenges in interpersonal relationships and family life, it may not directly affect responses to specific pharmacological treatments.
5.7. Age at Onset
Research on predictive factors for response to clomipramine treatment indicates that age at onset of OCD is an important predictor, independent of illness duration. Higher age at onset is associated with better treatment responses (43). Previous studies have suggested that starting SSRI treatment at a younger age may lead to a more positive response. However, more research is required to fully understand how age at onset influences treatment outcomes with various SSRI medications (47). Our analysis did not identify age at OCD onset as a significant predictor of clinical response to memantine augmentation.
5.8. Family History
Having a family history may increase the chances of responding well to certain medications. Studies on the relationship between family history of OCD and response to SSRI medications have produced conflicting findings (47). In our study, a family history of OCD did not serve as a predictor of response to memantine treatment. Having a positive family history indicates a higher burden of risk alleles but does not necessarily indicate a higher prevalence of the specific glutamatergic dysfunction that memantine corrects.
5.9. Medication Combination
To date, the addition of antipsychotics to SSRIs has been recognized as the most effective strategy for addressing inadequate responses to first-line treatments for OCD (24). We hypothesized that patients already receiving SDAs might represent a distinct subgroup in such a way that prior use of SDA predicts a good therapeutic response. Our results did not support this hypothesis. This may be explained by different mechanisms of action, meaning that the presence or absence of any of these agents may not predict response to others, as well as by the type, dose, and duration of selected SDAs and the levels of resistance. It can be cautiously concluded that, in this sample, response to memantine was not contingent upon SDA use.
5.10. Severity of Disorder
Baseline severity of the disorder, typically assessed using the Y-BOCS, cannot be considered a reliable predictive variable for treatment with SSRIs. In 8 studies conducted with pediatric populations, 6 found no significant relationship between disease severity and treatment outcomes. The results of the remaining 2 studies indicated that patients with greater symptom severity had a lower likelihood of complete recovery (48). In our study, which focused on an adult population, no significant relationship was observed between overall disorder severity or cognitive and compulsive subgroups and treatment response. This supports the notion that treatment response may be independent of severity. Conflicting findings suggest that baseline severity of the disorder, typically measured using the Y-BOCS, may not reliably predict the effectiveness of treatment with SSRIs. This finding, consistent with other findings, indicates the need for further studies on less-understood mechanisms of drug response.
5.11. Conclusions
In this study of memantine augmentation for treatment-resistant OCD, we explored a range of potential predictive variables. Our analysis revealed no statistically significant predictors of clinical response. This absence of identifiable predictors has several implications. First, it suggests that the therapeutic effect of memantine may be broadly applicable and not restricted to an identifiable clinical subgroup based on the variables we assessed. This supports a strategy of considering memantine augmentation for a wide range of patients with OCD who have failed standard treatments. Second, our negative findings underscore the complexity and heterogeneity of the pathophysiology of treatment-resistant patients. The underlying mechanisms of response to glutamatergic modulation may be more subtle than what is measurable by conventional clinical criteria. Future research should focus on larger, multicenter samples to identify smaller effect sizes, enable robust subgroup analyses, and explore prospective biomarkers, including neuroimaging and genetic markers related to glutamate signaling. Personalized treatment in this challenging clinical situation will remain a subject of future research.
5.12. Limitations
This study had several limitations. First, the study was designed as a retrospective study based on clinical record data, which may be subject to data recording bias or incomplete information. Second, sampling was conducted using the convenience sampling method, which may cause incomplete representation of the target population and reduce the generalizability of the results. Third, we were only able to examine the predictive effect of conventional clinical and demographic variables. Fourth, neuropsychological, neuroimaging, and neurophysiological variables were not examined in our study. Finally, the study was underpowered to detect small-to-moderate predictive effects. Post-hoc power analysis indicated that, given the sample size (N = 94) and the distribution of predictors, the study had adequate power (80%) to detect only large effect sizes (OR, 3.4). Consequently, the absence of significant predictors in our analysis should be interpreted with caution, as subtle associations might have been missed due to limited statistical power.






