1. Background
Cardiovascular disease (CVD) was the main cause of death worldwide in 2013, accounting for approximately 31.5% of the total global mortality rate (1, 2). Similarly, according to the latest reports, it is estimated that 92 million people have at least one type of CVD. By the year 2030, 43.9% of the world’s adult population is expected to have some type of CVD (3). With the enhancement of multislice computed tomography (MSCT) technology, coronary CT angiography (CCTA) has been usually selected to check for possible CVD as a noninvasive method (4).
Although the heart is the target organ in CCTA examinations, susceptible breast tissue is also in the main field of the beam, despite the fact that it is not the organ intended in the diagnosis. This problem particularly increases the risk of cancer in young women (5, 6). So, like all cardiac imaging modalities, concerns about the increase in radiation dose have led to different approaches aimed at decreasing radiation risks (7). In most studies, researchers have reported that CT doses of coronary angiography are 6 to 40 mSv based on the CT model and the detector type (8-10).
Thus, to move towards preserving general health, using bismuth shields is a reccommended assay for reducing radiation doses in female breast during MDCT examinations (11-15). For the first time, Hopper et al. (16) reported that bismuth shields can decrease the average radiation dose by 57%. But they did not analyze image quality. Bismuth shielding is also a suggested method to reduce the radiation dose of superficial sensitive organs in CCTA. Abadi et al., without reporting image quality analysis, showed that bismuth breast shielding can decrease entrance dose by 46.8% during CCTA examinations (17). Yilmaz et al. explained the amount of dose reduction using a bismuth composite shield when performing coronary calcium scoring during MDCT (18). It was found that the breast shield provided a 37.12% decrease in radiation dose. Thus, studies point to decreases in radiation levels in the breast tissue by approximately 50% using bismuth shields, but due to the absence or unavailability of these shields in all parts of the world, plus some concerns about bismuth shields increasing radiation dose through scatter (15) and lack of data or consensus about their impact on image quality, this technique is currently not being widely used. Studies have reported on the effects of breast bismuth shields on image quality during chest and lung CT exams, but there is little information to use in coronary CTA.
In this study, we are looking to improve the shape of bismuth shields for more efficient use in CT. A novel aspect of this research is a new bismuth composite form for shields as well as enhancements in size and belt shape of the composite bismuth shield. Also, the effect of shield thickness, the frequency of bismuth powder used, the size of female breast tissues and the dose absorbed in the skin and glandular positions were investigated as factors intervening in dose reduction.
2. Objectives
Due to the potential of bismuth shields for the protection of superficial radiosensitive organs against any unnecessary radiation during CCTA, we undertook a comparative dosimetry and image quality study on coronary CTA. In this study, quantitative analyses of image quality with and without the use of the bismuth composite shields in question were conducted in all cases, including bismuth percentage, shield thickness and breast size, along with measuring the doses of the skin and the glands.
3. Materials and Methods
3.1. Constructed Shields
We designed new belt bismuth-silicon composite shields by silicon rubber and bismuth micro particles (≤ 150μm) with different percentages and thicknesses. To make composite shields with 10% and 15% bismuth and a thickness of 1 mm and 1.5 mm with an area of 20 × 70 cm, bismuth powder was added to the silicon rubber after calculating the weight percentages and measuring accuracy. These shields were placed in the laboratory for two weeks in order for the composite mixtures to dry and to eliminate air bubbles (12). When they became stable, they were used for the experiments. The mass attenuation coefficient of bismuth composite shields was obtained using conventional digital radiology experimentally.
3.2. Female Chest Phantom and Imaging Protocol
A female chest phantom was designed and constructed in dosimetry laboratory of Medical Physics Department, Tabriz University of Medical Sciences (19). Two different breast sizes were considered for the female phantom. The female phantom was scanned using a SOMATOM Definition 128 CT (Siemens AG, Wittelsbacherplatz, Munenchen, Germany). The parameters of adult conventional chest scanning that were considered by the machine automatically (tube voltage of 120 kVp, effective tube current of 58 mA, slice thickness of 0.6 mm, the pitch of 1) were used for phantom imaging. One cm of foam was located between the shields and phantom, with the breasts covered. To avoid increasing the scan parameters with the shields, they were placed after the CT scout.
3.3. Image Quality Analysis
Bismuth-silicon composite shields were placed on normal and large breasts. The differences between CT numbers and noise of shielded and unshielded images were qualified. For this purpose, three and four circular regions of interest (ROIs) in the posterior and center (as a position of the heart) of the trunk and three ROIs in each breast, with an area of 2 by 2 cm, were selected to measure both the average Hounsfield unit (HU) and the standard deviation (SD). The measures of SD can be used as a quantitative assessment of noise within CT images. ROIs were selected in the trunk and breast of the phantom (in anterior, center and posterior) on one slice.
3.4. Dose Assessment
Dose measurements were conducted using 100 thermo-luminescent dosimeters (TLDs: GR-200) (Hangzhou Freq control Electronic Technology Ltd., China) on the location of the breasts. The calibration of the TLDs was performed by the Atomic Energy Organization of Iran, Karaj. Before use, the annealing of TLDs was done at 240ºC for 10 minutes. They were then immediately cooled to eliminate any residual light. A TLD reader (7103 model, Raman Security Development Co) was used to read the TLDs.
Every experiment was repeated three times. In the first time, the skin and glandular dose of normal and large breasts with and without composite shields 10% and 15% of bismuth, 1 mm were evaluated during CT angiography. In the second experiment, the skin and glandular dose of normal and large breasts in the state with and without composite shields 10% and 15% of bismuth, 1.5 mm were assessed. In the every session, to measure entrance skin dose (SD) at the level of the breast, four TLD chips were placed on each breast skin around the nipple. Also, to measure breast gland dose (GD), four TLDs were placed in the fourth layer of the large and normal breast phantoms for the glandular part of the breast. For each scan, sixteen TLDs were initially placed on the skin and the glands of each large and normal breasts with and without the presence of shields. Four TLDs that were unexposed were used as background readings. After reading each TLD, the element correction coefficient (ECC) was multiplied and the received dose of each TLD chip was obtained using the calibration curve. The average of the TLD doses was calculated and recorded.
3.5. Statistical Analysis
Paired t-test analysis with 95% confidence interval was performed using SPSS statistics software 22.0 (IBM Corp. Released 2013. IBM SPSS Statistics for Windows, Version 22.0. Armonk, NY: IBM Corp.) between groups with and without using different shields. Mean values of breast dose with and without different composite shield used to Paired t-test and P values were reported. Also, means and standard deviations of data were calculated using SPSS statistics software 22.0. All graphs were drawn using GraphPad Prism 6. The percentage of dose reduction as a result of bismuth shielding was calculated according to Formula 1:
Dose reduction (%) = [(Measured dose in without of shield - Measured dose in presense of shield)/Measured dose in without of shield] × 100
4. Results
4.1. Dose Measurement
The skin and glandular radiation doses of normal and large breasts were measured in the cardiac CT angiography with and without using different belt bismuth-silicon composite shields (Figure 1). The recorded skin and the glandular dose of normal and large breasts averaged as follows: 7.00 mGy (normal breast skin dose), 8.50 mGy (normal breast gland dose), 7.80 mGy (large breast skin dose), and 8.90 mGy (large breast gland dose) before applying shields. Using the 10% bismuth composite shields with thicknesses of 1mm and 1.5 mm reduced the dose. The average TLD readings following this were: 6.05 mGy and 6.00 mGy (normal breast skin dose), 7.80 mGy and 7.70 mGy (normal breast gland dose), 6.30 mGy and 5.91 mGy (large breast skin dose), and 7.70 mGy and 7.10 mGy (large breast gland dose). Also, the results of using the 15% bismuth composite shields by a thickness of 1 mm and 1.5 mm showed that the average absorbed doses significantly decreased. The recorded skin and gland average dose at the normal and large breasts with and without using different bismuth-silicon shields are presented in Figure 1. It is easy to see a noticeable difference in the breast dose between skin and gland. Moreover, a significant difference in the absorbed dose was also detected between normal and large breast (P value = 0.05). Statistical analysis results of presence of different composite shields is reported in Table 1.
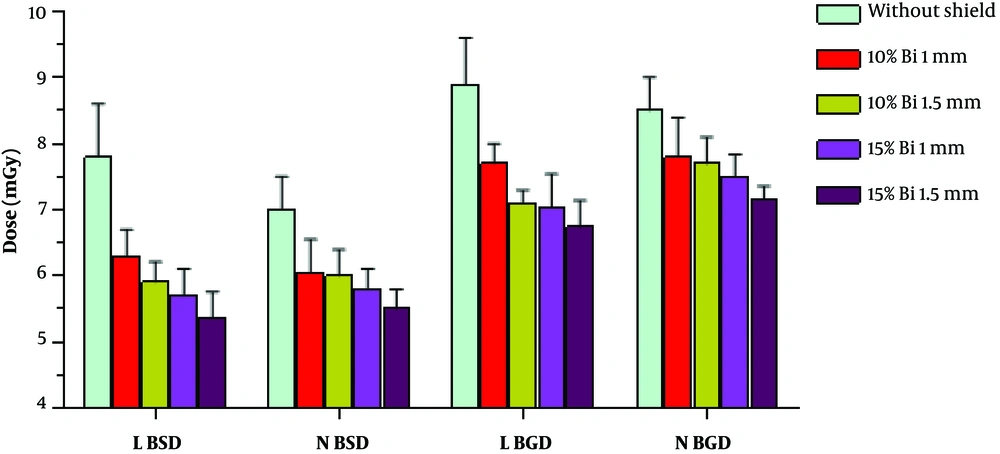
Figure 1.
Recorded dose in the skin and glandular tissue of breast in coronary CT angiography exams without and with bismuth shields (in different bismuthe percentages and shield thicknesses) (N BSD, normal breast skin dose; N BGD, normal breast glandular dose; L BSD, large breast skin dose; L BGD, large breast glandular dose)
Table 1.
Paired t-Test Analysis (P Value) of Breast Dose With and Without the Use of Different Composite Shields
| 10% Bi 1 mm | 10% Bi 1.5 mm | 15% Bi 1 mm | 15% Bi 1.5 mm | |
|---|---|---|---|---|
| Without shield | 0.0079 | 0.0157 | 0.0098 | 0.0058 |
| 10% Bi 1 mm | - | 0.1142 | 0.0223 | 0.0051 |
| 10% Bi 1.5 mm | - | - | 0.0186 | 0.0016 |
| 15% Bi 1 mm | - | - | - | 0.0001 |
Abbreviation: Bi, bismuth
4.2. Dose Reduction
Reduction in skin and glandular for normal and large breasts using belt bismuth-silicon composite shields is summarized in Table 2. The 1 mm and 1.5 mm of 10% breast bismuth composite shield decreased the absorbed skin dose by 13.57% and 14.28% in the normal breast phantom and 19.23% and 24.23% in the large breast phantom, respectively. Also, they led to reductions in glandular dose by 8.23% and 9.41% in the normal breast and 13.48% and 20.22% in the large breast phantom, respectively. Thus, it is clear that dose reduction depends on shield thickness, skin or glandular position and breast size. Similarly, the 1 mm and 1.5 mm of 15% breast bismuth composite shield reduced the skin and glandular dose significantly more than the 10% bismuth composite shield in normal and large breasts (Table 2).
Table 2.
Dose Reduction (%) in the Skin and Glandular of Breast Tissue in Coronary CT Angiography Exams Due to Different Belt Bismuth-Silicon Composite Shields
| Phantom | 10% Bi | 15% Bi | ||
|---|---|---|---|---|
| 1 mm | 1.5 mm | 1 mm | 1.5 mm | |
| L BSD | 19.23 | 24.23 | 26.92 | 31.28 |
| N BSD | 13.57 | 14.28 | 17.14 | 21.42 |
| L BGD | 13.48 | 20.22 | 20.89 | 24.26 |
| N BGD | 8.23 | 9.41 | 11.76 | 15.76 |
Abbreviations: Bi, bismuth; L BGD, large breast glandular dose; L BSD, large breast skin dose; N BGD, normal breast glandular dose; N BSD, normal breast skin dose.
4.3. Image Quality Assessment
The location of phantoms and the shield on the breasts is shown in Figure 2A. Also, the quantitative assessment of image quality was considered by measuring the signal [CT number] and noise level [SD] as shown in Figure 2B.
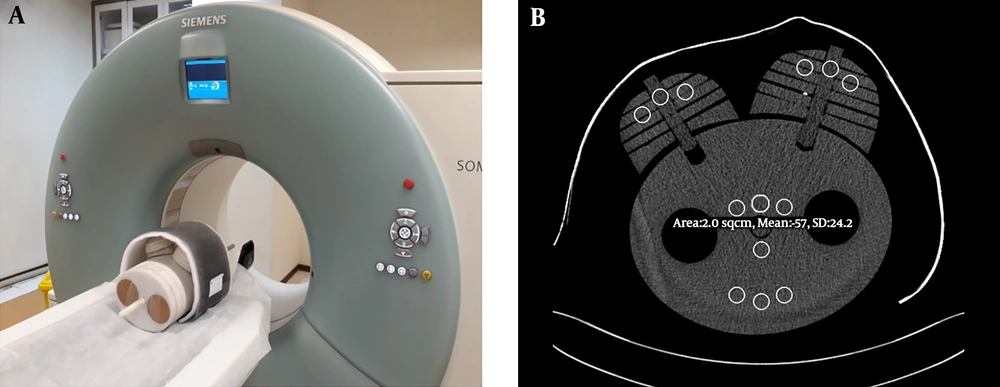
Figure 2.
Image quality assessment in regions of interest of chest phantom with and without different belt bismuth-silicon composite shields. A, Female chest phantom covered by belt bismuth-silicon composite shield and 1 cm foam. B, Three areas were selected to analysis image quality. The regions of interest (ROIs) were defined according to anterior, central and posterior area under the shield.
Mean values of CT number and noise levels in the anterior (breast), the center (heart) and posterior of the images are shown in Table 3. The mean CT number without shielding was -55.7 HU. As a result of using bismuth composite shields, the mean CT numbers dropped to -54.0 and 53.1 for 10% bismuth shield with thicknesses of 1 mm, 1.5 mm, and -51.5 and -50.06 for 15% bismuth shield with thicknesses of 1mm and 1.5 mm, respectively.
Table 3.
Mean CT Number and Noise Values Measured in Images Obtained from Coronary CT Angiography Scans Performed With and Without Bismuth-Silicon Composite Shields
| Shields | Anterior region | Central region | Posterior region | Mean | ||||
|---|---|---|---|---|---|---|---|---|
| CT number | Noise | CT number | Noise | CT number | Noise | CT number | Noise | |
| Reference | - 59.2 | 22.2 | -55.6 | 21.7 | -52.3 | 20.4 | -55.7 | 21.43 |
| 10% Bi 1 mm | -58.1 | 24 | -54.5 | 22.6 | -49.4 | 21.5 | -54.0 | 22.7 |
| 10% Bi 1.5 mm | -56.9 | 25.1 | -53.9 | 23.0 | -48.5 | 22.18 | -53.1 | 23.42 |
| 15% Bi 1 mm | -54.6 | 27.4 | -53.1 | 25.4 | -46.8 | 24.2 | -51.5 | 25.67 |
| 15% Bi 1.5 mm | - 53.4 | 29.7 | -51.5 | 27.1 | -45.3 | 24.8 | -50.06 | 27.2 |
Abbreviation: Bi, bismuth
The mean noise without shielding was 21.43 HU; while, by using 10% bismuth shield at 1 mm, and 1.5 mm thickness, the noise obtained was 22.7 and 23.42. Also, the mean noise level was 25.67 and 27.2 due to using 15% bismuth shield 1 mm and 1.5 mm thick, respectively. Consequently, it was found that with increasing frequency percentage of bismuth powder at the shields with constant thickness, noise significantly increased. It is clear that the use of 15% and 10% bismuth shields with 1.5 mm showed an increase in the noise on the anterior, central and posterior region more than is the case without shield condition (Figure 3). In addition, the highest amount of noise was observed in the anterior (breasts) region, while the amount of noise in the center area (heart) was significantly less on corresponding images.
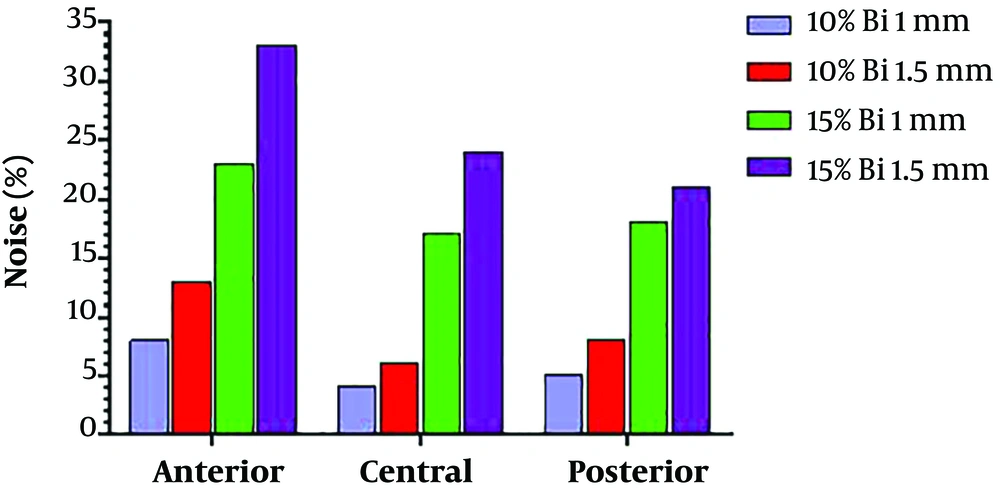
Figure 3.
Noise levels at the anterior (breast region), central (heart region) and posterior area in coronary CT angiography images due to different belt bismuth - silicon composite shields.
Overall, by using bismuth composite shields noise was enlarged and spread over the whole image. The noise was generally observed under the shielded area and these artifacts were mainly found in the region of the breast where they are not essentially important for diagnosis in CCTA. The differences in noise with and without shields are significant, but in the region of the heart, they would be acceptable for some diagnostic purposes.
5. Discussion
This study introduced bismuth composite shields which possess the potential to protect breasts against radiation during coronary CT angiography. The rate of dose reduction depends on shield characteristics as well as organ size.
The study of the possible effects of organ size on the radiation dose received showed that the glandular and skin doses of the large breast were higher than for normal breasts. Also, the glandular dose of both large and normal breasts was higher than that of the skin dose. Thus, the use of different bismuth composite shields reduced breast dose from CCTA by 8% - 31%, in proportion to breast size. There is good agreement between the findings from our dose reduction rates and those by available studies on chest CT for the breast (20, 21).
Other important factors affecting dose reduction were shield thickness and bismuth weight percentage. Comparison of dose reduction for 10% and 15% bismuth shields with the same thickness showed that increasing the percentage of bismuth significantly does lead to dose reduction. In case of increasing shield thickness from 1 mm to 1.5 mm with the same bismuth percentage, we also saw an increase in attenuation but it was not significant. So, the effect of bismuth percentage and shield thickness data showed that variation in the amount of attenuation is slight because it is only due to increases in thickness.
Today, the debate is focused on the influences on image quality, especially CT number changes, increasing noise and beam hardening artifacts, probably compromising diagnostic accuracy (22). Hopper et al. (23) exhibited that the eye shield produced artifacts under the shield but not into the brain area. In addition, Colombo et al. studied image quality decline in areas under a breast shield but not in areas of diagnostic interest for chest CT, and noteworthy rise in image noise only in the anterior portions of the lung during chest CT examination (24). Regarding the importance of using foams between the shield and the target organ, we put one cm of foam between the shields and the phantom. In our study, the measured noise was higher with the bismuth shield, as opposed to without it, but it was not significant. Additionally, quantitative measures showed that noise in the area of coronary arteries, which are the main target for optimal image quality in CCTA, was slightly lower than that under the shield. Moreover, most radiological diagnostic processes were assessed by visual checks undertaken by radiologists not solely reliant on HU statistics.
The breast shields used in our study differed from commercially available shields in several ways. First, the breast shields were constructed from bismuth-silicon composite shields with a one-cm foam. The second difference is the percentage of bismuth particles used in the shield. The current commercially available shields are constructed in four-layer thicknesses (3.4 gr of bismuth per square centimeter, AttenuRad CT Radio-protective; F & L Medical Products) (25).
Despite the innovative approach, some of the limitations of this study deserve consideration. Like many of studies, we used a phantom to measure the received dose of breast with and without the presence of shields. Additionally, it was also better to use human samples to check the quality of images when using shields.
In conclusion, this study supports the view that newly designed and prepared bismuth composite shields can play an important role in dose optimization during CCTA scanning, particularly for superficial organs. We found three effective factors in dose reduction including breast size, shield thickness and bismuth weight percentage. Dose reductions in skin layer are larger and more significant than in the glandular layer for both large and normal breasts sizes. Thicker shields with high percentages of bismuth in them made better dose reductions possible. Image noise was within an acceptable range for CCTA diagnosis process.