Cover image of the article: A Narrative Review of Menstrual Health Rights in Low- and Middle-Income Countries: Advocating for Supportive Policies and Legal Frameworks

Image Credit:J Health Rep Technol

A Narrative Review of Menstrual Health Rights in Low- and Middle-Income Countries: Advocating for Supportive Policies and Legal Frameworks

Authors

Roland Nnaemeka OkoroRoland Nnaemeka Okoro ORCID1,*, Deborah Oyine AluhDeborah Oyine Aluh ORCID2, 3, Chinelo Nneka Aguiyi-Ikeanyi2
1Department of Clinical Pharmacy and Pharmacy Administration, University of Maiduguri, Maiduguri, Nigeria
2Department of Clinical Pharmacy and Pharmacy Management, University of Nigeria Nsukka, Nsukka, Nigeria
3Lisbon Institute of Global Mental Health (LIGMH), NOVA Medical School, NOVA University of Lisbon, Lisboa, Portugal
*Corresponding Author: Okoro Roland Nnaemeka, Department of Clinical Pharmacy and Pharmacy Administration, University of Maiduguri, Maiduguri, Nigeria. Email: orolandn@gmail.com

Journal of Health Reports and Technology:Vol. 11, issue 1; e147981
Published online:Jan 31, 2025
Article type:Systematic Review
Received:Sep 20, 2024
Accepted:Jan 23, 2025
How to Cite:Okoro RN, Aluh DO, Aguiyi-Ikeanyi CN. A Narrative Review of Menstrual Health Rights in Low- and Middle-Income Countries: Advocating for Supportive Policies and Legal Frameworks. J Health Rep Technol. 2025;11(1):e147981. doi: https://doi.org/10.5812/jhrt-147981

Abstract

Context:

Menstrual health is a critical component of sexual and reproductive health, which is deeply intertwined with human rights, gender equality, and sustainable development. Despite its importance, menstrual health management remains a significant challenge, particularly in low- and middle-income countries (LMICs), due to systemic barriers, cultural stigmas, and resource limitations. This paper aims to highlight the barriers to effective menstrual health management in LMICs, and their impact on health, educational and social, and economic outcomes.

Evidence Acquisition:

A narrative review of the literature was conducted with a search across major academic databases, including PubMed, Scopus, Web of Science, and Google Scholar for peer-reviewed articles and reports. Grey literature was also reviewed using repositories such as WHO, UNICEF, and other global health organizations. Key information, including barriers, and reported outcomes was extracted and synthesized using a thematic approach.

Results:

Key barriers to menstrual health include poor hygiene infrastructure, lack of access to menstrual products, economic constraints, cultural taboos, and inadequate policies. These barriers led to adverse outcomes such as reproductive tract infections, poor academic performance, gender-based violence, and stigma. Overall, inadequate menstrual health management exacerbates inequalities and undermines the well-being of girls and women in LMICs.

Conclusions:

Addressing menstrual health through informed policies and laws is essential to ensuring the dignity, health, and rights of girls and women in LMICs. Comprehensive education and access to menstrual products must be prioritized to mitigate the adverse outcomes associated with poor menstrual health.

Highlights

1. Context

Menstrual health is a fundamental yet often overlooked component of sexual and reproductive health, which is deeply interwoven with human rights, gender equality, and sustainable development. While menstruation is a natural biological process, it remains stigmatized and inadequately addressed in many societies, particularly in low- and middle-income countries (LMICs) (1). The consequences of this neglect extend beyond physical health, impacting education, economic empowerment, and overall well-being.
In LMICs, several barriers perpetuate inequality and compromise the dignity of menstruating individuals. Adolescent girls often face menarche unprepared, leading to feelings of shame, confusion, and social isolation. Additionally, harmful practices and societal taboos exacerbate the challenges of managing menstruation safely and hygienically. The intersection of menstrual health with the United Nations Sustainable Development Goals (SDGs) highlights its significance in achieving global priorities, including gender equality (SDG 5), quality education (SDG 4), clean water and sanitation (SDG 6), and good health and well-being (SDG 3) (2). Addressing menstrual health issues is therefore not only a matter of public health priority but also a critical step toward empowering women and gender-diverse individuals, fostering inclusive development, and dismantling systemic inequities.
The review of literature explores the barriers to effective menstrual health management in LMICs and examines the health, educational and social, and economic consequences of poor menstrual health. By identifying actionable solutions and emphasizing the urgency of integrating menstrual health into global and national development agendas, this work aims to advocate for systemic change and the realization of menstrual health as a human right.

2. Evidence Acquisition

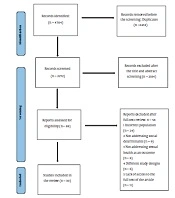
A narrative review was conducted to identify the barriers and adverse outcomes associated with poor menstrual health in LMICs. A comprehensive search strategy was employed to identify relevant literature on menstrual health in LMICs. Major academic databases, including PubMed, Scopus, Web of Science, and Google Scholar, were searched for peer-reviewed articles. Grey literature was also reviewed using repositories such as WHO, UNICEF, and other global health organizations. The search terms included a combination of keywords and medical subject headings (MeSH) terms such as "menstrual health", "menstrual hygiene management", "low- and middle-income countries", "barriers", "stigma", "adolescent girls", and "health outcomes". Inclusion criteria were studies focused on menstrual health in LMICs, articles published in English between 2000 and 2024, menstrual health research addressing barriers, health, educational and social, and economic outcomes consequences. Exclusion criteria were studies that focused solely on high-income countries, non-English publications or those lacking full-text access, and articles with limited relevance to the research objectives. Titles and abstracts were screened for relevance, followed by a full-text review of shortlisted articles. Discrepancies in selection were resolved through discussion among the reviewers. Key information, including barriers identified, and reported outcomes was extracted and synthesized using a thematic approach. A total of 100 articles were identified through the initial search across databases and grey literature sources. After removing duplicates and screening titles and abstracts for relevance, 50 articles were shortlisted for full-text review. Following the application of inclusion and exclusion criteria, 25 articles were deemed eligible and included in this review.

3. Results

3.1. Barriers to Menstrual Health

The review identified multiple barriers to effective menstrual health management, which are categorized into structural, cultural, and systemic domains:

3.1.1. Structural Barriers

- Inadequate menstrual hygiene infrastructure, including the lack of clean water and sanitation facilities (3, 4).
- Limited access to affordable menstrual products, particularly in rural and low-income settings (4-7).
- Economic constraints, exacerbated by broader poverty and inequality issues (4, 5, 7).
- Displacement and humanitarian crises, which disrupt access to basic menstrual health services (8).
- Accessibility challenges for individuals with disabilities (9).

3.1.2. Cultural Barriers

- Stigma and taboo surrounding menstruation, perpetuating feelings of shame and secrecy (5).
- Harmful cultural and religious beliefs that marginalize menstruating women (5, 10).
- Gender inequality and discrimination, limiting women's agency and decision-making power (11).

3.1.3. Systemic Barriers

- Limited education on menstruation and reproductive health, leaving many adolescents unprepared for menarche (12, 13).
- Inadequate training and awareness among healthcare providers regarding menstrual health (14).
- Policy and legal gaps, including the absence of comprehensive frameworks supporting menstrual health rights (15, 16).

3.2. Consequences of Poor Menstrual Health

The barriers to effective menstrual health management have far-reaching implications such as:

3.2.1. Health Impact

- Increased risk of reproductive tract infections (RTIs), urinary tract infections (UTIs), and other hygiene-related illnesses (17, 18).
- Vulnerability to HIV and sexually transmitted infections (STIs) due to poor menstrual hygiene practices (19).
- Secondary infertility and adverse pregnancy outcomes linked to untreated RTIs (20).
- Heightened risk of drug-related problems (21, 22).

3.2.2. Educational and Social Impact

- Missed school days and reduced academic performance due to inadequate menstrual health resources and facilities (5, 13, 23).
- Heightened vulnerability to gender-based violence, including harassment and assault, particularly in schools and public spaces without adequate sanitation facilities (24-26).
- Perpetuation of stigma and social isolation, undermining mental health and self-esteem (5).

3.2.3. Economic Impact

- Reduced workforce participation and productivity among women due to the lack of workplace accommodations for menstruation (15, 27).
- Financial burdens associated with purchasing menstrual products, particularly for low-income families (5).
The findings underscore the need for a multifaceted approach to addressing menstrual health challenges. This includes:
- Expanding access to affordable and sustainable menstrual products.
- Improving WASH facilities in schools, workplaces, and public spaces.
- Promoting comprehensive menstrual health education for adolescents and communities.
- Developing and implementing policies to protect menstrual health rights and eliminate stigma.
- Strengthening healthcare systems to provide better support for menstrual health management.

4. Discussion

Menstruation, a natural and healthy part of life for most women, is surrounded by various challenges, particularly in LMICs. Systemic barriers and biases perpetuate menstrual inequality and stigma (5), necessitating urgent societal change to ensure that all women can manage menstruation with dignity and respect. Adolescents in many LMICs often lack basic knowledge about menstruation and menstrual-related disorders (12, 28). For many, menstruation begins without prior education or preparation, leading to feelings of confusion, humiliation, and distress (13). Cultural taboos and societal stigma exacerbate these issues, leaving adolescents to navigate their menstrual health in isolation. Harmful cultural and religious practices, such as menstrual seclusion, further perpetuate inequality and limit access to proper menstrual health resources. Restrictive gender roles and social norms in LMICs often deprive girls and women of decision-making power and the resources required for adequate menstrual management. In addition, economic constraints limit access to essential commercial menstrual products, such as sanitary pads, tampons, or menstrual cups. The situation is even more dire in refugee or crisis settings, where menstrual health services and facilities are often non-existent.
Inadequate facilities for menstrual product disposal, washing, and drying, coupled with limited access to clean water, sanitation, and hygiene (WASH) facilities, present significant challenges for menstrual health management. Girls and women with disabilities face additional barriers, as do those in LMICs without healthcare providers adequately trained in menstrual health. Policy and legal gaps further complicate efforts to ensure comprehensive support for menstrual health and rights.
The consequences of poor menstrual health are far-reaching and severe. Unhygienic practices, such as using improperly cleaned cloths or absorbent alternatives like grass or tissue, can lead to RTIs, UTIs, and other health complications (20). If untreated, RTIs may increase vulnerability to HIV, STIs, and secondary infertility (20). Additionally, poor menstrual health practices contribute to adverse pregnancy outcomes (20) and health risks associated with transactional sex, which some girls could engage in to afford menstrual products.
Educational disruptions caused by menstrual health issues are significant. Many girls miss school due to inadequate sanitation facilities, fear, or dysmenorrhoea, resulting in compromised academic performance (5, 13, 23). Furthermore, the lack of WASH facilities in schools exacerbates gender-based violence risks, as girls become more vulnerable to harassment and assault during menstruation (3). Menstruation, as common as it is, is stigmatized all over the world, particularly in LMICs (29). Stigma surrounding menstruation negatively impacts women’s health, sexuality, well-being, and social standing, perpetuating cycles of inequality (11).
Self-medication for menstrual-related illnesses, including dysmenorrhoea, is prevalent in LMICs (30-36). Many adolescents use non-steroidal anti-inflammatory drugs (NSAIDs) or antispasmodic medications without proper medical guidance, leading to potential adverse drug events. In some cases, combinations of NSAIDs and antibiotics have been reported (21), raising concerns about safety and efficacy.
To ensure menstrual health and sexual and reproductive rights for all girls and women, integrating menstrual health into broader sexual and reproductive health rights initiatives is critical. Educational programmes covering menstrual health, anatomy, and hygiene should target young girls before menarche, promoting confidence, solidarity, and healthy practices. Governments, non-governmental organizations, and multilateral organizations must prioritize menstrual health by ensuring access to clean water, adequate WASH facilities, and affordable menstrual products. Policies such as tax exemptions on menstrual products and support for social entrepreneurship can enhance accessibility for low-income populations. Governments in countries like India, Kenya, South Africa, and Uganda have made commendable strides by pledging to improve access to sanitary products for low-income girls (37, 38). Legal frameworks should also address harmful practices such as female genital mutilation, enforce gender equality, and protect individuals from discrimination based on menstruation or gender. Comprehensive healthcare policies must prioritize menstrual health services, including contraception and pain management, while ensuring these services are accessible even in crisis situations.
Investing in menstrual health research will further refine policies and practices, ensuring that systemic barriers and stigmas surrounding menstruation are effectively addressed. Collaborative efforts between governments, global health partners, and the corporate sector can promote menstrual health, dignity, and equality, creating a world where menstruation is no longer a barrier to well-being and empowerment. The review is limited by its reliance on secondary data, which may not capture recent policy developments or grassroots-level insights.

5. Conclusions

Menstrual health is an essential component of sexual and reproductive health, with far-reaching implications for gender equality, education, and economic empowerment. Addressing the systemic and structural barriers, and cultural stigmas that surround menstruation, particularly in LMICs, is critical to promoting dignity and well-being for all individuals. Ensuring access to education, affordable menstrual products, and adequate WASH facilities, alongside enacting supportive policies and legal frameworks, can help combat the challenges associated with poor menstrual health. Governments, non-governmental organizations, and global partners must work collaboratively to prioritize menstrual health and integrate it into broader development goals. By addressing menstrual health inequities, we can empower girls and women, enhance their participation in society, and contribute to achieving the Sustainable Development Goals. Through sustained advocacy, investment, and action, menstruation can become a symbol of empowerment rather than a barrier, fostering a more equitable and inclusive future.


Footnotes

  • Authors' Contribution: R. N. O.: Study concept and design, literature review, drafting of the manuscript, critical revision of the manuscript for important intellectual content; D. O. A.: Literature review, drafting of the manuscript, critical revision of the manuscript for important intellectual content; C. N. A.: Literature review, drafting of the manuscript, critical revision of the manuscript for important intellectual content.

  • Conflict of Interests Statement: The author declared no conflict of interest.

  • Data Availability: The dataset presented in the study is available on request from the corresponding author during submission or after publication.

  • Funding/Support: This work was self-funded by the authors.

References

  • 1.
    Mohammed S, Larsen-Reindorf RE. Menstrual knowledge, sociocultural restrictions, and barriers to menstrual hygiene management in Ghana: Evidence from a multi-method survey among adolescent schoolgirls and schoolboys. PLoS One. 2020;15(10). e0241106. [PubMed ID: 33091080]. [PubMed Central ID: PMC7580927]. https://doi.org/10.1371/journal.pone.0241106.
  • 2.
    United Nations. Department of Economic and Social Affairs (Sustainable Development). 2024, [cited 2024]. Available from: https://sdgs.un.org/goals.
  • 3.
    Sommer M, Ferron S, Cavill S, House S. Violence, gender and WASH: spurring action on a complex, under-documented and sensitive topic. Environ Urbaniz. 2014;27(1):105-16. https://doi.org/10.1177/0956247814564528.
  • 4.
    Rossouw L, Ross H. Understanding Period Poverty: Socio-Economic Inequalities in Menstrual Hygiene Management in Eight Low- and Middle-Income Countries. Int J Environ Res Public Health. 2021;18(5). [PubMed ID: 33806590]. [PubMed Central ID: PMC7967348]. https://doi.org/10.3390/ijerph18052571.
  • 5.
    Sure RA, Odek A, Otuya P. Socio Economic Determinants and Effective Menstrual Management among Primary School Girls in Rural Schools in Nyatike Sub County. African J Empirical Res. 2023;4(2):964-75. https://doi.org/10.51867/ajernet.4.2.98.
  • 6.
    Biswas S, Alam A, Islam N, Roy R, Satpati L. Understanding period product use among young women in rural and urban India from a geospatial perspective. Sci Rep. 2024;14(1):20114. [PubMed ID: 39209872]. [PubMed Central ID: PMC11362602]. https://doi.org/10.1038/s41598-024-70383-w.
  • 7.
    Roy N, Amin MB, Aktarujjaman M, Hossain E, Mugo C, Islam F, et al. Cross-national variation in the prevalence and correlates of current use of reusable menstrual materials: Analysis of 42 cross-sectional surveys in low-income, lower-middle-income, and upper-middle-income countries. PLoS One. 2024;19(10). e0310451. [PubMed ID: 39374244]. [PubMed Central ID: PMC11458041]. https://doi.org/10.1371/journal.pone.0310451.
  • 8.
    Hirani SAA. Barriers to Women's Menstrual Hygiene Practices during Recurrent Disasters and Displacement: A Qualitative Study. Int J Environ Res Public Health. 2024;21(2). [PubMed ID: 38397644]. [PubMed Central ID: PMC10888390]. https://doi.org/10.3390/ijerph21020153.
  • 9.
    Wilbur J, Torondel B, Hameed S, Mahon T, Kuper H. Systematic review of menstrual hygiene management requirements, its barriers and strategies for disabled people. PLoS One. 2019;14(2). e0210974. [PubMed ID: 30726254]. [PubMed Central ID: PMC6365059]. https://doi.org/10.1371/journal.pone.0210974.
  • 10.
    Mohamed Y, Durrant K, Huggett C, Davis J, Macintyre A, Menu S, et al. A qualitative exploration of menstruation-related restrictive practices in Fiji, Solomon Islands and Papua New Guinea. PLoS One. 2018;13(12). e0208224. [PubMed ID: 30507969]. [PubMed Central ID: PMC6277107]. https://doi.org/10.1371/journal.pone.0208224.
  • 11.
    Wigle JM, Paul S, Birn AE, Gladstone B, Kalolo M, Banda L, et al. Participation of young women in sexual and reproductive health decision-making in Malawi: Local realities versus global rhetoric. PLOS Glob Public Health. 2022;2(11). e0001297. [PubMed ID: 36962663]. [PubMed Central ID: PMC10022123]. https://doi.org/10.1371/journal.pgph.0001297.
  • 12.
    Ogunfowokan AA, Babatunde OA. Management of primary dysmenorrhea by school adolescents in ILE-IFE, Nigeria. J Sch Nurs. 2010;26(2):131-6. [PubMed ID: 19850951]. https://doi.org/10.1177/1059840509349723.
  • 13.
    Tegegne TK, Sisay MM. Menstrual hygiene management and school absenteeism among female adolescent students in Northeast Ethiopia. BMC Public Health. 2014;14:1118. [PubMed ID: 25355406]. [PubMed Central ID: PMC4232635]. https://doi.org/10.1186/1471-2458-14-1118.
  • 14.
    Davile M, Gangane N, Khan MF, Dange S, Mundle S. Exploring Menstrual Hygiene Practices and Awareness of Menstrual Cups Among Nursing Professionals: A Cross-Sectional Survey. Cureus. 2024;16(5). e61179. [PubMed ID: 38933610]. [PubMed Central ID: PMC11205264]. https://doi.org/10.7759/cureus.61179.
  • 15.
    Fry W, Njagi JW, Houck F, Avni M, Krishna A. Improving Women’s Opportunities to Succeed in the Workplace: Addressing Workplace Policies in Support of Menstrual Health and Hygiene in Two Kenyan Factories. Sustainability. 2022;14(8). https://doi.org/10.3390/su14084521.
  • 16.
    Asomadu N. Access to Menstrual Hygiene Products in Nigeria: A Call for Legal Reforms. J Commercial Property Law. 2024;11(3):82-8.
  • 17.
    Singh A, Kushwaha S. Awareness about reproductive tract infection, its relation with menstrual hygiene management and health seeking behaviour: A cross-sectional study among adolescent girls of Lucknow. J Family Med Prim Care. 2022;11(11):6690-6. [PubMed ID: 36993070]. [PubMed Central ID: PMC10041320]. https://doi.org/10.4103/jfmpc.jfmpc_510_21.
  • 18.
    Al Karmi J, Alshrouf MA, Haddad TA, Alhanbali AE, Raiq NA, Ghanem H, et al. Urinary and reproductive tract infection symptoms and menstrual hygiene practices in refugee camps in Jordan: A cross-sectional study. Womens Health (Lond). 2024;20:17455057241240900. [PubMed ID: 38576125]. [PubMed Central ID: PMC10996361]. https://doi.org/10.1177/17455057241240920.
  • 19.
    Zulaika G, Otieno FO, Mason L, van Eijk AM, Bhaumik R, Green SJ, et al. Menstrual cups to reduce bacterial vaginosis and STIs through reduced harmful sexual and menstrual practices among economically vulnerable women: protocol of a single arm trial in western Kenya. BMC Public Health. 2024;24(1):3089. [PubMed ID: 39516733]. [PubMed Central ID: PMC11545970]. https://doi.org/10.1186/s12889-024-20491-z.
  • 20.
    House S, Mahon T, Cavill S. Menstrual hygiene matters: a resource for improving menstrual hygiene around the world. New York, USA; 2012, [cited 2024]. Available from: https://washmatters.wateraid.org/sites/g/files/jkxoof256/files/Menstrual%20hygiene%20matters%20low%20resolution.pdf.
  • 21.
    Okoro RN, Malgwi H, Ngong CK, Okoro GO. Dysmenorrhoea: Ways of Management among Nigerian University Students. Actual Gynecol Obstetrics. 2012;4.
  • 22.
    Parisa N, M. Khairul Kahfi Pasaribu, Bintang Arroyantri P, Ardesy Melizah K, Ziske M. Patterns of Using Analgesics for Menstrual Pain in Female Students Sriwijaya University Faculty of Medicine. Arch Med Case Rep. 2021;1(2):49-57. https://doi.org/10.37275/amcr.v1i2.10.
  • 23.
    Shah V, Nabwera H, Sonko B, Bajo F, Faal F, Saidykhan M, et al. Effects of Menstrual Health and Hygiene on School Absenteeism and Drop-Out among Adolescent Girls in Rural Gambia. Int J Environ Res Public Health. 2022;19(6). [PubMed ID: 35329020]. [PubMed Central ID: PMC8954348]. https://doi.org/10.3390/ijerph19063337.
  • 24.
    Stevenson EG, Ambelu A, Caruso BA, Tesfaye Y, Freeman MC. Community Water Improvement, Household Water Insecurity, and Women's Psychological Distress: An Intervention and Control Study in Ethiopia. PLoS One. 2016;11(4). e0153432. [PubMed ID: 27124391]. [PubMed Central ID: PMC4849673]. https://doi.org/10.1371/journal.pone.0153432.
  • 25.
    Caruso BA, Clasen TF, Hadley C, Yount KM, Haardorfer R, Rout M, et al. Understanding and defining sanitation insecurity: women's gendered experiences of urination, defecation and menstruation in rural Odisha, India. BMJ Glob Health. 2017;2(4). e000414. [PubMed ID: 29071131]. [PubMed Central ID: PMC5640070]. https://doi.org/10.1136/bmjgh-2017-000414.
  • 26.
    Caruso BA, Cooper HLF, Haardorfer R, Yount KM, Routray P, Torondel B, et al. The association between women's sanitation experiences and mental health: A cross-sectional study in Rural, Odisha India. SSM Popul Health. 2018;5:257-66. [PubMed ID: 30094321]. [PubMed Central ID: PMC6077264]. https://doi.org/10.1016/j.ssmph.2018.06.005.
  • 27.
    Sommer M, Chandraratna S, Cavill S, Mahon T, Phillips-Howard P. Managing menstruation in the workplace: an overlooked issue in low- and middle-income countries. Int J Equity Health. 2016;15:86. [PubMed ID: 27268416]. [PubMed Central ID: PMC4895811]. https://doi.org/10.1186/s12939-016-0379-8.
  • 28.
    Chhabra S, Gokhale S, Yadav S. Premenarche information and dysmenorrhea in young girls. Insights Reprod Med. 2017;1(2):1-6.
  • 29.
    Holmes K, Curry C, Ferfolja T, Parry K, Smith C; Sherry, et al. Adolescent Menstrual Health Literacy in Low, Middle and High-Income Countries: A Narrative Review. Int J Environ Res Public Health. 2021;18(5). [PubMed ID: 33668788]. [PubMed Central ID: PMC7956698]. https://doi.org/10.3390/ijerph18052260.
  • 30.
    Kushwaha RP, Rauniar GP, Sarraf DP, Rai DS, Sinha P, Sitaula S, et al. Evaluation of the severity and self-management practice in primary dysmenorrhea in medical and dental students: A cross-sectional study in a teaching hospital. Asian J Med Sci. 2021;12(3):59-65.
  • 31.
    Ore TO, Ogundeko CA. Knowladge and self management of dysmenorrhea amang female adolescents in selected secondary school in Ogun State, Nigeria. Commonwealth J Acad Res. 2021;2(5):60-70.
  • 32.
    Sugumar R, Krishnaiah V, Channaveera GS, Mruthyunjaya S. Comparison of the pattern, efficacy, and tolerability of self-medicated drugs in primary dysmenorrhea: a questionnaire based survey. Indian J Pharmacol. 2013;45(2):180-3. [PubMed ID: 23716896]. [PubMed Central ID: PMC3660932]. https://doi.org/10.4103/0253-7613.108312.
  • 33.
    Yasir S, Kant B, Dar MF. Frequency of dysmenorrhoea, its impact and management strategies adopted by medical students. J Ayub Med Coll Abbottabad. 2014;26(3):349-52. [PubMed ID: 25671945].
  • 34.
    Osonuga A, Ekor M. Risk factors for dysmenorrhea among Ghanaian undergraduate students. Afr Health Sci. 2019;19(4):2993-3000. [PubMed ID: 32127874]. [PubMed Central ID: PMC7040311]. https://doi.org/10.4314/ahs.v19i4.20.
  • 35.
    Gebeyehu MB, Mekuria AB, Tefera YG, Andarge DA, Debay YB, Bejiga GS, et al. Prevalence, Impact, and Management Practice of Dysmenorrhea among University of Gondar Students, Northwestern Ethiopia: A Cross-Sectional Study. Int J Reprod Med. 2017;2017:3208276. [PubMed ID: 28589173]. [PubMed Central ID: PMC5446888]. https://doi.org/10.1155/2017/3208276.
  • 36.
    Abu Helwa HA, Mitaeb AA, Al-Hamshri S, Sweileh WM. Prevalence of dysmenorrhea and predictors of its pain intensity among Palestinian female university students. BMC Womens Health. 2018;18(1):18. [PubMed ID: 29334974]. [PubMed Central ID: PMC5769430]. https://doi.org/10.1186/s12905-018-0516-1.
  • 37.
    Sommer M, Hirsch JS, Nathanson C, Parker RG. Comfortably, Safely, and Without Shame: Defining Menstrual Hygiene Management as a Public Health Issue. Am J Public Health. 2015;105(7):1302-11. [PubMed ID: 25973831]. [PubMed Central ID: PMC4463372]. https://doi.org/10.2105/AJPH.2014.302525.
  • 38.
    Kasiko M. National best practice in advocacy for menstrual hygiene management for schools in Uganda. 4th Annual MHM and WASH in Schools Virtual Conference. Uganda. 2015.

Copyright

Copyright © 2025, Journal of Health Reports and Technology. This open-access article is available under the Creative Commons Attribution-NonCommercial 4.0 (CC BY-NC 4.0) International License (https://creativecommons.org/licenses/by-nc/4.0/), which allows for the copying and redistribution of the material only for noncommercial purposes, provided that the original work is properly cited.

Similar Articles

15
Oct
2020
A descriptive study of menstrual hygiene practices among women at the rural area of Haryana

A descriptive study of menstrual hygiene practices among women at the rural area of Haryana

Poonam Sheoran,
Simarjeet Kaur,
Hem Lata

Sheoran P, Kaur S, Lata H. A descriptive study of menstrual hygiene practices among women at the rural area of Haryana. J Nurs Midwifery Sci. 2020;7(4):e140775. doi: https://doi.org/10.4103/jnms.jnms_18_20

20
Jul
2021
Determining Health Literacy Level and Its Related Factors Among Pregnant Women Referred to Medical and Health Centers of Tehran in 2019: A Cross-sectional Study

Determining Health Literacy Level and Its Related Factors Among Pregnant Women Referred to Medical and Health Centers of Tehran in 2019: A Cross-sectional Study

Safoura Taheri,
Mahmoud Tavousi,
Zohre Momenimovahed,
Ashraf Direkvand-Moghadam,
Nazanin Rezaei,
Nasibeh Sharifi
,et al.

Taheri S, Tavousi M, Momenimovahed Z, Direkvand-Moghadam A, Rezaei N, et al. Determining Health Literacy Level and Its Related Factors Among Pregnant Women Referred to Medical and Health Centers of Tehran in 2019: A Cross-sectional Study. Shiraz E-Med J. 2021;22(10):e109592. doi: https://doi.org/10.5812/semj.109592

17
Jan
2024
Social Determinants of Women's Reproductive Health: A Systematic Review

Social Determinants of Women's Reproductive Health: A Systematic Review

Maryam Biglari Abhari,
Hamideh Sabetrohani,
Samaneh Saghfian Larijani,
Ronak Ghafori,
Ayoub Nafei

Biglari Abhari M, Sabetrohani H, Saghfian Larijani S, Ghafori R, Nafei A. Social Determinants of Women's Reproductive Health: A Systematic Review. Health Scope. 2024;13(1):e140449. doi: https://doi.org/10.5812/healthscope-140449

19
Dec
2023
Social Determinants of Reproductive Age Women's Sexual Health: A Scoping Review

Social Determinants of Reproductive Age Women's Sexual Health: A Scoping Review

Farangis Habibi,
Soghra Khani,
Mohammad Ahmadi

Habibi F, Khani S, Ahmadi M. Social Determinants of Reproductive Age Women's Sexual Health: A Scoping Review. J Nurs Midwifery Sci. 2023;10(4):e140898. doi: https://doi.org/10.5812/jnms-140898

16
Jul
2014
Risky Behaviors and Life Status as Risk Factors for Spontaneous Abortion

Risky Behaviors and Life Status as Risk Factors for Spontaneous Abortion

Seyed Abbas Hosseini,
Masoumeh Farsi Zaban

Hosseini SA, Farsi Zaban M. Risky Behaviors and Life Status as Risk Factors for Spontaneous Abortion. Int J High Risk Behav Addict. 2014;3(4):e17635. doi: https://doi.org/10.5812/ijhrba.17635

More by these authors

Roland Nnaemeka OkoroPubMedScholar
Deborah Oyine AluhPubMedScholar
Chinelo Nneka Aguiyi-IkeanyiPubMedScholar
Share
Cited by
Metrics