
1. Background
Chronic diseases and their associated pain place a substantial burden on individuals, healthcare systems, and societies worldwide (1). Chronic pain is widely recognized as one of the most complex public health challenges, exerting profound effects on physical functioning, psychological well-being, and social participation (2, 3). Given its multifaceted nature, unidimensional approaches are insufficient for comprehensive assessment (4). Accordingly, the biopsychosocial model — which conceptualizes pain as an interaction among biological, psychological, and social determinants — has replaced traditional one-dimensional viewpoints and is now regarded as the gold standard for understanding and managing chronic pain (5, 6).
Among populations affected by chronic pain, veterans constitute a particularly vulnerable group due to the long-term consequences of combat-related injuries and disabilities, compounded by psychological, social, and cultural challenges that shape their pain experiences (7). In Iran, more than 500,000 veterans of the Iran–Iraq war are registered with the Martyrs and Veterans Affairs Foundation (8), and evidence shows that over 80% experience chronic pain across diverse forms such as musculoskeletal, neuropathic, and chemical-injury–related pain. These persistent and often overlapping pain conditions can lead to substantial functional limitations and reduced quality of life (9-12).
Psychological determinants — including pain catastrophizing, anxiety, depression, PTSD, and lower pain self-efficacy — substantially influence pain perception and disability among veterans (13). Social determinants, such as social support, socioeconomic status, family dynamics, and access to healthcare, further contribute to variations in pain intensity and coping (14). Importantly, Iranian veterans are embedded in a unique cultural and religious context in which concepts such as sacrifice, endurance, spiritual coping, and societal expectations regarding pain expression play a defining role in how pain is perceived, reported, and managed (15). Despite the relevance of these cultural factors, limited empirical research has examined how they specifically shape the multidimensional pain experience of Iranian veterans, representing a significant gap in current literature.
Although multidisciplinary and integrative pain management approaches — incorporating pharmacological, non-pharmacological, and psychosocial interventions — are recommended globally for veteran populations (16, 17), access to such comprehensive programs in Iran remains limited. Structured pain self-management interventions, which enhance coping skills and pain management self-efficacy, are not widely implemented despite their demonstrated benefits (18). Moreover, disparities related to socioeconomic status, place of residence, age, and ethnicity influence access to adequate pain care (19, 20). Although participation in multidisciplinary pain management programs is known to improve pain severity, disability, mental health, and quality of life (21), such programs are scarce for Iranian veterans. Additional barriers — including pain underreporting, cultural normalization of suffering, fear of medication side effects, financial constraints, limited awareness, and inadequate access to specialized services — further impede effective pain management (22, 23).
Given these limitations, there is a clear need for studies that investigate the multidimensional aspects of pain within the cultural, psychological, and social context of Iranian veterans. Such research is essential for informing more effective, culturally sensitive, and comprehensive pain management strategies tailored to this population.
2. Objectives
Chronic pain is a complex and multifaceted condition, yet comprehensive investigations into its dimensions and management strategies among veterans remain limited. Given the distinctive geographical, climatic, socioeconomic, and cultural context of Abadan, this study aimed to explore the multidimensional aspects of chronic pain in war veterans and to examine the relationships between pain dimensions, psychosocial factors, and coping strategies.
3. Methods
This descriptive–analytical study was conducted in 2024 among veterans affiliated with the Martyrs and Veterans Affairs Foundation in Abadan, Iran. Although a registry of eligible participants was available, random sampling was not feasible due to administrative and methodological constraints, including confidentiality regulations and the need to verify clinical information through in-person review of medical records. Therefore, convenience sampling was adopted as the most feasible approach to obtain complete and accurate data. While this method may limit generalizability, the use of an adequate sample size and transparent reporting helped reduce selection bias and support internal validity.
The inclusion criteria included having chronic pain, the ability to answer questions, and willingness to participate in the research. The exclusion criteria included the use of medication for sever psychiatric disorders and the misuse of stimulant or narcotic substances. According to the inclusion criteria, 192 veterans with various types of pain, who were identified through the veteran health monitoring system, voluntarily participated in the research. The final sample size of 192 veterans was determined based on both feasibility considerations and reference to prior studies conducted among Iranian veterans with chronic pain. Previous research in similar populations has typically employed sample sizes in the range of 150 - 200 participants, which have been demonstrated to provide sufficient statistical power for correlational and regression analyses (16, 21).
According to established power-analysis principles, approximately 180 participants are required to detect moderate effect sizes (R = 0.25 - 0.30; Cohen’s f2 ≈ 0.06 - 0.10) with 80% power at α = 0.05 in multiple regression models. The inclusion of 192 veterans exceeded this threshold, ensuring adequate statistical power for detecting meaningful associations among pain characteristics, psychosocial variables, and coping strategies. Furthermore, all regression analyses incorporated reporting of effect-size indices (standardized β coefficients and Cohen’s f2 values), allowing readers to evaluate the magnitude and practical significance of the observed effects beyond reliance on P-values alone.
The data collection tools were a demographic questionnaire, the Short-Form McGill Pain Questionnaire (SF-MPQ), the West Haven-Yale Multidimensional Pain Inventory (WHYMPI), and the Coping Strategies Questionnaire (CSQ).
The SF-MPQ was first developed by Melzack in 1971. A revised 22-item version was designed by Dworkin et al. in 2009, covering 4 dimensions: Affective pain, neuropathic pain, continuous pain, and intermittent pain. This scale is scored on a range of 0 to 10. The minimum and the maximum scores are 0 and 220, respectively. This questionnaire does not have reverse scoring, and a higher score indicates more pain. The alpha coefficient for the total scale (SF-MPQ-2) was reported to be 0.95, and the coefficients for its subscales, including affective pain, neuropathic pain, continuous pain, and intermittent pain, were 0.86, 0.83, 0.87, and 0.87, respectively (24). To evaluate and standardize it for the Iranian population, in a study, Khosravi et al. confirmed its content validity and reported its reliability using Cronbach's alpha coefficient as 0.86 (25).
The WHYMPI was developed by Kerns, Turk, and Rudy at West Haven-Yale University in 1985 (26). This 52-item questionnaire has 12 scales across three parts. Part 1 includes questions about pain interference with daily life, support from others, pain severity, life control, and affective distress. Part 2 assesses punitive responses, solicitousness by others, and distraction by others. Part 3 examines household chores, outdoor activities (yard work), activities away from home, and social activities. The value of each question in this questionnaire is graded on a scale of 0 to 6. The validity and reliability of this questionnaire in Iran were examined and reported in different sections by Mirzamani et al. The Cronbach's alpha coefficients for the three parts were calculated as 0.86, 0.78, and 0.75, respectively, and the total Cronbach's alpha was 0.77. The reliability coefficient of this questionnaire using the test-retest method was reported as 0.95 (27).
The CSQ is a 42-item scale developed by Rosenstiel and Keefe to measure six coping strategies, including diverting attention, reinterpreting pain sensations, coping self-statements, ignoring pain sensations, catastrophizing, and praying/hoping (28). Each coping strategy consists of seven phrases. Respondents are asked to read each phrase carefully and indicate the extent to which they use each of the strategies when experiencing pain, on a 7-point Likert scale ranging from “never” to “always”, The scores of the 7 phrases are summed to obtain a composite score for each coping strategy, which can range from 0 to 42. Higher scores on each scale denote a greater use of that strategy in coping with chronic pain. The reliability of this test and its internal consistency coefficients, as measured by Cronbach's alpha, were reported for the main factors as 0.82, 0.77, 0.82, 0.83, 0.80, 0.74, respectively, with a total Cronbach's alpha of 0.926 (29).
Before statistical analysis, all completed questionnaires were reviewed for accuracy and completeness. Questionnaires with more than 10% missing items were excluded from the study to preserve data quality. For cases with minimal item-level missingness, mean substitution within each respective subscale was applied to avoid unnecessary data loss while maintaining consistency across instruments. Sensitivity analyses confirmed that these imputation procedures did not alter variable distribution patterns or affect the results of correlation and regression analyses.
To collect data, the researchers, after obtaining the necessary permissions from Abadan University of Medical Sciences, went to the Martyrs and Veterans Affairs Foundation in Abadan, Iran, to sample veterans. Data collection was conducted during clinic visits and was based on a review of medical records and documented evidence contained in the veterans’ files. All questionnaires were completed under the supervision of trained interviewers who followed standardized instructions to ensure consistency. Clarifications were provided only when necessary, allowing participants to respond independently. This approach maintained high data quality and minimized any potential influence of the interviewers on participants’ responses.
Afterward, the collected data were analyzed using SPSS software version 26. For descriptive analysis, frequency percentages, means, and standard deviations were calculated. Pearson’s correlation coefficient was employed to examine the relationships among the questionnaires’ dimensions, and the Kolmogorov-Smirnov test was utilized to check the normality of the data.
3.1. Ethical Considerations
Ethical safeguards were incorporated throughout the research process. The study protocol was reviewed and approved by the Ethics Committee of Abadan University of Medical Sciences. Participation was entirely voluntary, and written informed consent was obtained after participants received comprehensive information about the study objectives, confidentiality protections, and their right to withdraw at any stage without penalty. To preserve confidentiality, all data were anonymized, securely stored, and accessible only to authorized members of the research team. To minimize the potential for psychological distress, data collection was carried out by trained interviewers with prior experience working with veteran populations. These procedures ensured adherence to internationally recognized ethical standards for conducting research with potentially vulnerable groups.
4. Results
A total of 192 veterans were examined in this study. The participants’ mean age was 57.9 ± 4.5 years, with the highest age distribution observed in the 61 - 70 years age group. The majority of participants in this study were male (95.3%) and married (92.2%). The longest pain duration was reported to be over 30 years (50.0%), and the most common type of disability was physical (69.3%). Table 1 presents the veterans’ demographic characteristics.
Table 1.
Demographic and Disability Characteristics of Veterans Participating in the Study Categorization Frequency (Percentage)
| Variables | No. (%) |
|---|---|
| Age (y) | |
| 54 - 60 | 52 (27.1) |
| 61 - 70 | 80 (41.7) |
| > 70 | 60 (31.2) |
| Gender | |
| Male | 183 (95.3) |
| Female | 9 (4.7) |
| Marital status | |
| Married | 177 (92.2) |
| Single/divorced | 15 (7.8) |
| Pain duration (y) | |
| < 20 | 37 (19.3) |
| 20 - 30 | 59 (30.7) |
| > 30 | 96 (50.0) |
| Type of disability | |
| Physical | 133 (69.3) |
| Psychological | 37 (19.3) |
| Combined | 22 (11.4) |
The findings of the present study revealed that patients with pain achieved a mean total score of 105.3 ± 23.4 on the SF-MPQ, indicating relatively severe pain across various dimensions. In the psychological evaluation using the WHYMPI, the mean score for the psychological dimensions of pain was reported as 3.3 ± 1.1, with the highest scores belonging to pain severity (3.9 ± 1.0) and pain interference with daily life (3.5 ± 1.1). The findings related to others’ responses were predominantly solicitousness by others (2.6 ± 1.1) and distraction by others (2.3 ± 1.0), while negative responses were at a lower level (2.0 ± 1.0), indicating the presence of relative support for the patients. The daily activities dimension, with a total mean score of 2.9 ± 1.2, showed that these activities were affected by pain and had a significant decrease, particularly in the areas of social activities (2.3 ± 1.1) and outdoor activities (2.7 ± 1.2). Additionally, on the CSQ, diverting attention (22.5 ± 7.0) and praying/hoping (20.3 ± 7.1) strategies were reported as the most frequently used coping methods. The total pain management score (111.2 ± 27.8) also suggested that patients employed a diverse set of individual strategies to cope with their pain. Table 2 presents the scores for pain management dimensions and strategies among veterans.
Table 2.
Scores for Pain Management Dimensions and Strategies Among Veterans
| Questionnaire and Part/Subscale | Number of Questions | Score Range | Mean ± SD |
|---|---|---|---|
| SF-MPQ | |||
| Affective pain | 6 | 6 - 60 | 31.2 ± 8.5 |
| Neuropathic pain | 5 | 5 - 50 | 24.8 ± 7.8 |
| Continuous pain | 6 | 6 - 60 | 26.7 ± 8.2 |
| Intermittent pain | 5 | 5 - 50 | 21.9 ± 6.9 |
| Total scale | 22 | 22 - 220 | 105.3 ± 23.4 |
| WHYMPI | |||
| Part 1: Psychological dimensions of pain (20 questions) | |||
| Interference with daily life | 9 | 0 - 6 | 3.5 ± 1.1 |
| Support from others | 3 | 0 - 6 | 3.0 ± 1.1 |
| Pain severity | 3 | 0 - 6 | 3.9 ± 1.0 |
| Life control | 2 | 0 - 6 | 3.1 ± 1.2 |
| Affective distress | 3 | 0 - 6 | 3.4 ± 1.1 |
| Total mean score of Part 1 | 20 | 0 - 6 | 3.3 ± 1.1 |
| Part 2: Others’ responses (14 questions) | |||
| Negative responses | 4 | 0 - 6 | 2.0 ± 1.0 |
| Solicitousness by others | 6 | 0 - 6 | 2.6 ± 1.1 |
| Distraction by others | 4 | 0 - 6 | 2.3 ± 1.0 |
| Total mean score of part 2 | 14 | 0 - 6 | 2.3 ± 1.0 |
| Part 3: Daily activities (18 questions) | |||
| Household chores | 5 | 0 - 6 | 3.4 ± 1.3 |
| Outdoor activities | 5 | 0 - 6 | 3.0 ± 1.4 |
| Activities away from home | 4 | 0 - 6 | 2.7 ± 1.2 |
| Social activities | 4 | 0 - 6 | 2.3 ± 1.1 |
| Total mean score of part 3 | 18 | 0 - 6 | 2.9 ± 1.2 |
| CSQ | |||
| Diverting attention | 7 | 0 - 42 | 22.5 ± 7.0 |
| Reinterpreting pain sensations | 7 | 0 - 42 | 19.5 ± 6.6 |
| Coping self-statements | 7 | 0 - 42 | 17.8 ± 6.0 |
| Ignoring pain sensations | 7 | 0 - 42 | 14.6 ± 5.8 |
| Catastrophizing | 7 | 0 - 42 | 16.5 ± 6.5 |
| Praying/hoping | 7 | 0 - 42 | 20.3 ± 7.1 |
| Total score of the scale | 42 | 0 - 252 | 111.2 ± 27.8 |
Abbreviations: SF-MPQ, Short-Form McGill Pain Questionnaire; WHYMPI, West Haven-Yale Multidimensional Pain Inventory; CSQ, Coping Strategies Questionnaire.
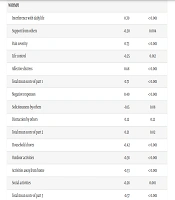
Pearson’s correlation analysis indicated that the SF-MPQ total score was positively correlated with all SF-MPQ subscales (P < 0.001). Among the WHYMPI subscales, pain severity (R = 0.73, P < 0.001), pain interference with daily life (R = 0.70, P < 0.001), and affective distress (R = 0.68, P < 0.001) showed strong positive correlations with the SF-MPQ total score. Conversely, support from others (R = -0.30, P = 0.004) and life control (R = -0.25, P = 0.012) demonstrated significant negative correlations with the SF-MPQ total score, such that higher scores on these subscales were associated with lower total pain scores. It should be noted that while ‘Support from others’ was significant in bivariate correlation (Table 3), its effect was slightly attenuated in multivariate regression (Table 4) due to adjustment for other association.
Table 3.
The Correlations of Pearson’s Correlation Coefficients for the Subscales of the Short-Form McGill Pain Questionnaire, the West Haven-Yale Multidimensional Pain Inventory, and the Coping Strategies Questionnaire with the Short-Form McGill Pain Questionnaire Total Score
| Variables and Part/Subscale | R | P-Value |
|---|---|---|
| SF-MPQ | ||
| Affective pain | 0.88 | < 0.001 |
| Neuropathic pain | 0.85 | < 0.001 |
| Continuous pain | 0.90 | < 0.001 |
| Intermittent pain | 0.82 | < 0.001 |
| Total scale | 1 | - |
| WHYMPI | ||
| Interference with daily life | 0.70 | < 0.001 |
| Support from others | -0.30 | 0.004 |
| Pain severity | 0.73 | < 0.001 |
| Life control | -0.25 | 0.012 |
| Affective distress | 0.68 | < 0.001 |
| Total mean score of part 1 | 0.71 | < 0.001 |
| Negative responses | 0.40 | < 0.001 |
| Solicitousness by others | -0.15 | 0.08 |
| Distraction by others | 0.12 | 0.12 |
| Total mean score of part 2 | 0.21 | 0.02 |
| Household chores | -0.42 | < 0.001 |
| Outdoor activities | -0.38 | < 0.001 |
| Activities away from home | -0.33 | < 0.001 |
| Social activities | -0.28 | 0.001 |
| Total mean score of part 3 | -0.37 | < 0.001 |
| CSQ | ||
| Diverting attention | -0.18 | 0.05 |
| Reinterpreting pain sensations | -0.21 | 0.03 |
| Coping self-statements | -0.15 | 0.08 |
| Ignoring pain sensations | -0.10 | 0.18 |
| Catastrophizing | 0.50 | < 0.001 |
| Praying/hoping | -0.05 | 0.60 |
| Total score of the scale | 0.02 | 0.80 |
Abbreviations: SF-MPQ, Short-Form McGill Pain Questionnaire; WHYMPI, West Haven-Yale Multidimensional Pain Inventory; CSQ, Coping Strategies Questionnaire.
Table 4.
The Multivariate Regression Analysis Results Regarding the Effect of the Short-Form McGill Pain Questionnaire Total Score on the Subscales of the West Haven-Yale Multidimensional Pain Inventory and the Coping Strategies Questionnaire a
| Variables and Part/Subscale | B (Unstandardized Coefficient) | β (Standardized Coefficient) | 95% CI for B | P-Value | R² | Interpretation |
|---|---|---|---|---|---|---|
| WHYMPI-part 1 (psychological dimensions of pain) | ||||||
| Interference with daily life | 0.54 | 0.55 | 0.32 to 0.76 | < 0.001 | 0.29 | Strong positive relationship |
| Support from others | -0.19 | -0.21 | -0.37 to -0.01 | 0.05 | 0.05 | Weak negative relationship |
| Pain severity | 0.62 | 0.58 | 0.41 to 0.83 | < 0.001 | 0.34 | Strongest predictor |
| Life control | -0.28 | -0.27 | -0.47 to -0.09 | 0.01 | 0.09 | Negative association |
| Affective distress | 0.49 | 0.48 | 0.26 to 0.72 | < 0.001 | 0.23 | Positive relationship |
| WHYMPI-part 2 (others’ responses) | ||||||
| Negative responses | 0.36 | 0.31 | 0.12 to 0.60 | 0.004 | 0.08 | Positive association |
| Solicitousness by others | -0.14 | -0.12 | -0.34 to 0.06 | 0.14 | 0.03 | Non-significant |
| Distraction by others | 0.22 | 0.19 | 0.01 to 0.43 | 0.04 | 0.06 | Weak positive relationship |
| WHYMPI-part 3 (daily activities) | ||||||
| Household chores | -0.43 | -0.38 | -0.63 to -0.23 | 0.001 | 0.11 | Pain reduces activities |
| Outdoor activities | -0.38 | -0.34 | -0.57 to -0.19 | 0.003 | 0.09 | Significant negative relationship |
| Activities away from home | -0.34 | -0.29 | -0.54 to -0.14 | 0.007 | 0.07 | Decreased activities |
| Social activities | -0.29 | -0.25 | -0.53 to -0.05 | 0.02 | 0.05 | Reduced social engagement |
| CSQ (coping strategies) | ||||||
| Diverting attention | 0.31 | 0.27 | 0.08 to 0.54 | 0.01 | 0.08 | Increased use with pain |
| Reinterpreting pain sensations | -0.20 | -0.18 | -0.42 to 0.02 | 0.08 | 0.04 | Negative trend, ns |
| Coping self-statements | 0.12 | 0.10 | -0.09 to 0.33 | 0.27 | 0.01 | Non-significant |
| Ignoring pain sensations | -0.08 | -0.07 | -0.26 to 0.10 | 0.39 | 0.005 | Non-significant |
| Catastrophizing | 0.18 | 0.16 | -0.03 to 0.39 | 0.09 | 0.03 | Positive trend |
| Praying/hoping | 0.28 | 0.24 | 0.06 to 0.50 | 0.02 | 0.06 | Positive association |
| Total score of CSQ | 0.33 | 0.30 | 0.08 to 0.58 | 0.009 | 0.09 | Overall positive |
Abbreviations: SF-MPQ, Short-Form McGill Pain Questionnaire; WHYMPI, West Haven-Yale Multidimensional Pain Inventory; CSQ, Coping Strategies Questionnaire; ns, non-significant.
a Dependent variable: SF-MPQ total score; independent variables: Subscales of WHYMPI and CSQ.
In the others’ response’s part, negative responses (R = 0.40, P < 0.001) were positively correlated with the SF-MPQ total score. Daily activities also showed a significant negative correlation with the SF-MPQ total score, such that as pain increased, household chores (R = -0.42, P < 0.001), outdoor activities (R = -0.38, P < 0.001), and social activities (R = -0.28, P = 0.001) all decreased.
Moreover, a correlation analysis revealed a significant negative correlation between the reinterpreting pain sensations strategy and the SF-MPQ total score (R = -0.21, P = 0.03), while the diverting attention strategy showed significant correlation (R = -0.18, P = 0.05). In contrast, catastrophizing showed the highest positive correlation (R = 0.50, P < 0.001). In contrast, praying/hoping showed no significant correlation with the SF-MPQ total score (R = -0.05, P = 0.60), indicating that this strategy was not associated with pain intensity in the present sample (Table 3).
These results indicate that pain severity in veterans is associated with psychological and social factors, as well as with patients’ coping strategies. The use of positive coping strategies (e.g., reinterpreting pain) was associated with lower pain severity, whereas negative strategies such as catastrophizing were associated with higher pain severity and greater psychological burden. Table 3 shows the correlations of Pearson’s correlation coefficients (R) and significance levels (P) for the subscales of the used questionnaires with the SF-MPQ total score.
Findings from a multiple regression analysis demonstrated that the SF-MPQ total score was significantly associated with all subscales in Part 1 of the WHYMPI (psychological dimensions of pain) (P < 0.01). In Part 2 of the WHYMPI (others’ responses), pain severity showed significant associations with negative responses, solicitousness by others, and distraction by others (P < 0.05). In Part 3 of the WHYMPI (daily activities), all subscales were influenced by the SF-MPQ total score (P < 0.05). Additionally, all subscales of the CSQ were significantly correlated with the total pain score (P < 0.01). These findings suggest that the patients’ total pain score is a significant association of their psychological status, social interactions, daily activities, and pain coping strategies. The details of the multivariate regression analysis results regarding the effect of the SF-MPQ total score on the subscales of the WHYMPI and the CSQ are reported in Table 4.
5. Discussion
The present study provides empirical evidence on the multidimensional characteristics of chronic pain among Iranian veterans by examining its associations with demographic factors, pain dimensions, psychosocial functioning, and coping strategies. Rather than reiterating established theoretical models, the findings extend existing knowledge by demonstrating how long-standing pain in this population is concurrently related to functional impairment, affective distress, and specific coping patterns.
The demographic profile of the sample, with a mean age of 57.9 ± 4.5 years and a predominance of male participants, reflects an aging veteran population with prolonged exposure to combat-related injuries. The high proportion of individuals reporting pain duration exceeding 30 years highlights the persistent nature of war-related pain, consistent with prior international evidence documenting the long-term neurophysiological and psychosocial consequences of trauma (30-33). These findings add to the literature by quantifying the chronicity of pain within this specific veteran cohort.
Results from the SF-MPQ demonstrated elevated scores across affective, neuropathic, continuous, and intermittent pain dimensions, supporting the conceptualization of pain as a multidimensional experience. Importantly, the present findings empirically document the coexistence of multiple pain modalities within individuals, aligning with the multidimensional framework proposed by the International Association for the Study of Pain (IASP), without restating its theoretical foundations (34-36).
Within the WHYMPI domains, pain severity and interference with daily life exhibited the strongest associations with overall pain scores, accompanied by elevated affective distress. These results highlight the close linkage between pain intensity and functional disruption in veterans and are consistent with previous reports demonstrating associations between chronic pain, emotional distress, and reduced quality of life in this population (37, 38). However, given the cross-sectional design, it is equally plausible that psychological distress contributes to heightened pain perception, underscoring the potential for bidirectional relationships between these variables.
Regarding social functioning, higher levels of solicitous responses from others were observed alongside reduced engagement in outdoor and social activities. While perceived support was measured directly, interpretations regarding its buffering role should be made cautiously. The data indicate co-occurrence rather than protective effects, suggesting that social support and activity limitation may simultaneously characterize the lived experience of chronic pain in veterans, as reported in earlier studies (39, 40).
Coping strategy patterns revealed that diverting attention and praying/hoping were the most frequently reported strategies, whereas catastrophizing showed a strong positive association with pain severity. However, praying/hoping showed no significant association with pain intensity, suggesting that while it was frequently used, it did not correlate with pain levels in this sample. These findings are strictly based on measured CSQ subscales and do not imply causal effects.
These findings are strictly based on measured CSQ subscales and indicate differential associations between coping styles and pain outcomes. Although prior research has linked catastrophizing to increased pain and distress (41), the present results do not imply causality. It remains possible that higher pain intensity predisposes individuals to greater reliance on maladaptive coping strategies, an issue that warrants longitudinal investigation.
Finally, the observed associations across pain severity, psychological distress, social interaction, and daily functioning reinforce the interrelated nature of these domains within the biopsychosocial framework of chronic pain (42). Nevertheless, the cross-sectional design precludes causal inference, and reverse causality cannot be ruled out. Future longitudinal and interventional studies are necessary to clarify temporal relationships and to determine whether modifying psychosocial or coping-related factors leads to meaningful changes in pain outcomes, as suggested by prior research (40).
5.1. Limitations
Although this study offers valuable insights into the multidimensional nature of pain in veterans, its cross-sectional design limits causal interpretation, and the use of convenience sampling from a single city may reduce generalizability. Additionally, reliance on self-reported questionnaires may have introduced recall or social desirability bias. Future longitudinal and multi-center studies with more rigorous and mixed-method designs are recommended to validate these findings.
5.2. Conclusions
This study advances understanding of the multidimensional nature of chronic pain in veterans, showing how pain severity is closely intertwined with psychological distress, social functioning, and coping strategies. The findings indicate that pain severity in this population is not limited to physical symptoms but is concurrently related to daily activities, emotional states, and social interactions. Although these results do not establish causal relationships or intervention effects, they underscore the relevance of considering medical, psychological, and social dimensions when assessing chronic pain in veterans. While methodological constraints call for cautious interpretation, the insights gained provide a strong foundation for future inquiry. Future research should include interventional trials as well as longitudinal and multi-center studies that employ rigorous sampling strategies and mixed-methods designs. Such approaches are essential to build upon the current findings and to develop targeted, evidence-based interventions.