2. Objectives
The present study reviewed our experience with HDR brachytherapy with cobalt 60 (Co-60) remote after loading system to evaluate treatment outcome treated cervical cancer patients between 2008 and 2015 after EBRT, to identify prognostic factors for 3-year OS, 3-year DFS and incidence of acute and late gastrointestinal and genitourinary complications.
3. Patients and Methods
This was a cross sectional-analytic study that data obtained from patient medical records. Staging of cancer cervix was performed based on the international federation of gynecology and obstetrics (FIGO) criteria in our center or other centers.
A total of 154 patients who diagnosed with histopathologically confirmed carcinoma of cervix, followed by the radiation-oncology ward of Shohada-e-Tajrish hospital in Tehran, Iran between February 2008 and March 2015. They were completed their scheduled EBRT + HDR ICRT with Co-60 remote after loading system treatment radiotherapy. They were analyzed for 3-year DFS (residual disease, local recurrence, and distant metastases), 3-year OS and incidence of acute and late treatment complications for HDR-ICRT.
All the patients were treated initially with external beam irradiation in our center or other centers with total dose 45 Gy-54 Gy with or without concomitant chemotherapy. After completion of EBRT all Patients were planned for brachytherapy within 1 to 3 weeks and more due to the great number of patients with three to five fractions of HDR brachytherapy for each patient with a week’s interval.
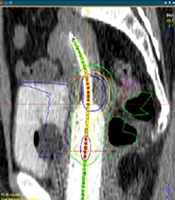
We used Co-60 HDR after-loading system for intracavitary radiotherapy with one tandem and two ovoid applicators based on the Manchester System. There were three different sizes of tandems and ovoids based on the length of uterus and expansion of the vaginal wall. We performed meticulous vaginal packing with betadine gauze packs to get away the bladder and rectum from the applicators. In brachytherapy room, tumor regression was evaluated and endocervical canal was dilated by a radiation oncologist with assistance of two nurses.
All the tandem and ovoids insertions, X-ray images, and treatments were done in a standard brachytherapy room with X-ray equipment by a radiation oncologist and two well trained nurses.
Treatment planning was done by a radiation oncologist and a medical radiation physicist for the treatment planning system.
The brachytherapy dose was calculated based on EQD 2Gy + EQD HDR = Total dose to point A (80 - 90 Gy) and delivered to the point A. The treatment overall time was between 20 to 40 minutes.
After the completion of treatment, all 154 patients were followed by the radiation-oncology ward of Shohada-e-Tajrish hospital between February 2008 and March 2015 with standard guide lines every 3 months for the first 2 years, every 6 months for the next 3 years and annually afterward.
During each follow up, clinical examination was done by a radiation oncologist in each appointment and cervical cytology was taken by a gynecologic oncologist at the first follow-up and annually afterward. Paraclinic examination such as blood test, X-ray, ultrasonography, bone scan, CT scan and MRI were used based on the patients complains and suspected examination findings to rule out any locoregional and distant metastasis. All local recurrences disease was histologically confirmed. Recurrences were defined as distant if they occurred in the Para-aortic lymph nodes or outside the pelvis. Patients with rectal or bladder complications were evaluated by the common toxicity criteria by radiation therapy oncology group (RTOG). Patients considered lost to follow up who did not visit after any appointments. 22 patients were excluded from the study because of they did not complete our standard follow up protocol.
Patients without any locoregional recurrence or distant metastases until the last follow up were considered as disease free. Follow-up time was defined by the interval between the last day of HDR ICRT and the last information about the patient. The follow up duration was between 6 - 60 months. 3-year DFS rates were calculated from date of the last day of HDR ICRT until the date of first recurrence or progression or distant metastases. 3-year OS rates were calculated from date of the last day of HDR ICRT until the date of death.
The ethical regulations dictated in the act provided by Shahid Beheshti University of Medical Sciences (reference number of research ethics committee: 400) were strictly observed. The data were strictly preserved without using the patient`s names.
The examination of three-year DFS and the three-year OS by univariable analyses was performed by log rank test. For multivariate analysis, the Cox proportional hazards model was used to assess the strengths of various histo-clinical and treatment factors with three-year DFS and the three-year OS. The statistical analyses were performed by using software SPSS version 21 (SPSS IBM).
4. Results
154 patients were the subjects for our study. The follow up duration was between 6 - 60 months with a median of 38 months. Their median age was 57.4 years (range, 33 to 86 years). Fourteen patients (9.1 %) were in stage I (FIGO classification), 8 (5.2%) were in stage IIA, 26 (16.9%) were in stage IIB, 100 (64.9%) were in stage III, and 6 (3.9 %) were in stage IVA. 102 patients (66.2 %) had tumor size ≥ 4 cm. 137 patients (89%) had squamous cell carcinoma and 13 patients (8.4%) had adenocarcinoma in their final histology reports. 132 patients (85.7%) received concomitant chemotherapy with EBRT. 19 patients (12.3%) was detected during the follow up with distant metastasis, which consistent of lung 6, bone 4, liver 3, Para-aortic lymph node 6, Supraclavicular lymph node and Para-aortic lymph node 2. 44 patients (28.6%) were diagnosed with pelvic lymph node involvement based on imaging studies. The median total dose of EBRT was 50 Gy (range, 45 to 54 Gy), median total dose of BT was 20 Gy (range, 16 to 24 Gy) and median total dose to the point A was 80 Gy (range, 70 to 90 Gy).The mean fractions number of BT was 4 fractions (range, 3 to 5 fractions) and the median gap between EBRT and HDR ICRT was 2 weeks (range, 1 to 5 weeks). Table 1 shows patient, tumor characteristics and treatment factors of 154 adult patients included in this study.
Table 1.
| Factors | Total (n = 154) |
|---|---|
| 57.4 (33 - 86) | |
| I | 14 (9.1) |
| IIA | 8 (5.2) |
| IIB | 26 (16.9) |
| III | 100 (64.9) |
| IVA | 6 (3.9) |
| Tumor size ≥ 4 | 102 (66.2) |
| Tumor size < 4 | 52 (33.8) |
| Squamous cell carcinoma | 137 (89) |
| Adenocarcinoma | 13 (8.4) |
| Adenosquamous carcinoma | 4 (2.6) |
| None | 102 (66.2) |
| Pelvic alone | 44 (28.6) |
| Pelvic and para-aortic | 8 (5.2) |
| 50 (45 - 54) | |
| Yes | 132 (85.7) |
| No | 22 (14.3) |
| 20 (16 - 24) | |
| 80 (70 - 90) | |
| 4 (3 - 5) | |
| 2 (1 - 3) | |
| 38 (6 - 60) |
a Abbreviations: BT, brachytherapy; EBRT, external beam radiotherapy; FIGO, international federation of gynecology and obstetrics; HDR ICRT, high dose rate intracavitary radiotherapy.
b Data are presented as median (range) or No. (%).
Acute and late gastrointestinal (rectal) and genitourinary (bladder) complications based on RTOG criteria were seen 6.5%, 3.9% and 16.2%, 7.1% respectively. Overall rectal and bladder complications were seen in 16 (10.4%) and 36 (23.3 %) patients. No patients died of any irradiated-related causes (grade 5).
Four patients experienced grade 1 and grade 2 acute radiation proctitis and six patients had grade 3 acute proctitis. One patient had grade 1 and grade 2 late radiation proctitis and six experienced grade 3 late proctitis. There was no patient in grade 4 acute and chronic radiation proctitis. Twenty patients experienced grade 1 and 2 acute radiation cystitis, four patients experienced grade 3 acute cystitis and one patient had grade 4 acute cystitis.
Two patients experienced grade 1 and grade 2 late genitourinary toxicities, eight patients experienced grade 3 late genitourinary toxicities and one patient had grade 4. The most common acute and late gastrointestinal (rectal) and genitourinary (bladder) toxicities were in stage III patients. Table 2 shows acute and late toxicities based on RTOG criteria and stage of tumor in patients.
Table 2.
Gastrointestinal and Genitourinary Complications Based on RTOG Criteria and Stage of Tumor in Patients a
| I | 14 | 0 | 0 | 0 | 14 (9.1) | 14 | 0 | 0 | 0 | 14 (9.1) |
| IIA | 7 | 1 | 0 | 0 | 8 (5.2) | 8 | 0 | 0 | 0 | 8 (5.2) |
| IIB | 24 | 1 | 1 | 0 | 26 (16.9) | 24 | 0 | 2 | 0 | 26 (16.9) |
| III | 94 | 2 | 4 | 0 | 100 (64.9) | 96 | 1 | 3 | 0 | 100 (64.9) |
| IVA | 5 | 0 | 1 | 0 | 6 (3.9) | 6 | 0 | 0 | 0 | 6 (3.9) |
| Total | 144 | 4 | 6 | 0 | 154 (100) | 148 | 1 | 5 | 0 | 154 (100) |
| I | 14 | 0 | 0 | 0 | 14 (9.1) | 14 | 0 | 0 | 0 | 14 (9.1) |
| IIA | 7 | 1 | 0 | 0 | 8 (5.2) | 8 | 0 | 0 | 0 | 8 (5.2) |
| IIB | 24 | 4 | 1 | 0 | 26 (16.9) | 24 | 0 | 2 | 0 | 26 (16.9) |
| III | 94 | 14 | 3 | 1 | 100 (64.9) | 92 | 2 | 5 | 1 | 100 (64.9) |
| IVA | 5 | 1 | 0 | 0 | 6 (3.9) | 5 | 0 | 1 | 0 | 6 (3.9) |
| Total | 129 | 20 | 4 | 1 | 154 (100) | 143 | 2 | 8 | 1 | 154 (100) |
a Abbreviation: G: grade.
Overall, 22 (14.28 %) patients were excluded because of lost to follow up after completion of EBRT and HDR ICRT (1patient in stage I, 5 patients in stage II, 14 patients in stage III and 2 patients In stage IVA) and 78 (50.64 %) patients were disease free (12 patients were in stage I, 24 patients were in stage II, 41 patients were in stage III and only 1 patient was in stage IVA). The median follow-up period was 38 months overall, and 36 months for patients who did not die of their cervical cancer.
The 3 year DFS rate was 85.7%, 70.7 %, 41% and 16.6% for stages I, II, III, IVA respectively.
According to Kaplan-Meier 3-year DFS analysis and Log-rank test in univariate analysis and Cox regression model in multivariate analysis, four factors were statistically significant relation between 3-year DFS and early stage (P = 0.001, Odd Ratio (OR) = 2.31, 95% CI = 1.13 - 4.52), tumor size ≥ 4 cm (after adjusting for the residual disease after radiation) (P = 0.012, OR = 2.19, 95% CI = 1.01 - 4.40), pelvic lymph node involvement (P = 0.005, OR = 2.25, 95% CI = 1.07 - 4.46) and 1 week Gap between EBRT and HDR ICRT (P = 0.005, OR = 1.74, 95% CI = 0.99 - 2.96) (Table 3). Then, the favorable prognostic factors in our study in univariate and multivariate analysis were: early stage, tumor size < 4 cm, no pelvic lymph node involvement and 1 week Gap between EBRT and HDR ICRT. There was no statistically significant relationship between 3-year DFS and histology tumor (after adjusting for the residual disease after radiation) and mean total dose to the point A by univariate and multivariate analysis (Table 3).
Table 3.
Three-year Disease Free Mean Survival Rate According to Univariate and Multivariate Analysis (After Adjusting for the Residual Disease After Radiation for the Histology and Tumor Size a
| Factor | No. of Patients | Three-Year DFS | Univariate Analysis P Value | Odd Ratio | 95% CI | Multivariate Analysis P Value |
|---|---|---|---|---|---|---|
| 0.03 | 2.31 | 1.13 - 4.52 | 0.001 | |||
| I + IIA + IIB (early stage) | 48 | 36 (75) | ||||
| III + IVA (locally advanced stage) | 106 | 42 (39.62) | ||||
| 0.11 | 1.52 | 0.68 - 3.49 | 0.32 | |||
| Squamous cell carcinoma | 137 | 65 (60.58) | ||||
| Adenocarcinoma | 13 | 6 (69.23) | ||||
| Adenosquamous carcinoma | 4 | 2 (50) | ||||
| 0.04 | 2.19 | 1.01 - 4.40 | 0.005 | |||
| ≥ 4 | 102 | 37 (52.85) | ||||
| < 4 | 52 | 34 (77.27) | ||||
| 0.03 | 2.25 | 1.07 - 4.46 | 0.005 | |||
| No | 102 | 66 (64.7) | ||||
| Yes | 52 | 15 (28.8) | ||||
| 0.009 | 1.74 | 0.99 - 2.96 | 0.005 | |||
| 1 | 95 | 69 (72.63) | ||||
| ≥ 3 | 59 | 29 (49.15) | ||||
| 0.082 | 1.18 | 0.79 - 1.75 | 0.099 | |||
| < 80 | 80 | 44 (55) | ||||
| ≥ 80 | 74 | 31 (41.9) |
a Abbreviations: DFS, disease free mean survival; EBRT, external beam radiotherapy; HDR ICRT, high dose rate intracavitary radiotherapy.
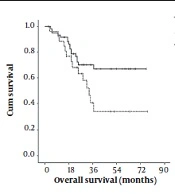
The 3 year OS rate was 85.7%, 76.4%, 42%, and 33.3% for stages I, II, III, and IVA, respectively.
According to Kaplan-Meier 3-year OS analysis and Log-rank test in univariate analysis and Cox regression model in multivariate analysis, four factors were statistically significant relation between 3-year OS and early stage (P = 0.001, OR = 2.52, 95% CI = 1.34 -4.72), tumor size ≥ 4 cm (P = 0.002, OR = 2.32, 95% CI = 1.22 - 4.55), pelvic lymph node involvement (P = 0.002, OR = 2.5 5, 95% CI = 1.13 - 4.48), 1 week Gap between EBRT and HDR ICRT (P = 0.002, OR = 2.04, 95% CI = 1.29 - 3.26) and distant metastasis (during the follow up) (P = 0.001, OR = 8.25, 95% CI = 3.13 - 25.2), (Table 4). Then the favorable prognostic factors in our study in univariate and multivariate analysis were: early stage, tumor size < 4 cm, no pelvic lymph node involvement, 1 week Gap between EBRT and HDR ICRT and no distant metastasis. There was no statistically significant relationship between 3-year OS and histology tumor and mean total dose to the point A by univariate and multivariate analysis (Table 4).
Table 4.
Three-Year Mean Overall Survival Rate According to Univariate and Multivariate Analysis a
| Factor | No. of Patients | Three-Year OS | Univariate Analysis P Value | Odd Ratio | 95% CI | Multivariate Analysis P Value |
|---|---|---|---|---|---|---|
| 0.02 | 2.52 | 1.34 - 4.72 | 0.001 | |||
| I + IIA + IIB (early stage) | 48 | 38 (80.95) | ||||
| III + IVA (locally advanced stage) | 106 | 44 (41.50) | ||||
| 0.17 | 1.3 2 | 0.68 - 3.49 | 0.41 | |||
| Squamous cell carcinoma | 137 | 91 (66.42) | ||||
| Adenocarcinoma | 13 | 10 (76.92) | ||||
| Adenosquamous carcinoma | 4 | 2 (50) | ||||
| 0.02 | 2.32 | 1.22 - 4.55 | 0.002 | |||
| ≥ 4 | 102 | 41 (40.2) | ||||
| < 4 | 52 | 42 (80.76) | ||||
| 0.02 | 2.55 | 1.13 - 4.48 | 0.002 | |||
| No | 102 | 72 (70.58) | ||||
| Yes | 52 | 18 (34.6) | ||||
| 0.001 | 8.25 | 3.13 - 25.2 | 0.001 | |||
| No | 135 | 85 (62.96) | ||||
| Yes | 19 | 2 (10.52) | ||||
| 0.005 | 2.04 | 1.29 - 3.26 | 0.002 | |||
| 1 | 95 | 72 (75.78) | ||||
| 3 ≥ | 59 | 32 (54.23) | ||||
| 0.092 | 1.08 | 0.68 - 1.64 | 0.11 | |||
| < 80 | 80 | 48 (60) | ||||
| ≥ 80 | 74 | 35 (47.3) |
a Abbreviations: EBRT, external beam radiotherapy; HDR ICRT, high dose rate intracavitary radiotherapy; OS, overall survival.
5. Discussion
EBRT with brachytherapy is the standard treatment modality of most stages of carcinoma cervix (6, 7). American Brachytherapy Society (ABS) recommends multiple HDR ICRT insertions, allowing tumor volume decreases daily (8). HDR ICRT has been used for more than 40 years in Iran. Our findings were consistent with the most studies that showed similar DFS and OS.
In 2010, Azad and Choudhary (9) showed that 342 patients who had been treated by EBRT and HDR brachytherapy, reported three year disease free survival rate for stages I, II, III, and IV, were 81.8%, 70.7%, 40.08%, and 11.76% respectively. The disease free survival rate for early stage (I and II) was 72.04% and 37.75% for locally advanced stage (III and IVA).
Likewise in our study, that t 3-year DFS was 85.7%, 70.7 %, 41% and 16.6% for stages I, II, III, IVA respectively. The DFS rate was 75% and 39.62% for early stage and locally advanced stage (P = 0.001).
Azad and Choudhary (9) also demonstrated that early stage and overall treatment time were prognostic factors that affect the 3 years DFS and 3 years OS with P value of 0.0001. We also showed that, early stage, tumor size less than 4 cm, no pelvic lymph node involvement and 1 week Gap between EBRT and HDR ICRT were favorable prognostic factors for 3 year DFS by both univariate and multivariate analysis.
Lorvidhaya et al. (10) showed the five-year overall survival rate for Stage IB, IIA, IIB, IIIA, IIIB, IVA, and IVB were 86.3%, 81.1%, 73.0%, 50.3%, 47.8%, 7.8%, and 30.8% respectively. But they did not report any prognostic factors which affect the 5-year OS.
This finding was partly matched with our study that showed three year OS was 85.7%, 76.4%, 42%, and 33.3% for stages I, II, III, and IVA, respectively. In our study, three year OS was 80.95% for early stage and 41.5% for locally advanced stage disease (P = 0.001).
But we also showed that, early stage, tumor size < 4 cm, no pelvic lymph node involvement and 1 week Gap between EBRT and HDR ICRT were favorable prognostic factors for 3 year OS by both univariate and multivariate analysis.
Our three year DFS and three year OS were comparable with those in previous reports of brachytherapy in the literature. Factors may affect to this result include high proportional total dose to the point A and physical advantages of HDR brachytherapy compared with LDR and MDR brachytherapy (11-14).
Our study also showed a significant relationship between tumor size (after adjusting for the residual disease after radiation) and pelvic lymph node involvement with the 3 year DFS and 3 year OS with P = 0.005 and P = 0.002 respectively. This result was comparable with Kodaira and colleagues’ findings that demonstrated tumor size and lymph node involvement were prognostic factors. But all patients in that study had stage II cervival cancer (15).
In our study all patients were irradiated with HDR ICRT after EBRT. Therefore, the overall treatment time was increased with the adverse effects. Our study also showed a significant relationship between 1 week Gap between EBRT and HDR ICRT versus 3 ≥ weeks Gap between EBRT and HDR ICRT (overall treatment time < 8 weeks versus overall treatment time ≥ 10 weeks) and the 3 year DFS and 3 year OS with P = 0.005 and P = 0.002 respectively.
Several similar studies estimated that DFS and OS drops by 1% per day with prolongation of EBRT and HDR ICRT beyond 8 weeks (16). Then, it should be recommended that to start HDR brachytherapy as short as possible, within 1 week of EBRT.
There was no statistically significant relationship between both 3-year DFS and 3-year OS and histology tumor (after adjusting for the residual disease after radiation) and mean total dose to the point A by univariate and multivariate analysis in our study.
Mosalaei et al. (17) showed overall rectal and bladder complication rates were 34.6%. This finding was consistent with our study that showed similar incidence rate of overall rectal and bladder complication (33.7%). Overall rectal and bladder complications were seen in 16 (10.4%) and 36 (23.3 %) patients in our study.
There were some limitations in our study. First, our study had a short median follow up duration (38 months). Second, the most of the EBRT was performed by other centers as the best EBRT protocol is usually based at a single institution. However, our study had 154 patients included in the study and relatively few cases (14%) were excluded.
In conclusion, in this cross sectional-analytic study, early stage, tumor size < 4 cm, no pelvic lymph node involvement and 1 week gap between EBRT and HDR ICRT were independent favorable prognostic factors for three-year DFS. Early stage, tumor size < 4 cm, no pelvic lymph node involvement,1 week gap between EBRT and HDR ICRT and no distant metastasis (during the follow up) were independent favorable prognostic factors for three-year OS. There was no statistically significant relationship between 3-year DFS, 3-year OS and histology tumor (after adjusting for the residual disease after radiation) and mean total dose to the point A by univariate and multivariate analysis.
Our seven years experience with HDR brachytherapy with Co-60 remote after loading system showed that, HDR brachytherapy in treating patients with carcinoma of cervix was successful after EBRT with acceptable rectal and bladder complications.