
1. Background
The epidemiology of Kawasaki disease (KD) suggests that an infectious agent may be a potential disease trigger in susceptible children (1). In Taiwan, a cohort study with 5280 patients matched one-to-one with 5280 control children showed a significantly greater rate of KD in the adenovirus-infected children than in the uninfected children (2). Another study investigating the blood samples of patients with typical KD found viral signatures, including signatures for poliovirus (vaccine strain), measles (vaccine strain), rhinovirus and bocavirus, in more than half of the patients (3). Kawano et al (4) reported that human herpesvirus HHV-6 and HHV-7 reactivation was frequent in KD patients. HHV-6 reactivation, as well as M. pneumoniae, might exacerbate the severity of KD. In recent years, M. pneumoniae has emerged as one of the most common causes of pediatric community-acquired pneumonia (CAP), accounting for 10 - 40% of cases (5, 6). Wang et al (7) found that the occurrence of KD was associated with M. pneumoniae infection, which was subsequently corroborated by Merlin and Chemli (8, 9). In a case series, Vitale et al (10) found that M. pneumoniae may be a possible trigger of KD. A retrospective analysis of 358 patients with KD was performed by Lee (11); 12 patients had high anti-M. pneumoniae antibody (AMA) titres (> 1:640), indicating that KD patients can be concurrently infected, with evident pulmonary symptoms. A prospective study including 450 KD patients demonstrated that M. pneumoniae infections were present in a significant proportion of KD patients (13.8%) (12). The cause of KD was considered to be associated with M. pneumoniae infection.
The major complication of KD is coronary artery aneurysm (CAA), which may result in myocardial ischaemia, myocardial infarction, or sudden death. Many studies have reported risk factors associated with CAA. Intravenous immunoglobulin (IVIG) treatment during the first 10 d of illness has been shown to reduce the prevalence of CAA five-fold (13). Risk factors for persistent CAA include long duration of fever and failure to respond to initial IVIG therapy, which manifests as persistent abnormal laboratory findings. These abnormal findings include low hemoglobin (Hb), low serum albumin, and low serum sodium (i.e., < 135 mEq/L) levels, an elevated heart rate, elevated alanine aminotransferase (ALT), elevated C-reactive protein (CRP), an elevated erythrocyte sedimentation rate (ESR), and elevated white blood cell (WBC) count (14-19). However, no studies have reported a correlation between M. pneumoniae and CAA. We used logistic regression models to evaluate the strength of this correlation.
2. Methods
2.1. Study Population
This retrospective study was conducted from January 2015 to December 2018 and included children with KD in a tertiary children’s hospital in Fujian Province, China. The criteria for the diagnosis of M. pneumoniae infection were positive serological results before administration of IVIG (MP-total antibody test ≥ 1:640 and positive MP-IgM) and related clinical manifestations (fever, dry or productive cough, and pulmonary imaging abnormalities). KD was diagnosed according to the 2017 Guidelines of the American Heart Association (AHA) (20). The calculation of accurate z-scores for coronary artery measurements in children was based on the following formula (21):
where M equals the measurement value of the coronary artery; BSA equals the body surface area; and β1, β2, and MSE are constants. Small CAA was defined as a z-score ≥ 2.5 ~ < 5, medium CAA was defined as a z-score ≥ 5 ~ < 10, and giant CAA was defined as a z-score ≥ 10.
2.2. Demographic and Clinical Data Collection
Medical records were reviewed and the following data were collected: (1) a description of the patient, including age, sex, BSA, length of hospitalization, duration of fever, the presence of conjunctival hyperaemia, the presence of a skin rash, the presence of a strawberry-like appearance of the tongue, enlarged lymph nodes and changes in extremities; (2) laboratory data (the most severe values within 24 h of hospital admission), including a complete blood count, biochemical tests, pre-albumin (PA) levels, CRP levels, the ESR, blood culture results, electrocardiogram results, and chest radiography findings; and (3) co-infection within 24 h after admission according to blood culture results for bacterial infection, passive agglutination test results for MP (Fujirebio Inc.), indirect fluorescent antibody test results for nine common viruses and bacteria known to cause CAP (Vircell.S.L Pneumoslide IgM), PCR-fluorometric test results for Epstein-Barr virus (EBV) and cytomegalovirus (CMV), colloidal gold method test results for enterovirus type 71 (EV71) and enzyme-linked immunosorbent assay (ELISA) results for herpes simplex virus.
2.3. Ethics
The study was approved by the ethics committee of the University (no. 2017-042). All patients and their family members signed the informed consent form, and the data from the patients were analyzed anonymously.
2.4. Statistical Analysis
Data were analysed using IBM SPSS, version 23.0 (Chicago, USA). Descriptive analyses were performed, and the findings were reported as absolute frequencies or rates for categorical variables, the median (min-max) values for quantitative variables with a non-parametric distribution, and the means ± SDs for quantitative variables with a normal distribution. Comparisons of quantitative variables between the two groups were performed using Student's t test or the Wilcoxon rank sum test when appropriate. Comparisons of categorical variables were performed using the χ2 test. Based on the group analysis results, a binary multivariate logistic regression analysis was conducted. P values below 0.05 were considered to indicate statistical significance.
3. Results
3.1. Demographic Characteristics
From January 2015 to December 2018, a total of 357 children with KD were hospital-ized. M. pneumoniae infections (165 cases) were present in a high proportion of the KD patients (46.2%). During data collection, 27 children without complete clinical data before IVIG therapy were excluded, Therefore, our study included 330 children with KD; 201 children were males, and 129 children were females (1.6:1 male: female ratio). We divided our cohort into two groups: the KD with M. pneumoniae infection group (n = 159) and the KD without M. pneumoniae infection group (n = 171). The KD with M. pneumoniae infection group was significantly older than the KD without M. pneumoniae infection group (P < 0.05). However, the two groups had similar sex distributions.
3.2. Clinical Characteristics of the Study Cohort
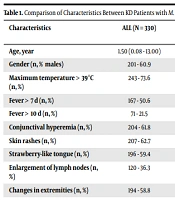
No significant differences were identified in the proportions of children with a maximum temperature > 39°C and a length of fever > 7 days. However, a significant difference was found in the proportion of those with a length of fever > 10 days. Conjunctival hyperemia, skin rash, a strawberry-like appearance of the tongue, enlarged lymph nodes and changes in extremities were common clinical manifestations of KD. Table 1 shows no significant differences in the proportions of those with conjunctival hyperemia, skin rash, a strawberry-like appearance of the tongue, enlarged lymph nodes, and changes in extremities between the two groups.
Table 1.
Comparison of Characteristics Between KD Patients with M. pneumoniae Infection and KD Patients with No M. pneumoniae Infection
| Characteristics | ALL (N = 330) | KD with M. pneumoniae Infection (N = 159) | KD with No M. pneumoniae Infection (N = 171) | F/Z/χ2 | P - Value |
|---|---|---|---|---|---|
| Age (y) | 1.50 (0.08 - 13.00) | 1.57 (0.26 - 8.00) | 1.42 (0.08 - 13.00) | - 3.823 | 0.000 |
| Gender (n, % males) | 201 - 60.9 | 95 - 59.7 | 106 - 62.0 | 0.174 | 0.677 |
| Maximum temperature > 39°C (n, %) | 243 - 73.6 | 122 - 76.7 | 121 - 70.8 | 1.512 | 0.229 |
| Fever > 7 d (n, %) | 167 - 50.6 | 86 - 54.1 | 81 - 47.4 | 1.488 | 0.222 |
| Fever > 10 d (n, %) | 71 - 21.5 | 43 - 27.0 | 28 - 16.4 | 4.515 | 0.034 |
| Conjunctival hyperemia (n, %) | 204 - 61.8 | 104 - 65.4 | 100 - 58.4 | 1.676 | 0.195 |
| Skin rashes (n, %) | 207 - 62.7 | 101 - 63.5 | 106 - 62.0 | 0.083 | 0.773 |
| Strawberry-like tongue (n, %) | 196 - 59.4 | 92 - 57.9 | 104 - 60.8 | 0.299 | 0.585 |
| Enlargement of lymph nodes (n, %) | 120 - 36.3 | 66 - 41.5 | 54 - 31.6 | 3.511 | 0.061 |
| Changes in extremities (n, %) | 194 - 58.8 | 95 - 59.7 | 99 - 57.9 | 0.117 | 0.732 |
| WBC × 109/L | 19.86 (5.14 - 45.64) | 19.63 (5.14 - 45.63) | 20.08 (7.18 - 39.63) | - 0.911 | 0.362 |
| Neutrophil percentage (%) | 68.23 ± 13.94 | 68.02 ± 13.60 | 68.44 ± 14.28 | 14.448 | 0.074 |
| Neutrophil counts, × 109/L | 10.31 (0.92 - 30.88) | 10.24 (1.44 - 30.88) | 10.38 (0.92 - 26.25) | - 0.561 | 0.575 |
| Neutrophil counts/ Lymphocyte counts | 1.87 (0.16 - 17.56) | 1.90 (0.25 - 9.42) | 6.21 (0.16 - 17.56) | - 0.533 | 0.594 |
| RDW (%) | 14.63 (0.03 - 28.50) | 14.52 (0.03 - 28.50) | 14.74 (1.57 - 27.70) | - 1.230 | 0.219 |
| HB, g/L | 101.33 (54.0 - 143.0) | 102.46 (62.0 - 177.0) | 100.29 (54.0 - 143.0) | - 1.765 | 0.078 |
| PLT, ×109/L | 610.47 (165.0 - 1653.0) | 596.04 (165.0 - 1351.0) | 623.89 (202.0 - 1653.0) | - 0.934 | 0.351 |
| CRP, mg/L | 81.46 (0.50 - 316.80) | 74.74 (0.50 - 316.80) | 87.71 (0.50 - 266.40) | - 1.634 | 0.102 |
| ESR | 65.45 (3.0 - 140.0) | 69.23 (3.0 - 140.0) | 61.92 (3.0 - 140.0) | - 1.782 | 0.075 |
| Serum sodium, mmol/L | 135.06 (110.0 - 145.0) | 134.38 (110.0 - 145.0) | 135.71 (110.0 - 145.0) | - 2.337 | 0.019 |
| Serum chloride, mmol/L | 102.55 (86.0 - 112.0) | 102.36 (86.0 - 112.0) | 102.72 (86.0 - 112.0) | - 0.985 | 0.324 |
| Serum potassium, mmol/L | 4.31 ± 0.70 | 4.28 ± 0.62 | 4.34 ± 0.78 | 0.245 | 0.494 |
| Serum calcium, mmol/L | 2.29 (1.66 - 2.82) | 2.27 (1.66 - 2.82) | 2.31 (1.66 - 2.82) | - 1.768 | 0.077 |
| ALT, U/L | 81.31 (7.70 - 968.00) | 72.62 (7.70 - 842.80) | 89.49 (8.60 - 968.00) | - 1.061 | 0.289 |
| AST, U/L | 69.80 (9.60 - 852.30) | 60.33 (9.60 - 622.50) | 78.70 (9.60 - 852.30) | - 0.146 | 0.884 |
| GGT, U/L | 66.34 (5.50 - 600.00) | 60.99 (5.60 - 600.00) | 71.52 (5.50 - 455.20) | - 1.625 | 0.104 |
| TBIL, μmol/L | 9.56 (1.20 - 157.40) | 8.45 (1.20 - 101.40) | 10.62 (1.70 - 157.40) | - 0.934 | 0.350 |
| TC, mmol/L | 3.78 (1.61 - 63.40) | 3.64 (1.61 - 7.00) | 3.92 (1.80 - 63.40) | - 1.189 | 0.234 |
| TG, mmol/L | 1.49 (0.27 - 6.64) | 1.45 (0.27 - 4.16) | 1.52 (0.46 - 6.64) | - 0.568 | 0.570 |
| LDL, mmol/L | 2.17 (0.49 - 5.18) | 2.17 (0.60 - 5.18) | 2.17 (0.49 - 5.18) | - 0.584 | 0.559 |
| HDL, mmol/L | 0.89 (0.30 - 2.18) | 0.88 (0.30 - 1.55) | 0.91 (0.31 - 2.18) | - 0.917 | 0.359 |
| PA, mg/dL | 12.11 (4.20 - 34.90) | 11.43 (4.53 - 29.38) | 12.73 (4.20 - 32.23) | - 2.241 | 0.025 |
| Albumin, g/L | 36.42 (19.40 - 51.40) | 35.90 (19.40 - 48.40) | 36.91 (23.50 - 51.40) | - 2.209 | 0.042 |
| LDH, U/L | 392.33 (12.11 - 2150.00) | 407.36 (109.30 - 2150.00) | 378.35 (12.11 - 1867.00) | - 0.874 | 0.382 |
| CK, U/L | 74.34 (6.70 - 5200.00) | 62.26 (6.70 - 1000.00) | 85.69 (7.80 - 5200.00) | - 0.135 | 0.892 |
| CKMB, U/L | 26.10 (2.80 - 161.00) | 24.73 (2.80 - 144.80) | 27.40 (3.00 - 161.00) | - 1.032 | 0.302 |
| Length of hospitalization (d) | 9.52 (2.0 - 32.0) | 9.41 (2.0 - 32.0) | 9.63 (2.0 - 32.0) | - 0.420 | 0.674 |
| Involving bilateral coronary arteries (n, %) | 101 - 30.6 | 42 - 26.4 | 59 - 34.5 | 2.538 | 0.111 |
| Small CAA (n, %) | 210 - 63.6 | 92 - 57.8 | 118 - 69.0 | 4.422 | 0.035 |
| Medium and Giant CAA (n, %) | 13 - 3.9 | 8 - 5.0 | 5 - 3.0 | 0.967 | 0.242 |
| Intravenous immunoglobulin non-responsive KD (n, %) | 45 - 13.6 | 26 - 16.4 | 19 - 11.1 | 1.922 | 0.166 |
Abbreviations: KD, Kawasaki Disease; M. pneumoniae, Mycoplasma pneumoniae; WBC, white blood cell count; RDW, red blood cell volume distribution width; HB, hemoglobin; PLT, platelet count; CRP, C-reactive protein; ESR, the erythrocyte sedimentation rate; ALT, alanine aminotransferase; AST, aspartate transaminase; GGT, γ-glutamyl transpeptidase; TBIL, total bilirubin; TC, total cholesterol; TG, triglycerides, LDL, low-density lipoprotein; HDL, high-density lipoprotein; PA, pre-albumin; LDH, lactate dehydrogenase; CK, creatinine kinase; CKMB, MB isoenzyme of creatine kinase; CAA, coronary artery aneurysm.
Regarding laboratory examinations, the average lymphocyte counts, serum sodium levels, PA levels, and albumin levels were significantly different between the two groups. In addition, a significant difference in the incidence of small CAA was ob-served between the two groups (P < 0.05), although no differences were observed for medium and giant CAAs and associated variables (Table 1).
3.3. Correlation Between M. pneumoniae Infection and Small CAA
Statistically significant clinical and laboratory parameters were analysed to assess as-sociations between independent variables and small CAA using binary logistic regression modelling. The categorical variables were the proportion of patients with a length of fever > 10 days and M. pneumoniae infection. The continuous variables were age, PA level, lymphocyte count, serum sodium level, and albumin level. We found that M. pneumoniae infection (OR: 0.515; 95% CI: 0.309 - 0.860; P = 0.011), serum sodium lev-el (OR: 0.910; 95% CI: 0.851 - 0.972; P = 0.005), and PA level (OR: 0.900; 95% CI: 0.854 - 0.949; P ≤ 0.001) were independent variables according to the final model, suggesting that M. pneumoniae infection may be associated with a decreased incidence of small CAA. However, decreased serum sodium and PA levels increased the risk of small CAA independently (Table 2).
Table 2.
Independent Variables for Small CAA by Binary Logistic Regression Analysis
| B | S.E. | Wals | Df | Sig | Exp (B) | Exp (B) 95% Confidence Interval | ||
|---|---|---|---|---|---|---|---|---|
| Lower Bound | Upper Bound | |||||||
| M. pneumoniae infection | -0.663 | 0.261 | 6.434 | 1 | 0.011 | 0.515 | 0.309 | 0.860 |
| Serum sodium | -0.095 | 0.034 | 7.871 | 1 | 0.005 | 0.910 | 0.851 | 0.972 |
| PA | -0.105 | 0.027 | 15.073 | 1 | 0.000 | 0.900 | 0.854 | 0.949 |
Abbreviations: CAA, coronary artery aneurysm; M. pneumoniae, Mycoplasma pneumoniae; PA, pre-albumin.
4. Discussion
The prevalence of M. pneumoniae infection among KD patients (46.2%) in this cohort was much higher than that reported in the literature (12). A major cause may be the epidemics of M. pneumoniae. Cyclic outbreaks of M. pneumoniae infections tend to occur in different regions every 3 - 7 years. Since 2010, outbreaks of M. pneumoniae have been reported in some European countries (22), with similar reports in China (23). In the last five years, the prevalence of M. pneumoniae infections has increased annually in Fujian Province, China. Another major reason for the increased prevalence may be the fact that the children in this study were presenting to a tertiary children’s hospital; therefore, patients with KD and M. pneumoniae may have been overrepresented.
The pathological mechanisms of KD due to M. pneumoniae infection remain largely unknown. Currently, the consensus by researchers is that indirect tissue injury by M. pneumoniae triggers an inflammatory response and overall activation of the immune system (24). Immune-stimulatory components of M. pneumoniae (including the M. pneumoniae N602 protein, whose inflammatory capacity has been estimated to be 100-fold higher than that of other proteins) can stimulate a high percentage of T cells by binding to the Vβ region of T cell receptors, which can stimulate the production of proinflammatory cytokines/chemokines and reactive oxygen/nitrogen species (ROS/NOS) and prolong the length of fever, subsequently eliciting systemic vasculitis (25, 26). However, our data indicated that the coronary arteries were not severely affected by M. pneumoniae infection, which is consistent with previously reported data (7, 27). Our data also indicated that no differences existed between medium and giant CAAs, possibly because the natural course of KD due to M. pneumoniae is likely similar to that of pulmonary infection with M. pneumoniae, which is usually mild and self-limiting (28), but severe, fulminant or fatal cases have also been found as the condition deteriorates. Additionally, the genetic background of an individual likely affects disease susceptibility (26). We postulate that M. pneumoniae infection might be associated with a decreased incidence of small CAA. However, our sample population was small; therefore, further studies with larger numbers of patients are needed.
According to the data in the present study, serum sodium and PA levels were independent risk factors for small CAA. Hyponatremia increases the secretion of aldosterone, which regulates contraction and remodelling of the vessel walls. The severity of vascular inflammation in acute KD with hyponatremia might worsen the prognosis of coronary vasculature. The sodium level may be a simple predictor of KD‘s cardiovascular sequelae. Our results corroborate the results of other reports (29-31). Hypoalbuminemia has been reported to be independently associated with the occurrence of progressive coronary dilatation and is an effective predictor of IVIG resistance (32, 33). Kim JH reported that the KD with adenovirus group was significantly associated with presence of hypoalbuminemia compared with the adenoviral infection group. However, hypoalbuminemia was not the significant predictive factor of KD in the multivariate analysis (34). Our study also showed that the albumin level was not an independent risk factor for small CAA, but the PA level was an independent risk factor. A possible reason for this result is that PA has a short average lifespan; therefore, it can better estimate the nutritional and inflammatory status of a child at the precise time at which it is measured (35).
In this study, we showed that children with KD who had M. pneumoniae infection were older and tended to experience longer periods of fever than the controls, possibly because M. pneumoniae infection is more frequently observed in children, particularly school-age children, than in adults (36). Older children are more immunologically mature than younger children, and the production of cytokines in response to M. pneumoniae increases, consequently increasing the likelihood of extrapulmonary complications, including KD, in older children infected with M. pneumoniae. Fever is the most common symptom of KD plus M. pneumoniae infection. Our results indicate that long-term fever (i.e., > 10 d) in children with M. pneumoniae infection may induce complications associated with KD.
This study has some limitations. First, this was a retrospective observational study in a single centre, which may have resulted in certain inherent selection biases. Second, the results might be limited because the children in this study were presenting to a tertiary children’s hospital; therefore, patients with KD and M. pneumoniae may have been overrepresented. Third, only obvious, severe infections on admission were considered, and some patients may have had subclinical infection, which would bias our study towards severe disease. Nevertheless, we believe that this study serves as a preliminary survey of the relationship between M. pneumoniae and CAA. Larger, prospective, multicenter studies may be justified to better quantify the risk and to investigate whether any other associations exist.
In conclusion, the present study demonstrated that M. pneumoniae infection occurred in a significant proportion of KD patients (46.2%). M. pneumoniae infection might be associated with a decreased incidence of small CAA. Further studies with large sample sizes are needed. Serum sodium and PA levels were important independent risk factors for small CAA and should be closely managed.