
1. Background
Today, chronic diseases account for a large proportion of health problems, not only in developing countries but also in many developed countries (1). It is estimated that more than 1.5 billion people worldwide will have high blood pressure by 2025, which will increase the risk of heart disease by 50% and the risk of stroke by 75% (2). With the high prevalence and serious complications on body organs, high blood pressure is a disease, making major health issues worldwide. The presence of one billion hypertensive people and the annual occurrence of four million deaths all over the world are the direct results of this disease (3). Blood pressure can be controlled only in 20% of patients suffering from hypertension in Iran (4). In 2019, 21,000 people were diagnosed with high blood pressure in Sistan and Baluchestan province, and according to the reports in this area, about 700 people died because of high blood pressure in 1996. Besides, a total of 29,549 patients with hypertension have been recently identified in a medical center affiliated with Zahedan University of Medical Sciences (5, 6).
Complications such as myocardial infarction, stroke, heart failure, atrial fibrillation, aortic rupture, peripheral artery disease, and cognitive problems can be prevented by the early detection of hypertension. Indeed, hypertension is a preventable risk factor for these complications (7, 8), which can be controlled by measures like lifestyle modification such as restricting sodium in the diet, weight loss, increasing activity and exercise, eating more fruits and vegetables, not smoking, reducing alcohol consumption, and adhering to the prescribed medication regimen (9). Therefore, self-efficacy is an important prerequisite in the process of changing behavior and improving the quality of life (10).
The incidence of any chronic disease has a great impact on the patient’s quality of life. Physical, psychological, social, and economic dimensions of the quality of life undergo many changes due to the duration and severity of chronic diseases (11). Numerous studies have shown that the quality of life of those patients is low (12, 13), which, in turn, reduces life expectancy and increases the risk of depression, social isolation, reduced daily activities, dependence, and economic burden (14). It is worth mentioning that nowadays, one of the most important goals of the Iranian health care system is to improve the quality of life (15). Thus, educational interventions (16), empowerment models (17), self-care education (18), and integrated strategies for health services delivery have received growing attention (19).
Currently, given the growing rate of chronic diseases and lack of physical space in treatment centers, attention to the family-centered empowerment model is a key element in medical and nursing education (20). Family-centered empowerment reflects professional interactions with families so that family members can gain a sense of control over their lives (21). The family empowerment model considers the beliefs and cultural values of family members, takes their needs into account, and tries to reduce their independence from the hospital (22). The term family-centered empowerment has played an important role in nursing and medical studies in recent decades, and this has been considered a necessity of the nursing process (23). Family-centered care is defined as an innovative approach to health care planning, delivery, and evaluation, based on beneficial and reciprocal collaboration between patients, families, and caregivers (24). Educating family members about disease control and even prevention can be important (25) because there is a strong relationship between family and members' health status (26). The family-centered empowerment model can empower individuals by emphasizing perceived threats (through perceived severity and sensitivity), promoting self-efficacy (by fostering necessary skills), and increasing self-esteem (through self-help, self-control, and self-efficacy) (27).
The family-centered empowerment model consists of four stages of identification, sensitization, control, and evaluation (28). the mentioned pattern is a native model and concepts of qualitative research of grounded theory. This model can increase the knowledge, beliefs, and skills of the patient and the family by emphasizing the important role of the family to play in terms of motivation, psychology, self-efficacy, and self-esteem. The main goal of the family-centered empowerment model is to empower the patients and their families to improve their level of health (29). A review study showed that this model affects the self-esteem (30) and the lifestyle of patients with hypertension (31), self-efficacy of patients on hemodialysis (32), and the quality of life of patients with myocardial infarction (33). Since the nurse is the best source for transferring information among the health team, patients, and their families, many studies have highlighted the effects of this model on patients with other diagnoses and different variables (23).
2. Objectives
The present study aimed to investigate the effect of the family-centered empowerment model on the quality of life of patients with hypertension.
3. Methods
The present clinical trial study was performed with registration number IRCT20201016049043N1 based on a permit from the Ethics Committee of Zahedan University of Medical Sciences (IR.ZAUMS.REC.1399.171) in Sistan and Baluchestan province. This province is located in the southeast of Iran, Central Asia. The participants were patients with hypertension who were referred to the comprehensive health centers in Zahedan in 2020.
The inclusion criteria included having a history of hypertension diagnosed in medical centers, having a blood pressure of higher than 140/90 for at least six months, having minimum literacy, being 25-65-years-old, and not participating in the same training program in the past six months. The inclusion criteria for the caregiver included having minimum literacy and living in the patient's home. The exclusion criteria for the patients were having an acute illness, hospitalization during the study, the unwillingness of the patient and his family to continue participating in the study, and not taking part in the posttest.
Sampling was performed in several steps. First, several urban districts were considered clusters. Then, two districts and one center from each district were randomly selected, and a list of eligible patients was prepared based on the inclusion criteria from the SIB system (The integrated health system) and the medical files available in the two centers. Out of 100 eligible patients, 70 patients were selected from two centers using convenience sampling. The selected patients were randomly assigned to the intervention and control groups (Figure 1).
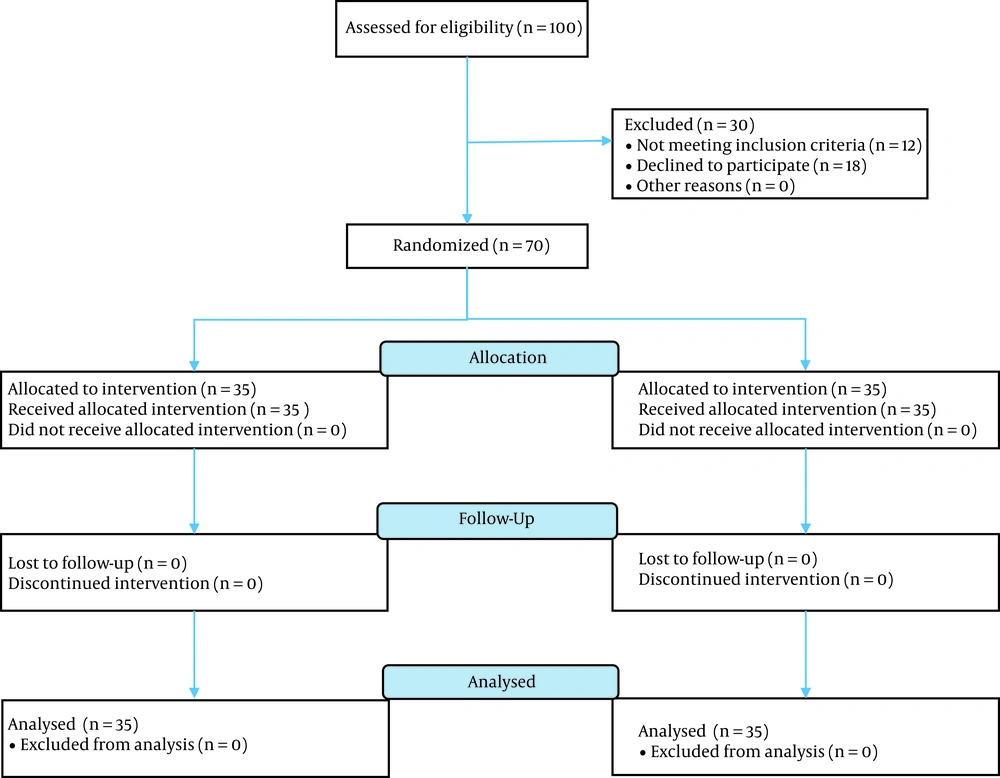
Figure 1.
The consort flow diagram
With a possible dropouts, 35 patients in each group and a total of 70 patients were evaluated (17).
The instruments used in the present study were a personal information form and the Quality of Life Questionnaire for patients with hypertension. The personal information form assessed the patients’ age, education (for the patient and caregiver), body mass index, duration of illness, underlying disease(s), gender, ethnicity, employment status, primary caregiver, marriage, smoking, a family history of hypertension, and the disease control method. The Quality of Life Questionnaire for Patients with Hypertension was designed and validated by Shamsi (2016). This questionnaire contains 42 items to assess the quality of life of Iranian patients with hypertension and was piloted in Tehran in 2015-2016. The items are scored on a five-point Likert scale: Never (5), rarely (4), sometimes (3), often (2), and always (1). The total score obtained varies from 42 to 210, and a higher score means a higher quality of life. The face, content, and construct validity indices of the questionnaire were confirmed, and its reliability with Cronbach’s alpha was reported to be 0.89 (34).
After obtaining the necessary permits, the researcher referred to the selected health centers and provided some information about the objectives of the study and the procedure taken to conduct it. Then, he invited the patients to participate in the study. First, the personal information form and the questionnaire were completed by conducting interviews with the participants in both groups. Afterward, the intervention was conducted for the participants in the intervention group using the empowerment model in four 60-min sessions for four weeks. The training sessions were held individually for each patient and a member of his family as the main caregiver (Table 1).
Table 1.
Training Sessions
| Educational Content | |
|---|---|
| Step one, sessions 1and 2 | Familiarity with the objectives of the intervention program, the generality of the disease, the importance of a healthy lifestyle to the individual’s health and prevention of chronic diseases, increasing awareness and improving the attitude of the participants about healthy nutrition; raising their awareness and improving their attitudes toward physical activity and its importance in the prevention and control of hypertension, improving the mental health of the participants with stories about ways to manage stress, improving the spiritual health of the participants with stories about the impact of religion on health. |
| Step two, session 3 | Familiarity with devices, principles, and objective methods of measuring blood pressure, how to solve problems, providing suggestions for solving problems, emphasizing the client's skills |
| Step three, session 4 | Reviewing content by the client accompanied by relevant interventions and support by the researcher, questions and answers |
| Step four | Evaluation |
The sessions were held in the form of discussions, verbal exchanges, questions, and answers by the researcher in health centers using educational aids such as PowerPoint presentations, videos, and booklets based on valid scientific texts (35) under the supervision of experts in this field. The participants in the control group did not receive any training. During the training, caregivers were asked to practice the given training content in the presence of a nurse to remove any possible ambiguities. The family-centered empowerment model was implemented through the following steps:
3.1. Step 1 (Perceiving the Threats)
The first step in the family-centered empowerment model was to increase the intensity and sensitivity perceived by the participants by lecturing and discussing the nature and complications of the disease, aggravating factors, nutritional factors, exercise, and other effective factors in disease control in two sessions. At the end of the training session, the participants’ comprehension was ensured through questions and answers.
3.2. Step 2 (Self-efficacy)
The focus was on improving the problem-solving skills. For this purpose, a problem-solving session was held individually for patients and their families. In these sessions, patients and families were faced with problems and the problem-solving process. They were asked to discuss concrete examples of their situation and what they had done to solve the problem. Besides, the practical methods of measuring blood pressure and weight and the consequences of not controlling these two variables and their normal levels were explained in detail. Then, the patients and families were asked to practice the skills. At this stage, the best way to solve the patients’ problems was selected with a focus on the clients’ skills.
3.3. Step 3 (Self-confidence)
At this stage, the patient was asked to teach the family members the issues covered in the previous sessions with the help of the researcher. The purpose of this step was to increase the patients’ self-confidence concerning their ability to provide information to family members and family support. To ensure and follow up on this step, several questions related to the educational issues were given to the patient to be answered with the help of family members and be delivered to the researcher.
3.4. Step 4 (Evaluation)
The evaluation was performed one and three months after the intervention in the two groups by completing the quality of life questionnaire. Furthermore, during the study, the participants were in contact with the researcher by phone to solve possible problems and answer possible questions.
To comply with ethical principles, a training booklet was provided to the participants in both intervention and control groups after completing the intervention. The questionnaires were completed in person or by contacting the participants so that the researcher could cooperate if there was any ambiguity to fill in the questionnaires. The collected data were analyzed by SPSS software (version 22).
Data normality was checked using the Shapiro-Wilk test. The chi-square test was used to compare the frequency of qualitative variables between the two groups. Furthermore, the independent samples t test was run to compare the means in the two intervention and control groups, and the analysis of variance was used before the intervention, as well as one and three months after the intervention. The assumptions were established the independence of observations, normality in population distributions, and homogeneity of population variances, and the homogeneity of the variances were established. The significance level in this study was less than 0.05.
4. Results
The findings of the study showed that the participants in the intervention and control groups were not significantly different in terms of demographic characteristics, including age, patient’s and caregiver’s education, body mass index, duration of illness, underlying disease, gender, ethnicity, employment status, primary caregiver, marital status, smoking, family history of hypertension, and disease control. The patients in the intervention and control groups were in their 40s. The patients had a body mass index of 29. The duration of the disease was 10 - 12 years. The majority of the participants in both groups had an underlying disease. Most of them were female and unemployed. Besides, 60% of the patients in the intervention group and 40% of the patients in the control group were Baloch. The main caregivers of the patients were children in the intervention group (65.7%) and spouses in the control group (54.3%) (Table 2).
Table 2.
The Participants’ Demographic Characteristics in Two Groups a
| Variable | Control Group | Intervention Group | P |
|---|---|---|---|
| Age | 7.74 ±49.91 | 6.31 ±48.80 | 0.51 b |
| Patients' academic years | 3.75±8.97 | 3.30 ± 7.77 | 0.16 b |
| Caregiver's academic years | 3.17 ± 10.80 | 3.03 ± 10.31 | 0.51 b |
| BMI | 5.10 ± 28.42 | 3.95± 29.24 | 0.46 b |
| Duration of the disease | 6.03 ± 10.09 | 5.38 ± 12.11 | 0.14 b |
| Underlying disease | 0.60 c | ||
| Yes | 24 (68.6) | 26 (74.3) | |
| No | 11 (31.4) | 9 (25.7) | |
| Gender | 0.33 c | ||
| Female | 23 (65.7) | 18 (51.4) | |
| Male | 12 (34.3) | 17 (48.6) | |
| Ethnicity | 0.80 c | ||
| Baloch | 21 (60) | 20 (57.1) | |
| Sistani | 14 (40) | 15 (42.9) | |
| Occupation | 0.08 c | ||
| Employed | 11 (31.4) | 13 (37.1) | |
| Unemployed | 24 (68.6) | 22 (62.9) | |
| Main caregiver | 0.09 c | ||
| Spouse | 12 (34.3) | 19 (54.3) | |
| Child | 23 (65.7) | 16 (45.7) | |
| Marital status | 0.78 c | ||
| Married | 27 (77.1) | 26 (74.3) | |
| Unmarried | 8 (22.9) | 9 (25.7) | |
| Smoking | 0.61 c | ||
| Yes | 11 (31.4) | 13 (37.1) | |
| No | 24 (68.6) | 22 (62.9) | |
| Family history of hypertension | 0.25 c | ||
| Yes | 25 (71.4) | 29 (82.9) | |
| No | 10 (28.6) | 6 (17.1) | |
| Blood pressure control | 0.60 c | ||
| With medication | 23 (65.7) | 25 (71.4) | |
| Without medication | 12 (34.4) | 10 (28.6) |
aValues are expressed as mean ± SD or No. (%).
bTest Independent t
cChi-square
The results showed that the two groups did not differ significantly in terms of the quality of life in the pre-intervention stage (P = 0.16); but after the intervention, there was a significant difference between the two groups (P < 0.001). The mean scores of the quality of life in the intervention group before, one month, and three months after the intervention were 132.62 ± 15.96, 143.68 ± 9.52, and 143.22 ± 10.25, and the corresponding values for the control group were 137.10 ± 14.44, 137.17 ± 10.41, and 137.28 ± 10.46, respectively. The results of repeated-measures analysis of variance on quality of life showed that changes in the quality of life scores over time were significant (P < 0.001), with greater changes observed in the intervention group than in the control group (Table 3).
Table 3.
Results of Repeated-measures Analysis of Variance for Quality of Life in Patients with Hypertension in Two Groups
| Variable | Sum of Squares | df | Mean Square | F | P |
|---|---|---|---|---|---|
| Time | 1009.82 | 1 | 1009.82 | 70.98 | < 0.001 |
| Group | 368.01 | 1 | 368.01 | 1.003 | < 0.001 |
| Time × group | 956.82 | 1 | 956.82 | 67.26 | < 0.001 |
| Error | 24947.69 | 68 | 366.87 |
the results showed that the mean score quality of life of the participants in the intervention group were significantly different from the pretest score in the second phase (P = 0.008) and third phase (P = 0.01) (Figure 2).
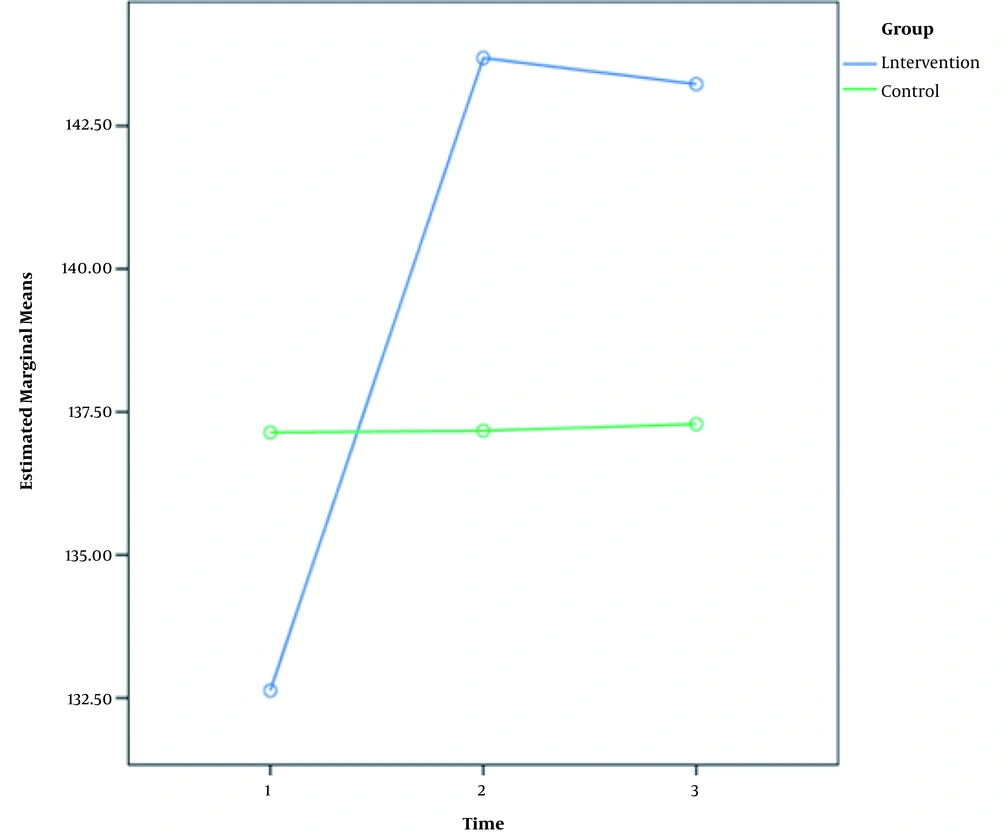
Figure 2.
Line graph showing changes in patients’ quality of life scores before and one and three months after implementing the family empowerment model in the control and intervention groups
5. Discussion
The results of the study showed that the implementation of the family-centered empowerment model improved the hypertensive patients’ quality of life. Accordingly, it can be said that the number of training sessions and the time allotted for educating patients and their families, ample opportunity to learn self-care content and skills, discussion, and active participation of the patient with an active family member were the main advantages of the model that contributed to achieving positive consistent outcomes in this study.
Mohalli et al. studied the effect of the family-centered empowerment model on empowerment indices of patients with hypertension and showed that the knowledge, self-esteem, and self-efficacy of patients with hypertension increased in the experimental group (36), as was evident in the present study. This study was similar to the present study in terms of the sample size and intervention process, but the final evaluation was performed 1.5 months later. Babaei-Sis et al. examined the effect of lifestyle modification training intervention on blood pressure control in patients with hypertension and confirmed the effectiveness of the educational intervention for promoting physical activity, weight management, nutrition, and mental health in patients with hypertension (31). These findings were in line with the results of the present study, with the advantage that it was performed on 210 people. Bairami et al. examined the relationship between self-care behaviors and quality of life in patients with hypertension who were referred to comprehensive health centers in Hamadan. The results showed a positive significant correlation between the overall scores of quality of life and self-care behaviors (37), which confirmed the results of the current study. Keshvari et al. investigated the effect of the family-centered empowerment model on blood pressure and empowerment of the elderly with hypertension and found that the empowerment of the elderly with hypertension led to improved blood pressure (38). This finding was consistent with the results of the present study, with the difference that the evaluation was performed one week and one month later.
Similar to the present study, Noori et al. explored the effect of the family-centered empowerment model on the quality of life of patients with hypertension and showed that implementing the family-centered empowerment model increased the patients’ quality of life and reduced their blood pressure (17). Contrary to the present study, the authors used the general quality of life questionnaire, and the effects of the interventions were measured 1.5 months later. Escortell-Mayor et al. investigated the effect of education on patients at risk for cardiovascular problems and with poor blood pressure control. The results of this study showed a statistically significant difference between the two groups, and education led to better control of blood pressure and lower blood cholesterol (39), which was in line with the results of the present study. Mini et al. investigated the effect of planned training on blood pressure control among teachers in Kerala, India, and showed that behavioral intervention had a significant effect on blood pressure control (40), which was consistent with the results of the present study. Gong et al. examined the effectiveness of community-based physical activity programs in preventing stroke and heart attack among patients with hypertension aged over 55 years and reported a significant difference in the incidence of stroke and heart attack. Besides, the physical activity of the patients in the intervention group increased after six months (41), which partly confirmed the results of the present study. Atak et al. performed a family-centered education intervention on a group of patients with diabetes and reported a relative improvement in some areas of quality of life, which was not statistically significant. This study used a different target group and limited training sessions with short duration and insufficient follow-up, which led to different results from the current study findings (42). The results of studies by Sargazi Shad et al. (43), Pilevar et al. (44), Rostami et al. (28), Davarpanah et al. (45), and Rajabi et al. (46) on the quality of life of patients with chronic diseases such as diabetes, rheumatoid arthritis, hemophilia, and leukemia have shown the positive significant effects of the family-centered empowerment model.
5.1. Conclusions
The implementation of the family-centered empowerment model on patients suffering from hypertension improved the patients’ quality of life. These types of interventions can help caregivers to improve the quality of their intensive care. Since high blood pressure is not treatable and needs to be controlled, educating and empowering family members can positively influence the self-care behaviors of patients with high blood pressure. Thus, nurses can use this model for engaging patients and family members in medical care.
5.2. Limitations
As a limitation to this study, the COVID-19 outbreak made the participants not have the maximum cooperation in fully implementing the training intervention.