1. Background
Jaundice is the most common reason for admission during the 1st month of life. Multiple variables (maternal, infantile, during labor and environmental factors) affect the course and severity of jaundice (1). Although there may be a benefit to patients with mild hyperbilirubinemia, the subjects with high elevation of serum bilirubin are endangered due to accumulation of bilirubin in the brain tissue (1, 2). Enhanced enterohepatic circulation of bilirubin (EHC) that can occur with resection or bypass in adults or ileal inflammation leads to hypersecretion of bilirubin into the bile with increased formation of black pigment gall stones (3, 4). Since active transport for non-conjugated bilirubin is not proved in the intestine, bilirubin may cycle only via passive diffusion under certain conditions (3-5). Interestingly, two thirds of bilirubin enter the systemic circulation; the remainder reabsorbed from the intestine is removed from blood by the liver (3-7). The final product of heme protein catabolism is an unconjugated bilirubin produced in the reticuloendothelial cells after a chain of enzymatic reactions by the oxygenase, reductase and non-enzymatic reducing agents. Conjugated bilirubin pigments can also be partly due to the deposition of the final product conjugations in hepatocyte by the enzyme bilirubin UDP-glucuronosyl transferase to form a polar water-soluble bilirubin glucuronide (8). One of the factors that affect the severity and incidence of jaundice is the level of serum zinc.
Physiopathology of idiopathic jaundice is unknown in the neonates. Animal studies show that oral administration of zinc decreases serum bilirubin level in the rats. Mendez-Sanchez et al. showed that zinc salts can deposit unconjugated bilirubin and that zinc sulfate suppressed enterohepatic circulation of bilirubin in hamsters (8). Consistent with the study by Vreman et al. who reported that zinc is an inhibitor of heme oxygenase enzyme in both in vitro and in vivo. Administration of zinc (4 μumol/kg) decreased carbon monoxide (CO) and bilirubin levels significantly one to six hours after treatment (9). Zinc salts and other elements such as strontium inhibit the hem-oxygenase enzymes and as a result may prevent jaundice (10).
2. Objectives
The current study aimed to compare the serum zinc level between the healthy neonates and infants with jaundice.
3. Patients and Methods
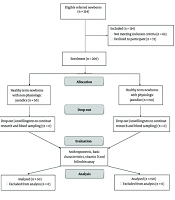
After the approval of the study by the Ethical committee of Mashhad University of Medical Sciences, parental consent was obtained for each infant. A case-control study was performed from April 2008 to October 2010 in the neonatal intensive care unit (NICU) and obstetrics department, Ghaem hospital, Mashhad, Iran.
Infants with jaundice were treated and formed the case group. Neonates without jaundice formed the control group. Also, the level of zinc serum, severity of jaundice, the type and duration of treatment of the referred infants with jaundice were recorded.
A total of 263 neonates completed the study. Healthy infants with idiopathic jaundice and gestational age >35 weeks were included. Neonates with sepsis, any congenital abnormalities or with ABO blood group system, RH incompatibility; or glucose-6-phosphate dehydrogenase (G-6PD) deficiency were excluded from the study.
To evaluate the serum zinc level, 2 mL of umbilical cord blood were collected and transferred into sterile tubes. All sterile tubes were rinsed with deionized water and acids to be free of trace elements. The blood samples were centrifuged at 1000 rpm and stored at −70°C for future analysis.
Neonates were evaluated for incidence of jaundice in days two, five and seven after birth. Serum levels of zinc and bilirubin were assessed for 114 neonates without jaundice (control group) and 149 neonates with jaundice (case group) using atomic absorption spectrometry. In addition, the amount of jaundice, and duration and type of treatment were recorded in neonates with jaundice. To evaluate jaundice causes, Coombs test (direct and indirect), PBS, Retice count, direct and indirect bilirubin, cell blood count, blood hematocrit and platelet counts were determined in the case group.
3.1. Statistical Analysis
Spearman correlation coefficient, chi-square and Mann-Whitney tests were employed to analyze the obtained data by SPSS software. The data were assessed for normality using the Kolmogorov-Smirnov test. P values less than 0.05 were considered significant.
4. Results
In the current study, 263 neonates were recruited [case group (n = 149) and control group (n = 114)] Table 1. Mean value of serum zinc level was 928.81 ± 247.61 μmol/L in all neonates. Mean of zinc level in the control and case groups were 1024.74 ± 245.17, and 841.42 ± 211.99 μmol/L respectively (P < 0.001) (Figure 1). There was a positive correlation between the level of bilirubin and hospitalization (Table 1, P < 0.001, r = 0.356). Thirty-eight of the subjects were excluded due to failure to follow up, the wrong phone number (16 infants), inaccessibility (12 infants) and physiologic hyperbilirubinemia (10 infants).
Table 1.
Characteristics of Mothers and Neonates in the Two Groups
| Case Group (n = 149) | Control Group (n = 114) | P Value | |
|---|---|---|---|
| Maternal age, y a | 27.75 ± 5.59 | 26.52 ± 5.25 | 0.071 |
| Multi parity, % | 49 | 64 | 0.009 |
| Age of neonate, d a | 3.40 ± 1.61 | 6.75 ± 4.88 | < 0.001 |
| Hospitalization, d a | 2.42 ± 1.51 | 2.02 ± 0.77 | 0.014 |
| Mode of delivery | 0.053 | ||
| Caesarian | 69 | 40 | |
| Vaginal | 79 | 74 | |
| History of a child with jaundice | 0.075 | ||
| Yes | 9 | 17 | |
| No | 140 | 97 | |
| Gender | 0.343 | ||
| Male | 56 | 83 | |
| Female | 56 | 66 |
aValues are presented as mean ± SD.
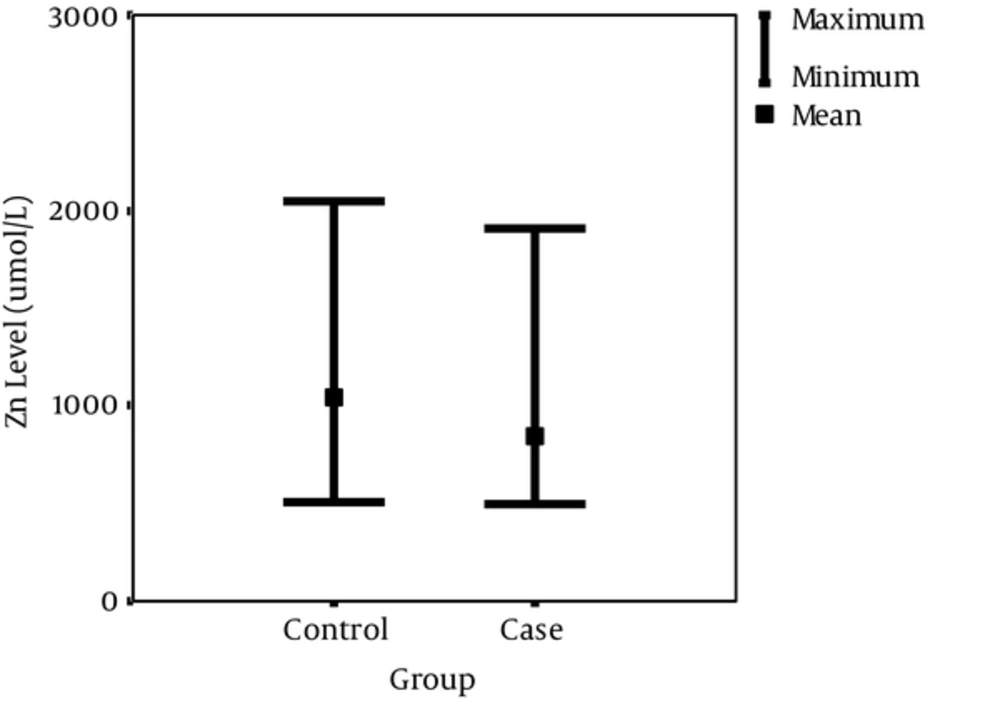
Figure 1.
Mean and Range of Changes of Zinc Level in the Case and Control Groups
There was no association between the age of neonates and serum zinc levels between the two groups (P = 0.47) Figure 2. The means of maternal age were 26.52 ± 5.25 and 27.75 ± 5.59 in the control and case groups, respectively. No significant correlation was found between serum level of zinc and maternal age (P = 0.30).
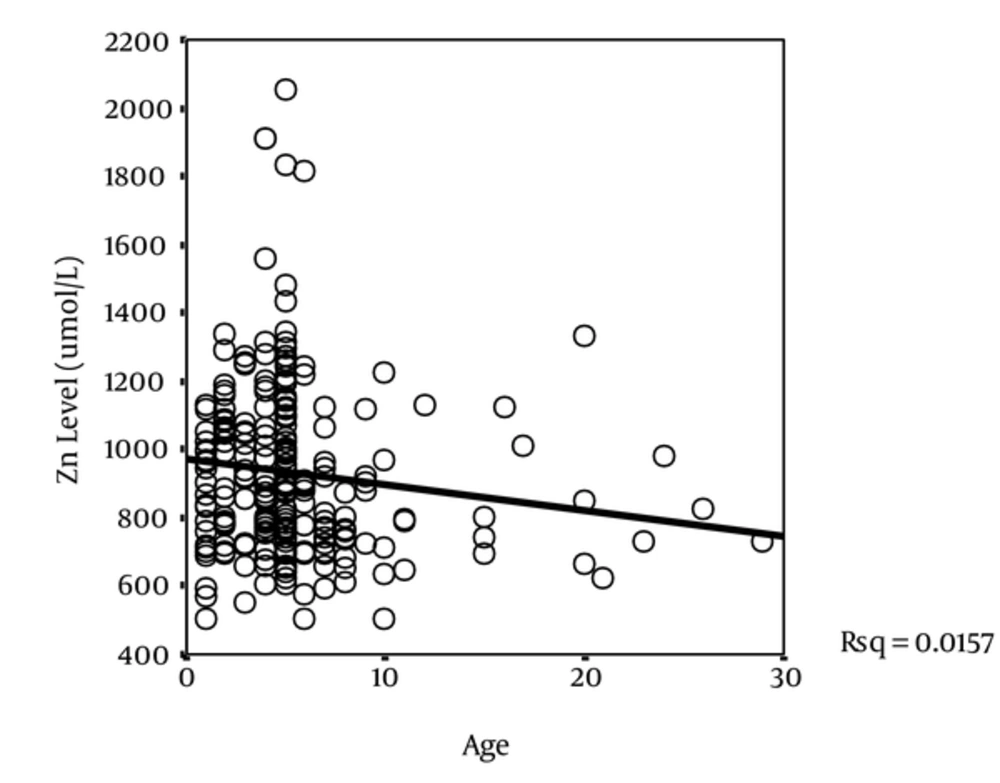
Figure 2.
Relationship Between the Age of Neonates and Zinc Level
The rates of multi parity were 64% and 49% between mothers in the control and case groups, respectively. There was no correlation between multi parity and serum zinc levels between the two groups (P = 0.90).
In the control group, 35% of infants were delivered by caesarian and 65% of them were delivered vaginally. In the case group 47% of mothers had caesarian delivery whereas 53% of them had a vaginal delivery (P = 0.05) Table 1. The mean value of the serum zinc level was 897.92 ± 230 in the neonates delivered by caesarian and this value was 953.72 ± 255.93 in the neonates delivered vaginally. There was no significant correlation between the mode of delivery and level of serum zinc in the neonates (P = 0.08). There was a significant correlation between neonatal age and jaundice (3.40 ± 1.61 in the control group versus 6.75 ± 4.88 days in the case group) (P = 0.001, Table 1).
In the control group 50% of infants were boys and 50% girl whereas in the case group 56% of neonates were boy and 44% girl (P = 0.34, Table 1). No significant correlation was observed between serum zinc level and gender of the neonates (P = 0.51, Table 2).
Table 2.
Relationship Between Serum Zinc Concentrations (umol/L) and Factors of Neonates and Mothers in the Case and Control Groups
| Factors | Control Group a | P Value | Case Group a | P Value |
|---|---|---|---|---|
| Having another child with jaundice | 0.760 | 0.189 | ||
| Yes | 1027.00 ± 156.32 | 915.79 ± 312.64 | ||
| No | 1054.23 ± 261.79 | 826.79 ± 184.28 | ||
| Mode of delivery | 0.513 | 0.338 | ||
| Caesarian | 1024.21 ± 270.84 | 824.09 ± 178.57 | ||
| Vaginal | 1056.72 ± 233.64 | 858.65 ± 239.46 | ||
| Gender | 0.673 | 0.772 | ||
| Male | 1031.60 ± 114.83 | 835.36 ± 215.80 | ||
| Female | 1051.83 ± 294.73 | 846.37 ± 214.28 |
aValues are presented as mean ± SD.
Table 3.
Mean and Range of Changes of the Zinc Level Based on the Incidence of Jaundice
| Age of Incidence of Jaundice | Mean of Zinc umol/La | Range, Minimum - Maximum |
|---|---|---|
| Two days | 207.86 ± 845.16 | 550 - 1910 |
| Three days | 202.12 ± 820.40 | 502 - 1813 |
| Four days and more | 237.49 ± 911.31 | 622 - 1480 |
| Total | 211.14 ± 845.99 | 502 - 1910 |
aValues are presented as mean ± SD.
No significant correlation was found between possessing a child with jaundice and level of serum zinc (P = 0.63). There was a positive correlation between the levels of direct bilirubin and serum zinc (P = 0.72). Similar results were observed for the correlation between zinc level and hospitalization (P = 0.53). Also, there was no significant relationship among serum levels of Na, blood urea nitrogen (BUN), creatinine (Cr), white blood cell (WBC), platelet, hematocrit (Hct) and serum zinc level (P > 0.05).
Based on statistical results of Kolmogorov-Smirnov test, distribution of serum zinc levels in the control group was normal (P = 0.40) but it was not normal in the case group (P = 0.006). Mean value of serum zinc level was 928.81 ± 247.61 μmol/L in all neonates. The means of zinc level in the control and case groups were 1024.74 ± 245.17, and 841.42 ± 211.99 μmol/L, respectively (P < 0.001) (Figure 2). Q-variance analysis showed that the difference of zinc level was not because of older age of the subjects in the case group and that age was not a interventional factor in the level of zinc serum and this difference could be due to jaundice (P = 0.47).
5. Discussion
The current study results demonstrated that the serum zinc level of the neonates with jaundice was lower than that of the ones without jaundice. Zinc deficiency in pregnant women causes numerous complications for the fetus during pregnancy, such as structural malformations, intrauterine growth retardation (IUGR), premature birth, and SGA in different animal species and human. It is estimated that approximately 50% of women of childbearing age suffer from zinc deficiency. Studies found a relationship among low maternal serum zinc levels, low transferred zinc to the fetus and increase risk of developmental defects. Zinc plays both the structural and enzymatic roles in many proteins. A part of teratogenic effects of zinc deficiency can be due to the changes in the activity of proteins in the embryo (11).
The level of serum zinc increases in the embryo during the third trimester and this accumulation can be especially in the fetal liver. Increased level of fetal metallothionein is also observed. The cause of these changes is still unclear. It may be useful administration of zinc during pregnancy for growth and maturation of the immune system. Congenital abnormalities could result from zinc deficiency (12). There was a significant relationship between maternal serum zinc levels and the incidence of low birth weight (13).
The current study findings showed no correlation between modes of delivery and neonatal zinc level. Past studies show that epidural or spinal anesthesia before cesarean has fewer side effects than other methods. However, general anesthesia is considered as a risk factor for jaundice (14). Based on the findings of another study, there is no relationship between the type of delivery and the severity of jaundice in newborns (15). No relationship was observed between the gender of infants and serum zinc levels. In another study correlation was observed between the level of the neonatal serum zinc and infants’ gender (2010). No association was found between the level of serum bilirubin and zinc in neonates with jaundice. In addition, there was no relationship between serum level of direct bilirubin and zinc. Previous findings showed an inverse relationship between the levels of unconjugated bilirubin and serum zinc (16). The major limitation of the current study was the sampling time in babies with icterus that was three days earlier than those without it. Another limitation was difficulty to follow up neonates and inaccessibility of neonates. The serum zinc level of infants with jaundice was lower than those of the healthy ones. It seems that zinc may have a protective effect in the incidence of neonatal jaundice. However, more evaluations are needed for better decision making.