1. Context
Health literacy consists of cognitive and social skills determining people’s motivation and capacity to obtain, understand, and use health information to inform appropriate health care decisions and behaviors (1). Health literacy can be considered a capacity that empowers people to make decisions related to their health (2, 3). Furthermore, Sorensen describes health literacy as an ability that helps individuals make health-related decisions in their everyday lives at home, at work, in the marketplace, and in the political domain (2).
Health literacy is reported to be associated with optimal disease management. Research has shown that increasing the level of health literacy among patients can be an effective tool to improve disease management, including adherence to treatment, which is one of the well-known predictors of medication effectiveness across all medical conditions (4-6). Health literacy can be used to improve clinical services delivery, community participation in health programs, health planning, public health education, and health policymaking (7). Hence, health literacy has been emphasized by the World Health Organization (WHO) as one of the most important determinants of health, which can play an important role in improving health services and reducing health inequalities (8, 9).
Inadequate health literacy is one of the main problems in both developed and developing countries (10). Individuals with inadequate health literacy have low self-management knowledge, resulting in poor adherence to treatment, undesirable health outcomes, and increased health costs; for example, poor health behaviors due to inadequate health literacy accounted for 7% - 17% of health expenditure in the USA (11). There is a relationship between the level of inadequate health literacy and difficulty in understanding one’s health status and increased mortality (12). For instance, Gazmararian et al. showed that health literacy was related to disease knowledge, in a way that people with inadequate health literacy had less information about their illness than well-educated ones (13).
In Iran, different rates have been reported for inadequate health literacy, ranging from 9.5 to 82.5 (14, 15). Based on the results of Tehrani Banihashemi et al.’s study, more than half of the population surveyed had an inadequate level of health literacy (16). Health literacy is recognized as one of the most important determinants of individuals’ health, and various studies have reported different findings. Given the strong association of health literacy with better healthcare outcomes, it is necessary for policymakers to design and implement initiatives to address the issue of inadequate health literacy; however, in order to achieve this goal, accurate statistics about the prevalence of health literacy in the target population is required by policymakers; therefore, this study aimed to estimate the prevalence of health literacy in the Iranian population.
2. Methods
2.1. Research Strategy
In this study, the health literacy of the Iranian population was examined by reviewing published articles in domestic and international journals without time limitations. The Iranian national databases of Scientific Information Database (SID), Medline, and Magiran and the international databases of Web of Science, Google Scholar, PubMed, and Scopus were used to search for studies on the health literacy of the Iranian community. The following keywords and their possible combinations were used in the search process: Health Literacy and Iran. The Persian equivalents of these words were used to search the Persian databases. The reference lists of the collected articles were also reviewed to access other related articles.
2.2. Study Selection and Data Extraction
Initially, the researchers collected all articles relevant to their topic of discussion by focusing on the main keywords. Then, the final articles were selected based on the inclusion and exclusion criteria. All the observational studies, conducted using standard instruments, were entered the analysis. Interventional studies, repeated studies, use of non-standard questionnaires, and lack of access to full-text articles were the main exclusion criteria. According to the inclusion and exclusion criteria, titles and abstracts of the articles were independently reviewed by two researchers. The related material was separated and the full texts of the selected articles were extracted. The methodological quality of articles was examined based on a validated tool, commonly used in the previous studies (17, 18). This tool assessed methodological quality in 5 domains: study design, comparison groups, study population, psychometric properties of the questionnaires used, and sample size; each domain was rated on a score of 0 - 3, with total scores ranging from 0 to 5 indicating low methodological quality, from 6 to 10 indicating moderate methodological quality, and above 10 indicating high methodological quality. Any disagreement between the two researchers was resolved by the corresponding author who was an expert in the meta-analysis. A data extraction tool was designed to summarize the characteristics of the studies: first author, year of publication, the location of the study, total sample size, target group, type of questionnaires used, the prevalence of health literacy was categorized into adequate, borderline, and inadequate.
2.3. Statistical Analysis
Since the prevalence rate has a binomial distribution, the variance of each study was calculated through a binomial distribution variance. Weighted mean was used to combine the prevalence rates in different studies and the weight assigned to each study was contrary to the variance of that specific study. To examine heterogeneity among the selected studies, The Cochran’s Q test and the I2 index were used; P < 0.1 and I2 index < 0.75 indicated significant heterogeneity. Heterogeneity was divided into three classes of less than 25% (low heterogeneity), 25% to 75% (moderate heterogeneity), and more than 75% (high heterogeneity). Based on the heterogeneity results, the random effects model was used to estimate the prevalence rate.
The subgroup analysis was used to examine the prevalence of health literacy by gender (male/female), target group (general population, pregnant women, older people, patients with diabetes, etc.), type of questionnaire (the S-TOFHLA, the TOFHLA, the HELIA, and the REALM). The subgroup analysis was also performed in 5 regions of Iran. According to a new classification system by Iran’s Ministry of Interior in 2014, Iran was divided into 5 regions based on such factors as adjacency, geographical location, and similarities. The secretariats of the regions 1 to 5 are located in Tehran, Isfahan, Tabriz, Kermanshah, and Mashhad, respectively. To investigate the effect of small studies and publication error, the Funnel plot was used based on the Egger’s regression test. The sensitivity analysis was used to determine the role of each study on the final results. The univariate analysis of variance was used to assess the relationship of health literacy prevalence with study publication year, sample size, and mean age of the study population. Data analysis was performed using STATA software (version 12).
The study was registered in the international prospective register of the systematic review (PROSPERO) with number CRD42018082316. This study was a systematic review and meta-analysis of published studies; therefore, obtaining ethics approval and informed consent was not necessary.
3. Results
In the initial search, 574 studies were identified, of which a total of 26 studies met the inclusion and exclusion criteria (Figure 1).
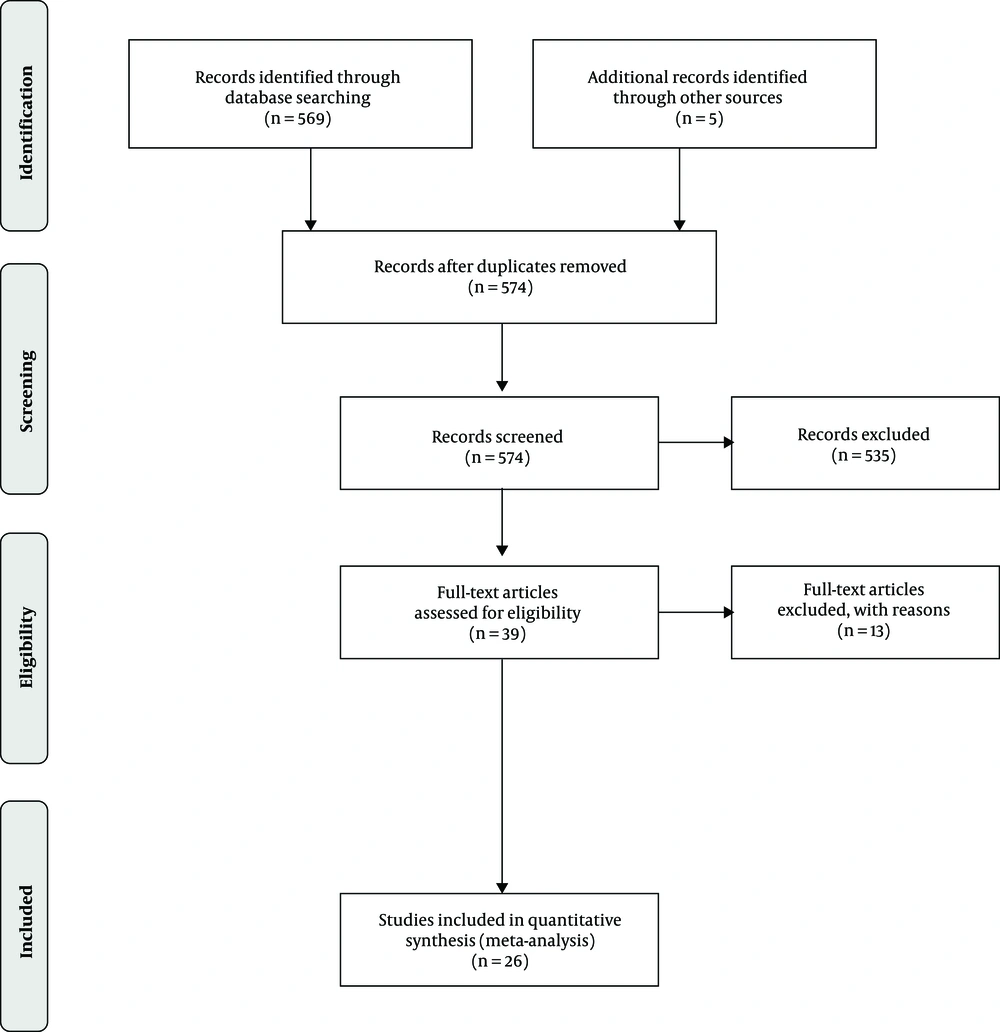
Figure 1.
Flowchart presentation of the selection and screening of the articles in accordance with the PRISMA guidelines.
The total sample size of the studies was 8932, with an average of 344 participants in each study. The largest and smallest sample sizes were for the studies by Tehrani Banihashemi et al. (1084) (16) and Amini and Mostafavizade (90) (15), respectively. The characteristics of the selected studies are presented in Table 1.
Table 1.
Summary of the Characteristic of the Included Studies
| First Author (Ref.) | Publication Year | Sample Size | Place | Target Group | Mean Age | Women % | Tool | Health Literacy (%) | ||
|---|---|---|---|---|---|---|---|---|---|---|
| Inadequate | Borderline | Adequate | ||||||||
| Baghaei (19) | 2017 | 400 | Urmia | Pregnant women | 27.3 ± 5.99 | 100 | S-TOFHLA | 24 | 25 | 51 |
| Safari Morad Abadi (20) | 2017 | 250 | Bandar Abbas | Pregnant women | 31.6 ± 7.45 | 100 | TOFHLA | 27.2 | 20.8 | 52 |
| Mahdavi (21) | 2017 | 500 | Tehran | Women | 41.2 ± 12.9 | 100 | TOFHLA | 48.6 | 24.4 | 27 |
| Charoghchian Khorasani (22) | 2017 | 162 | Chenaran | Patients with diabetes | 52.7 ± 11.8 | 80.2 | HELIA | 68.5 | 18.5 | 13 |
| Kamali (23) | 2017 | 100 | Nishabur | Pregnant women | - | 100 | S- TOFHLA | 45.8 | 35.6 | 18.6 |
| Bavandpour (24) | 2017 | 900 | Keranshah | General population | 32 ± 9.6 | 50 | TOFHLA | 19.6 | 57 | 23.4 |
| Fathi (25) | 2017 | 120 | Urmia | Elderly people | - | 100 | TOFHLA | 38.3 | 31.7 | 30 |
| Amini (15) | 2017 | 90 | Tehran | Librarians | 39.2 ± 7.7 | 74.7 | TOFHLA | 13.9 | 3.8 | 82.3 |
| Peyman (26) | 2016 | 120 | Mashhad | Pregnant women | 28.3 ± 0.3 | 100 | RELAM | 30 | 42.5 | 27.5 |
| Sheikh Sharafi (14) | 2016 | 105 | Mahabad | Heart failure | 60.7 ± 12.8 | 50.5 | HELIA | 28.6 | 61.9 | 9.5 |
| Zareban (27) | 2016 | 247 | Sistan and Baluchestan | Women | 26.2 ± 8.2 | 100 | HELIA | 33.2 | 34.4 | 32.4 |
| Darvishpour (28) | 2016 | 257 | Rasht | Hypertensive patinets | 55.7 ± 9.9 | 68.5 | S-TOFHLA | 28.4 | 30 | 41.6 |
| Khosravi (29) | 2016 | 250 | Bushehr | Patients | 42 ± 13.9 | 52 | TOFHLA | 22.8 | 38 | 39.2 |
| Rezaee Esfahrood (30) | 2016 | 432 | Yazd | Patients with diabetes | 55 ± 6.3 | 16.7 | TOFHLA | 59.3 | 18.5 | 22.2 |
| Sajjadi (31) | 2016 | 240 | Izeh | Women | 28.4 ± 6.3 | 100 | TOFHLA | 38.7 | 23.3 | 38 |
| Mahmoudi (32) | 2015 | 368 | Mashhad | Students | - | 54.7 | HELIA | 25 | 38.4 | 36.7 |
| Mohammadi (33) | 2015 | 407 | Tehran | Patients with diabetes | 55.8 ± 11.3 | 61.7 | TOFHLA | 70 | 11.8 | 18.2 |
| Izadirad (1) | 2015 | 400 | Sistan and Baluchestan | General population | - | 62.2 | HELIA | 34 | 34 | 32 |
| Mohseni (34) | 2015 | 200 | Kerman | Elderly people | - | 47.5 | TOFHLA | 52 | 31 | 17 |
| Seyedoshohadaee (35) | 2015 | 200 | Tehran | Patients with diabetes | 51.8 ± 8.8 | 35 | TOFHLA | 24 | 34 | 42 |
| Qobadi (36) | 2014 | 204 | Tehran | Patients undergoing hemodialysis | 50.9 ± 10.9 | 41.2 | S-TOFHLA | 25 | 9.8 | 65.2 |
| Kooshyar (37) | 2014 | 300 | Mashhad | Elderly people | 64.9 ± 5.2 | 65.7 | S-TOFHLA | 70 | 14.5 | 15.5 |
| Sharifirad (38) | 2014 | 354 | Isfahan | Elderly people | 67 ± 6.9 | 43 | TOFHLA | 79.6 | 11.6 | 8.8 |
| Nekoei-Moghadam (39) | 2013 | 1000 | Kerman | General population | 35.3 ± 12.2 | 62.4 | TOFHLA | 4.8 | 53.8 | 41.4 |
| Ghanbari (40) | 2012 | 240 | Tehran | Pregnant women | 27.7 ± 5.1 | 100 | TOFHLA | 30 | 24.6 | 45.4 |
| Tehrani Banihashemi (16) | 2007 | 1086 | National survey | General population | 38.1 ± 15.2 | 61.4 | TOFHLA | 56.6 | 15.3 | 28.1 |
Abbreviations: HELIA, health literacy for Iranian adults; S-TOFHLA, short-test of functional health literacy in adults; TOFHLA, test of functional health literacy in adults.
The overall prevalence of inadequate, borderline, and adequate health literacy was 38% (95% CI: 28 - 48), 29% (95% CI: 22 - 35), and 33% (95% CI: 27 - 38), respectively (Figure 2).
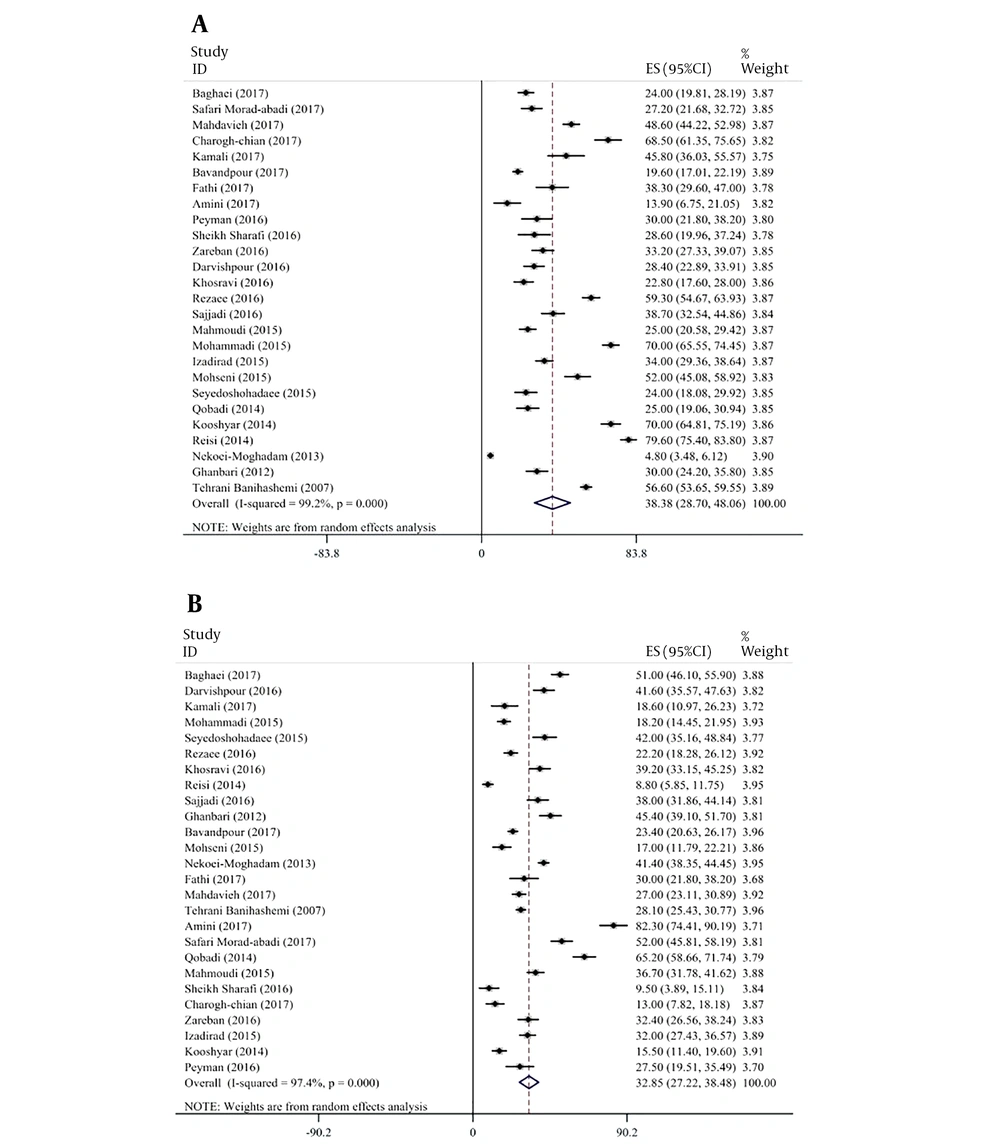
Figure 2.
Forest plot of the prevalence of inadequate (A) and adequate (B) health literacy in the Iranian population. The confidence interval of 95% for each study is shown by a horizontal line around the main mean, the dotted line in the middle represents the overall mean score, and the rhombus shows the confidence interval of the prevalence of health literacy.
The highest prevalence of adequate health literacy was in the region 1 (46.7%; 95% CI: 25.7 - 67.7%); whereas the highest prevalence of inadequate health literacy was in the region 2 (43.2%; 95% CI: 4.8 - 81.6%). The findings by the target groups showed that older people (60.2%; 95% CI: 43.7 - 76.8%) and patients with diabetes (55.4%; 95% CI: 35.6 - 75.2%) had the highest levels of inadequate health literacy. The highest frequency of adequate health literacy was for the other groups (41.1%; 95% CI: 29.2 - 53.1%) and pregnant women (37.4%; 95% CI: 21.5 - 53.3%). In terms of gender, the reviewed studies were divided into two groups: those conducted with both women and men and those conducted only with women. The findings showed that the prevalence of adequate health literacy was higher in the studies conducted exclusively on women (34.7%; 95% CI: 26.3 - 43%) than those included both men and women (31.3%; 95% CI: 24.2 - 38.3%). The results based on instruments showed that the highest health literacy scores were on the S-TOFHLA (37.2%; 95% CI: 19.8 - 54.6) (Table 2).
Table 2.
Subgroup Analysis of the Prevalence of Health Literacy
| Groups | Health Literacy | Number of the Articles | Prevalence (%) | Confidence Interval 95% | Heterogeneity | ||||
|---|---|---|---|---|---|---|---|---|---|
| Inadequate | Borderline | Adequate | % | P | |||||
| Regiona | 1 | * | 6 | 35.3 | 18 - 52.6 | 98.4 | 0.0001 | ||
| * | 17.8 | 9.7 - 25.8 | 95.4 | 0.0001 | |||||
| * | 46.7 | 25.7 - 67.7 | 98.5 | 0.0001 | |||||
| 2 | * | 3 | 43.2 | 4.8 - 81.6 | 99.4 | 0.0001 | |||
| * | 23.3 | 8.7 - 37.8 | 96.5 | 0.0001 | |||||
| * | 33.2 | 4.8 - 61.6 | 99 | 0.0001 | |||||
| 3 | * | 4 | 28.9 | 23.5 - 34.4 | 65.8 | 0.033 | |||
| * | 36.6 | 23.5 - 49.7 | 94 | 0.0001 | |||||
| * | 33 | 13.6 - 52.5 | 97.6 | 0.0001 | |||||
| 4 | * | 2 | 28.9 | 10.2 - 47.6 | 98.4 | 0.0001 | |||
| * | 31.8 | 3.2 - 60.4 | 99.6 | 0.0001 | |||||
| * | 29.2 | 22.9 - 35.4 | 89.7 | 0.0001 | |||||
| 5 | * | 10 | 42.2 | 24 - 60.3 | 99.4 | 0.0001 | |||
| * | 32 | 22.3 - 41.8 | 97.4 | 0.0001 | |||||
| * | 25.6 | 18.7 - 32.6 | 95.3 | 0.0001 | |||||
| Target group | General population | * | 4 | 28.7 | 4.8 - 52.6 | 99.7 | 0.0001 | ||
| * | 40.2 | 17.3 - 62.6 | 99.5 | 0.0001 | |||||
| * | 31.2 | 23.2 - 39.1 | 96.1 | 0.0001 | |||||
| Elderly people | * | 4 | 60.2 | 43.7 - 76.8 | 96.8 | 0.0001 | |||
| * | 21.2 | 12.3 - 30.9 | 92.8 | 0.0001 | |||||
| * | 17 | 9.9 - 24.1 | 89.3 | 0.0001 | |||||
| Pregnant women | * | 5 | 30.7 | 23.2 - 38.3 | 76.5 | 0.002 | |||
| * | 30.1 | 21.6 - 38.6 | 81.8 | 0.0001 | |||||
| * | 37.4 | 21.5 - 53.3 | 94.5 | 0.0001 | |||||
| Patients with diabetes | * | 4 | 55.4 | 35.6 - 75.2 | 98.2 | 0.0001 | |||
| * | 20.3 | 12.4 - 28.2 | 91.9 | 0.0001 | |||||
| * | 23.5 | 14.1 - 32.9 | 93.7 | 0.0001 | |||||
| Others | * | 9 | 29.4 | 22.4 - 36.5 | 98.2 | 0.0001 | |||
| * | 29 | 19.1 - 38.9 | 97.1 | 0.0001 | |||||
| * | 41.1 | 29.2 - 53.1 | 97.5 | 0.0001 | |||||
| Gender | Men and women | * | 17 | 40.1 | 26.7 - 53.4 | 99.3 | 0.0001 | ||
| * | 28.2 | 19.6 - 36.8 | 98.7 | 0.0001 | |||||
| * | 31.3 | 24.2 - 38.3 | 97.4 | 0.0001 | |||||
| Only women | * | 9 | 35.5 | 28.3 - 42.7 | 90.2 | 0.0001 | |||
| * | 28.7 | 24.3 - 33.1 | 78.4 | 0.0001 | |||||
| * | 34.7 | 36.3 - 38.3 | 93.3 | 0.0001 | |||||
| Scale | S-TOFHLA | * | 3 | 31.7 | 21.7 - 41.7 | 87.7 | 0.0001 | ||
| * | 29 | 23.5 - 34.5 | 59.3 | 0.086 | |||||
| * | 37.2 | 19.8 - 54.6 | 95.9 | 0.0001 | |||||
| TOFHLA | * | 15 | 39.6 | 24.7 - 54.5 | 99.5 | 0.0001 | |||
| * | 26.7 | 17.3 - 36.1 | 98.8 | 0.0001 | |||||
| * | 33.2 | 25.9 - 40.6 | 97.7 | 0.0001 | |||||
| HELIA | * | 7 | 40.6 | 26 - 55.1 | 97.8 | 0.0001 | |||
| * | 29.8 | 18.7 - 40.9 | 97 | 0.0001 | |||||
| * | 29.1 | 16.6 - 41.6 | 97.6 | 0.0001 | |||||
| REALM | * | 1 | 30 | 21.8 - 38.2 | - | - | |||
| * | 42.5 | 18.7 - 40.9 | - | - | |||||
| * | 27.5 | 19.5 - 35.4 | - | - | |||||
a Region 1, Alborz, Tehran, Qazvin, Mazandaran, Semnan, Golestan, and Ghom; region 2, Esfahan, Fars, Bushehr, Hormozgan, Kohgiluyeh and Boyer-Ahmad, and Chaharmahal and Bakhtiari; region 3, West Azerbaijan, East Azerbaijan, Ardabil, Zanjan, Gilan, and Kurdistan; region 4, Kermanshah, Ilam, Lorestan, Hadaman, Markazi, and Khuzestan; region 5, Razavi Khorasan, North Khorasan, South Khorasan, Kerman, Yazd, and Sistan and Baluchestan.
The results of the meta-regression indicated that there was no significant association between the prevalence of inadequate, borderline, and adequate levels of health literacy with sample size and year of publication (Table 3). However, there was a significant association between participants’ age and inadequate health literacy (P = 0.008). In other words, inadequate health literacy showed an upward trend with participants’ age (Figure 3). The results of the sensitive analysis by different levels of health literacy (inadequate/ borderline/ adequate) showed that removal of no study led to a significant change in the estimation of the frequency of health literacy at any level. In other words, none of the studies alone had a significant impact on the results.
Table 3.
Univariate Meta-Regression of Health Literacy in Iran
| Variable/Health Literacy | Coefficient | Standard Error | t | P Value | Confidence Interval 95% |
|---|---|---|---|---|---|
| Mean age of samples | |||||
| Inadequate | 0.908 | 0.294 | 3.08 | 0.006 | 0.29 - 1.52 |
| Borderline | -0.289 | -0.264 | -1.10 | 0.286 | (-0.84) - 0.26 |
| Adequate | -0.62 | 0.28 | -2.23 | 0.038 | (-0.038) - (-1.21) |
| Sample size | |||||
| Inadequate | -0.003 | 0.014 | -0.24 | 0.810 | (-0.034) - 0.026 |
| Borderline | 0.01 | 0.01 | 0.94 | 0.357 | (-0.012) - 0.032 |
| Adequate | -0.006 | 0.013 | -0.46 | 0.650 | (-0.032) - 0.2 |
| Publication year | |||||
| Inadequate | -1.56 | 1.79 | -0.87 | 0.391 | (-5.27) - 2.13 |
| Borderline | 1.19 | 1.34 | 0.89 | 0.384 | (-1.58) - 3.96 |
| Adequate | 0.343 | -1.61 | 0.21 | 0.833 | (-2.98) - 3.66 |
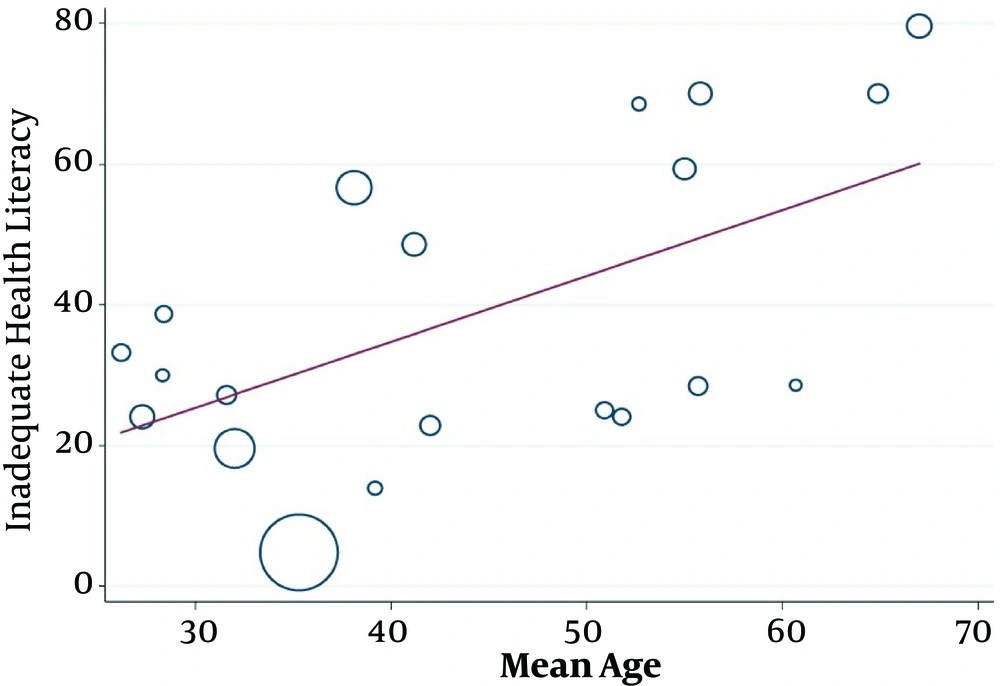
Figure 3.
Meta-regression of inadequate health literacy based on participants’ mean age
The findings also showed that there was no significant publication bias for any level of health literacy: inadequate (P = 519), borderline (P = 0.093), and adequate (P = 0.154).
4. Discussion
This was a systematic review and meta-analysis on the published studies on health literacy among the Iranian population. According to the results, the lowest health literacy rates were reported by the studies conducted in the region 2 of Iran and the studies with older adults, patients with diabetes, and male participants, while the highest health literacy rates were reported by the studies conducted in the region 1 of Iran and the studies with pregnant women and female participants. Among the studied regions of Iran, region 1 had the highest health literacy rates. This finding may be attributed to regional differences in cultural norms, interpersonal relationships, and values. In fact, good health literacy results from a dynamic cycle, which may be different in various societies. For example, there are differences between developed and developing counties in the health literacy level. In addition, the cultural competence of healthcare providers has a major role in improving the health literacy of every society (41).
On the other hand, such factors as income and education status influence the level of health literacy in the society, because previous studies have shown that societies with financial and social limitations are more likely to have also limitations in health literacy (42). Therefore, it is expected that financial and social differences among different regions can lead to differences in health literacy rates and this difference is even seen between rural and urban populations (43).
According to the results, older people had the lowest level of health literacy. Consistent with this finding, studies conducted in other countries have also shown that older people are one of the populations known for having health literacy limitations (42). Limited health literacy in older adults may result from their limited access to the necessary resources and their low education (mainly below high school) (44). On the other hand, cognitive abilities requiring information processing skills are reduced with age, and as people get older, it becomes more difficult for them to complete tasks requiring information processing skills, and completing these tasks takes a longer time for them. In addition, physical limitations such as hearing or vision loss reduce older people’s ability to listen to the educational information provided by the healthcare professionals or to read them in the published materials, and this can affect their health literacy. In line with this, a review study and meta-analysis by Kobayashi et al. on the studies conducted with older adults showed a relationship between low health literacy and lower ability to understand medical terms (45).
The difference in older adults’ health literacy rates in different studies may be related to the use of different outcome measures and data collection instruments. For example, some studies had measured older people’s health literacy in terms of reading, writing, and analyzing medical information using the test of functional health literacy in adults (TOFHILA) or its short form (S-TOFHILA), while others had assessed older people’s literacy in understanding medical terms using the health literacy measurement tools (REALM). On the other hand, a previous review study showed that screening older adults’ health literacy requires standard and reliable tools (46).
Our results also showed that patients with diabetes had low health literacy. Consistent with this finding, previous studies have also shown that patients with diabetes have lower health literacy compared to other groups of patients (47). Health literacy in patients with diabetes is related to their knowledge of diabetes, self-efficacy, self-care behaviors, and controlling blood sugar level (48). In addition, diabetes management requires some skills, including cultural and ethnic knowledge, hearing literacy, and the ability to read and write (49). Diabetes management also requires different components of health literacy, such as practical, relational, and critical health literacy, and the absence of any of these components can affect the patients’ health literacy.
In our meta-analysis, 38% of pregnant women had adequate health literacy. Pregnancy is one of the most important stages of a woman’s life and can have a major impact on the health of the mother and the baby, thus improving women’s health literacy is considered a priority (50). In a study by Kilfoyle et al. (51), 9% to 78% (M = 46%) of pregnant women had inadequate health literacy. High health literacy in pregnant women could be attributed to attending training classes before, during, or after pregnancy in healthcare centers or their efforts to get the necessary information through the media or their friends and family members in order to maintain the health of themselves and their babies. Differences in the health literacy of pregnant women in different societies can be due to cultural differences or different levels of access to healthcare services. The results also indicated that women had higher health literacy than men. This finding agrees with those of other cultural studies (52). This difference between men and women in terms of health literacy can be due to the important role of women in the health of the family and their higher knowledge about health care processes.
Bertakis et al. believe that women tend to search for health-related subjects and use health care services more than men (53). In addition, women may have different roles in different cultures. In fact, in the cultural context of countries like Iran, women often are the main care providers in the family and also in the health care systems in the society on a broader level, while men are more responsible for supporting their families financially. Therefore, higher health literacy in women can be due to their role as a health care provider for their family and their more contact with the health care and medical systems in society. Previous studies have also shown that because of providing health care for children and patient members of the family, women tend to have adequate health literacy (54). One of the strengths of our meta-analysis was that it was the first meta-analysis in which the health literacy of the Iranian population was comprehensively examined. Although the analyzed studies included the validity and reliability of the TOFHLA and the S-TOFHLA, they had not examined the psychometric properties of the two scales. Only the studies using the HELIA had examined health literacy based on the Iranian population because this questionnaire had been validated in the Iranian population. Therefore, some of the differences in the findings could be due to the different instruments used in the studies.
5. Conclusions
The highest inadequate health literacy rates are reported by the studies conducted in the region 2 of Iran and the studies with older people and patients with diabetes. Providing necessary training on health topics for these groups can be useful in improving their health.