
1. Background
Infantile colic (IC) is one of the most stressful conditions for parents, characterized by intense and persistent crying that begins suddenly and without a clear cause (1). These episodes are often accompanied by increased muscle tension, facial redness, leg flexion toward the abdomen, and abdominal bloating, typically resolving by three months of age (2, 3). The incidence of IC varies widely, with rates ranging from 17 - 25% during the first six weeks of life (4). Overall, the global prevalence of IC is estimated at approximately 20% (5). The classic definition of infant colic was introduced by Wessel in 1954, describing it as crying or fussing for more than three hours a day, more than three days a week, for over three weeks. The ROME IV criteria, established in 2016 for clinical purposes, define IC as follows: An infant younger than five months of age when symptoms begin and end; recurrent and prolonged periods of crying, fussing, or irritability reported by caregivers, which occur without an obvious cause and cannot be prevented or resolved by caregivers; and no evidence of failure to thrive, fever, or illness (3).
The etiology of colic remains unclear, but for better conceptualization, proposed causes are categorized as digestive and non-digestive. Non-digestive causes include feeding methods, changes in parent-infant interaction, and immaturity of the central nervous system. Digestive causes include progressive lactose intolerance, altered gut microbiota, immaturity of the enteric nervous system, increased motilin receptor expression, or hypersensitivity to cow’s milk (4). Therefore, changes in intestinal microflora are considered one of the potential digestive causes of colic. Probiotics are live microorganisms that can beneficially alter the host’s gut microbiota (6). Evidence suggests that colicky infants exhibit a different gut microbiota composition than healthy infants, including higher levels of anaerobic bacteria and lower concentrations of Lactobacillus (7). These infants often show greater microbial diversity, which probiotics may help normalize, promoting a healthier intestinal flora (8).
Multiple therapeutic approaches for IC have been proposed. However, despite decades of research, effective treatments remain limited. Broadly, these approaches are classified into parental behavioral strategies, dietary supplements, pharmacological interventions, and manipulative therapies (9). Given the observed alterations in gut microbiota among colicky infants, probiotic supplementation as a dietary approach is gaining interest. Fecal calprotectin is a well-established non-invasive marker of gut inflammation. Several studies have reported elevated fecal calprotectin levels in infants with colic (8, 10, 11). Additionally, IC has been linked to increased maternal depressive symptoms and lower maternal quality of life (12, 13).
This randomized, placebo-controlled, parallel-group clinical trial was therefore designed to evaluate the preventive effects of synbiotic supplementation on the incidence of infant colic, maternal quality of life, and infant fecal calprotectin levels.
2. Methods
2.1. Participants
This parallel, randomized, triple-blind, placebo-controlled clinical trial included healthy term infants born between 37 and 42 weeks of gestation, with a birth weight over 2000 grams and age under 10 days at the time of enrollment (14). Infants who had received antibiotics or probiotics before the study, required initial hospitalization or re-hospitalization, or had congenital, immune, metabolic, or developmental disorders were excluded. Additional exclusion criteria included any component of the synbiotic or placebo syrup, any known abdominal pathology, and maternal probiotic use. The sample size was calculated based on standard formulas for parallel clinical trials, assuming 5% type I error, 80% power, and anticipating a 30% dropout rate, resulting in 51 infants per group (15). The study was registered on the Iranian Registry of Clinical Trials website (identifier No.: IRCT20230123057193N2).
Also, this study has the approval of the moral principles and national norms and standards of Iran for conducting medical research. Ethics Approval Reference a local ethics committee or institutional review board (IRB): IR.TUMS.MEDICINE.REC.1402.692. All participants or their parents or legal guardians of participants signed the consent form.
2.2. Study Design
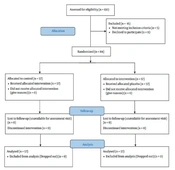
The trial was conducted according to the Declaration of Helsinki (1964). A total of 104 infants were enrolled. Informed written consent was obtained from all parents. Before group allocation, baseline anthropometric measurements (weight, length, and head circumference) were recorded. Individual and parental characteristics were collected via structured face-to-face interviews. The maternal quality of life questionnaire was completed at baseline and the end of the intervention. Additionally, mothers completed the Barr Children's Behavior Scale throughout the study to assess colicky behavior. To measure fecal calprotectin levels, at least 5 grams of stool were collected from each infant at baseline and after the 8-week intervention. Participants were randomized into intervention and placebo groups using a block randomization method. Each block included two infants matched for weight category (≤ 2500 g or > 2500 g) and feeding type (exclusive breastfeeding or not). The random sequence was generated using the Random Allocation Software (RAS) (16). A consolidated standards of reporting trials (CONSORT) diagram illustrating participant flow, study design, and dropouts is presented in Figure 1.
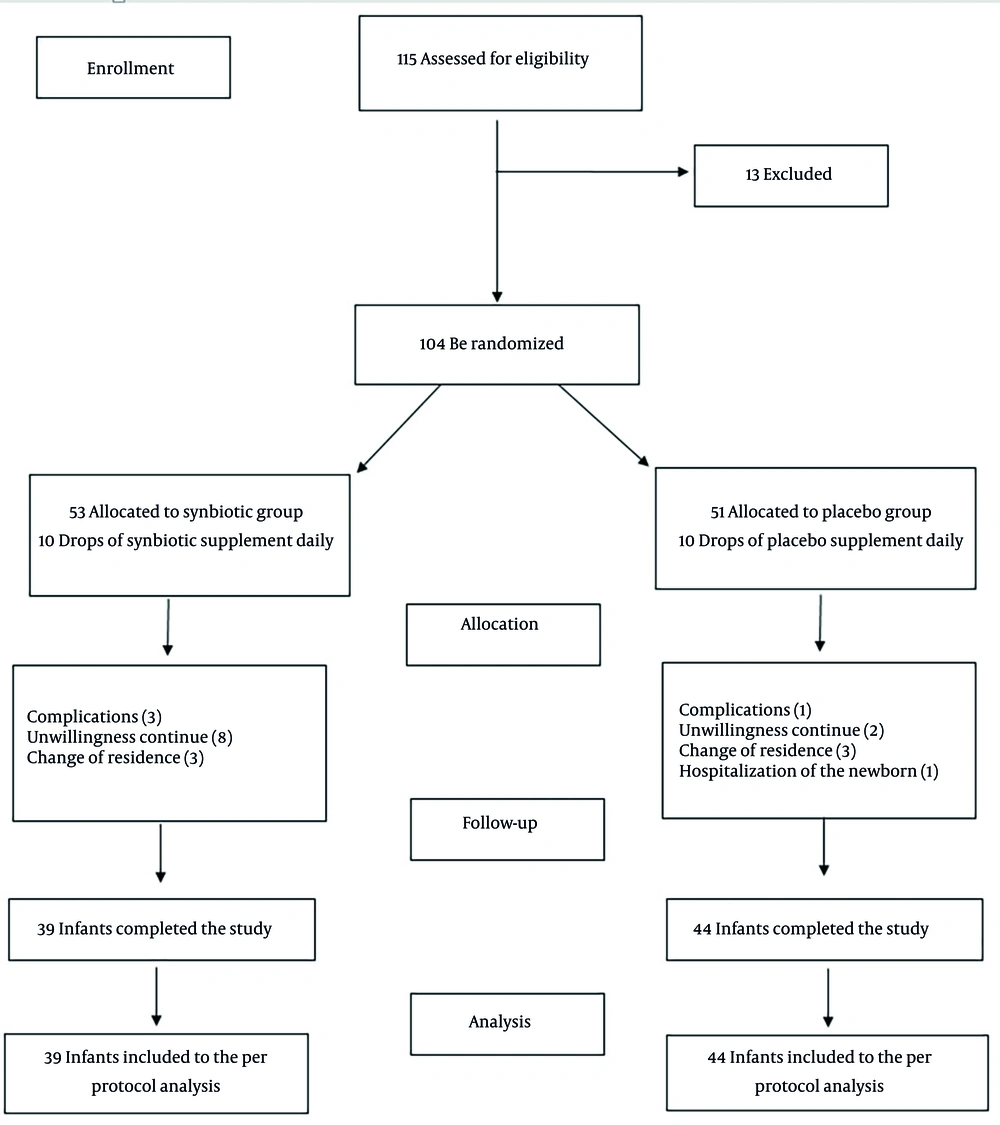
Figure 1.
Flow diagram of the study participants
2.3. Intervention
All parents, researchers, pediatricians, statisticians, and laboratory personnel were blinded to group allocation. Based on prior studies demonstrating preventive effects on colic, infants in the intervention group received 10 drops (26 mg) daily of a synbiotic supplement for 8 weeks (15). The supplement contained Lactobacillus reuteri, Lactobacillus rhamnosus, and Bifidobacterium infantis [total dose: 10¹⁰ colony-forming units (CFU)], along with a prebiotic (fructooligosaccharide). The placebo, matched in appearance, color, texture, and smell, contained sunflower oil, medium-chain triglyceride (MCT) oil, silicon dioxide, and orange flavoring. Both supplements were manufactured and quality-controlled by ZISTTAKHMIR Co., Tehran, Iran. Bottles were coded as A and B and remained blinded to the investigators throughout the study. Parents received the supplements during two visits — at baseline and week 4. To monitor adherence, a daily checklist was provided for parents to record consumption. Weekly reminder messages were also sent. Parents were asked to refrigerate the supplements and return the empty bottles at each follow-up visit. A pediatric specialist evaluated the infants biweekly to assess for any adverse effects.
In this study, we investigated the effects of synbiotic supplementation on a series of outcomes, which will be explained in more detail below.
2.4. Outcomes
The primary outcomes of this clinical trial were the incidence of IC and maternal quality of life. Secondary outcomes included the severity of colic and fecal calprotectin levels. Anthropometric measurements were also performed. All outcomes were assessed at baseline and the end of the trial.
2.5. Anthropometric Assessment
Anthropometric indices including body weight, length, and head circumference were measured at baseline and the end of the study. Body weight was recorded using a calibrated electronic scale (Zenithmed, Switzerland) to the nearest 0.1 kg, with infants wearing light clothing and no shoes. Length was measured to the nearest 0.1 cm with the infant in a supine position on a rigid measuring board (Seca, Germany), using a fixed headpiece and movable foot piece. Head circumference was measured to the nearest 0.1 cm using a non-stretchable plastic tape at the largest occipital-frontal diameter.
2.6. Calprotectin Level Measurement
Fecal samples were collected from all participants at baseline and after the intervention period. Samples were either collected by parents at home or during clinic visits, with assistance from a nurse if needed. Samples were transported to the laboratory within 24 hours and immediately stored at –80°C. Calprotectin levels were measured using a commercially available enzyme-linked immunosorbent assay (ELISA) kit according to protocol after stool preparation (Pishtaz Teb, Iran). According to this kit, a reported calprotectin level above 200 µg/g indicates the presence of significant inflammation in the gastrointestinal (GI) tract.
2.7. Maternal Quality of Life
Maternal quality of life was assessed using the short form health survey (36 items; SF-36) questionnaire, which consists of 36 items covering eight domains: Physical functioning, role limitations due to physical health, role limitations due to emotional problems, vitality, mental health, social functioning, bodily pain, and general health perceptions. Scores for each domain range from 0 to 100, with higher scores indicating better quality of life (17).
2.8. Colicky Behavior Assessment
Infant colic behavior was evaluated using the validated Barr Child Behavior Scale (18). This tool tracks the duration and nature of infant behavior over 24 hours, divided into four time periods: Midnight, morning, afternoon, and evening. Each period is subdivided into hourly intervals, further divided into five-minute segments. Parents recorded the infant’s behavior — including sleeping, feeding, quiet alertness, crying, and sucking — using specific symbols. The total duration of each behavior and the number of daily bowel movements were calculated and recorded.
2.9. Statistical Analysis
Statistical analyses were conducted using Statistical Package for the Social Sciences (SPSS) version 24. Data normality was assessed via histograms and the Kolmogorov-Smirnov test. If data were non-normally distributed, logarithmic transformation was applied. Results were expressed as (geometric) mean ± standard deviation. Independent samples t-tests were used to compare demographic characteristics, maternal quality of life scores, calprotectin levels, and colic-related behaviors between the intervention and placebo groups; also, independent samples t-tests were employed to assess effects of the synbiotic intervention on outcome variables. Analysis of covariance (ANCOVA) was used to compare post-intervention outcomes between the synbiotic and placebo groups, adjusting for baseline values and sibling history of colic as covariates. A per protocol (PP) approach was adopted. Logistic regression was used to estimate the odds of developing colic between groups after the intervention. A P-value of < 0.05 was considered statistically significant.
3. Results
The trial was conducted between May 2024 and May 2025. A total of 104 infants were enrolled, and 83 completed the 8-week trial (44 in the placebo group and 39 in the synbiotic group). In the synbiotic group, 14 infants withdrew: Three due to complications (including GI symptoms), 3 due to change of parents’ residence, and 8 for personal reasons of mothers. In the placebo group, 7 infants withdrew: One due to complications (including GI symptoms), 3 due to migration, 1 due to hospitalization, and 2 for personal reasons. However, all 104 participants were included in the PP analysis (Figure 1). Adherence was defined as consumption of ≥ 80% of the assigned supplement (synbiotic or placebo). All remaining participants met the study protocol and had good compliance until the end of the trial.
There were no significant differences between the two groups in demographic characteristics, except for a history of colic in a previous child (P = 0.02; Table 1). Similarly, no significant differences were found in anthropometric indices between the groups at baseline.
Table 1.
General Characteristics of Study Population at the Baseline a
| Variables | Synbiotic Group (n = 39) | Placebo Group (n = 44) | P-Value b |
|---|---|---|---|
| Mother's age (y) | 33.87 ± 4.23 | 33.04 ± 5.20 | 0.43 |
| Employment status/housewife | 66.7 | 81.8 | 0.11 |
| Education/university | 84.6 | 77.3 | 0.39 |
| Delivery/natural | 23.1 | 29.5 | 0.50 |
| Gender/boy | 48.7 | 43.2 | 0.61 |
| Gestational age (wk) | 38.22 ± 0.98 | 38.32 ± 0.90 | 0.63 |
| Age of the newborn at first visit (d) | 5.02 ± 2.35 | 5.04 ± 2.44 | 0.97 |
| Height at birth (cm) | 48.83 ± 2.21 | 48.82 ± 1.71 | 0.99 |
| Weight at birth (g) | 3183.92 ± 415.74 | 3096.25 ± 407.43 | 0.33 |
| Birth weight (g) | 0.93 | ||
| < 2500 | 2.6 | 2.3 | |
| ≥ 2500 | 97.4 | 97.7 | |
| Birth order | 0.70 | ||
| First | 28.2 | 29.5 | |
| Second | 51.3 | 56.8 | |
| Third and more | 20.5 | 13.6 | |
| History of colic in previous child/yes | 82.1 | 59.1 | 0.02 |
| Type of feeding | 0.10 | ||
| Breast milk | 58.5 | 64.7 | |
| Formula milk | 1.9 | 9.8 | |
| Complementary formula milk | 39.6 | 33.04 ± 5.20 |
a Values are expressed as mean ± SD or percent.
b P-values were obtained from independent Student’s t-test or the χ2 test, where appropriate.
Table 2 presents maternal quality of life over the 8-week intervention period. At baseline, the only statistically significant difference was observed in the general health domain, with higher scores in the synbiotic group (P = 0.01). After adjusting for baseline values and history of colic in siblings, no statistically significant differences were observed between the groups in any quality-of-life domains at the end of the study, except for the pain domain (P = 0.04), which was significantly lower in the synbiotic group, indicating reduced maternal pain.
Table 2.
Maternal Quality of Life at the Baseline and After 8 Weeks Trial a
| Maternal Quality of Life | Study Baseline | End of Trial | Effect Size (95% CI) | |||||
|---|---|---|---|---|---|---|---|---|
| Synbiotic | Placebo | P b | Synbiotic | Placebo | P b | P c | ||
| Physical function | 0.003 (-7.77, 4.71) | |||||||
| Crude | 33.00 ± 23.68 | 25.65 ± 15.89 | 0.09 | 24.21 ± 20.41 | 19.20 ± 13.22 | 0.18 | ||
| Adjusted | 22.37 ± 13.92 | 20.84 ± 13.86 | 0.62 | |||||
| Role physical | 0.01 (-19.72, 7.35) | |||||||
| Crude | 72.05 ± 27.43 | 70.00 ± 28.90 | 0.74 | 65.80 ± 32.26 | 60.00 ± 29.96 | 0.39 | ||
| Adjusted | 66.00 ± 30.41 | 59.82 ± 30.38 | 0.36 | |||||
| Body pain | 0.05 (0.17, 17.61) | |||||||
| Crude | 41.89 ± 22.00 | 44.61 ± 16.77 | 0.52 | 55.20 ± 22.38 | 64.81 ± 19.94 | 0.03 | ||
| Adjusted | 55.92 ± 19.54 | 64.81 ± 19.50 | 0.04 | |||||
| General health | 0.001 (-3.98, 5.61) | |||||||
| Crude | 40.02 ± 11.34 | 34.56 ± 8.13 | 0.01 | 38.67 ± 10.48 | 37.06 ± 10.54 | 0.50 | ||
| Adjusted | 37.38 ± 10.61 | 38.20 ± 10.54 | 0.73 | |||||
| Vitality | 0.006 (-3.21, 6.82) | |||||||
| Crude | 58.51 ± 18.29 | 52.15 ± 16.37 | 0.09 | 48.44 ± 17.96 | 46.27 ± 14.08 | 0.54 | ||
| Adjusted | 46.34 ± 11.17 | 48.14 ± 11.14 | 0.47 | |||||
| Social function | 0.01 (-2.86, 10.76) | |||||||
| Crude | 55.20 ± 22.18 | 61.43 ± 18.82 | 0.17 | 56.90 ± 20.53 | 65.42 ± 17.21 | 0.04 | ||
| Adjusted | 59.32 ± 15.23 | 63.27 ± 15.19 | 0.25 | |||||
| Mental health | 0.001 (-5.95, 4.54) | |||||||
| Crude | 41.76 ± 20.23 | 36.59 ± 16.57 | 0.20 | 39.82 ± 19.17 | 35.47 ± 15.22 | 0.25 | ||
| Adjusted | 37.89 ± 11.74 | 37.19 ± 11.74 | 0.79 | |||||
| Role emotional | 0.003 (17.52, 10.26) | |||||||
| Crude | 68.05 ± 37.54 | 61.86 ± 29.40 | 0.40 | 53.77 ± 35.55 | 44.00 ± 38.32 | 0.23 | ||
| Adjusted | 50.51 ± 31.16 | 46.89 ± 31.10 | 0.60 | |||||
a Values are expressed as mean ± SD.
b Obtained by Independent sample t-test.
c Obtained by ANCOVA/adjusting for baseline values and history of colic.
Fecal calprotectin levels at baseline and after the 8-week intervention are also presented in Table 3. At baseline, there was a borderline significant difference between the two groups (P = 0.05), with higher levels in the synbiotic group. After adjusting for baseline values and colic history, both groups experienced a reduction in calprotectin levels; however, this decrease was not statistically significant (P > 0.05).
Table 3.
Fecal Calprotectin Levels at Baseline and After 8 Weeks Trial a
| Variable | Study Baseline | End of Trial | Effect Size (95% CI) | |||||
|---|---|---|---|---|---|---|---|---|
| Synbiotic | Placebo | P b | Synbiotic | Placebo | P b | P c | ||
| Fecal calprotectin | 0.000 (-169.99, 153.64) | |||||||
| Crude | 134.19 ± 60.98 | 110.79 ± 49.75 | 0.05 | 124.74 ± 49.12 | 107.73 ± 51.12 | 0.12 | ||
| Adjusted | 116.16 ± 36.18 | 115.34 ± 36.08 | 0.92 | |||||
a Values are expressed as mean ± SD.
b Obtained by Independent sample t-test.
c Obtained by ANCOVA/adjusting for baseline values and history of colic.
Colic-related behaviors at baseline and the end of the intervention are summarized in Table 4. No significant differences were found between the two groups in terms of sleep duration, crying and fussing time, crying frequency less than 1 minute, and fecal frequency (P > 0.05).
Table 4.
Colic-Related Behaviors at Baseline and After 8 Weeks Trial a
| Colic-Related Behaviors | Study Baseline | End of Trial | Effect Size (95% CI) | |||||
|---|---|---|---|---|---|---|---|---|
| Synbiotic | Placebo | P b | Synbiotic | Placebo | P b | P c | ||
| Sleep duration | 0.000 (-29.85, 32.20) | |||||||
| Crude | 149.22 ± 746.68 | 124.08 ± 707.14 | 0.19 | 704.27 ± 79.75 | 706.25 ± 68.77 | 0.90 | ||
| Adjusted | 704.69 ± 69.56 | 705.87 ± 69.38 | 0.94 | |||||
| Crying time | 0.01 (-26.34, 10.05) | |||||||
| Crude | 41.02 ± 81.18 | 46.67 ± 91.64 | 0.28 | 81.86 ± 43.74 | 74.92 ± 40.25 | 0.45 | ||
| Adjusted | 82.50 ± 40.77 | 74.35 ± 40.72 | 0.37 | |||||
| Fussing time | 0.006 (-26.21, 12.94) | |||||||
| Crude | 67.89 ± 119.92 | 71.96 ± 135.45 | 0.31 | 111.98 ± 44.91 | 107.58 ± 42.52 | 0.64 | ||
| Adjusted | 113.17 ± 43.96 | 106.53 ± 43.84 | 0.50 | |||||
| Crying and fussing time | 0.01 (-48.57, 18.10) | |||||||
| Crude | 93.16 ± 201.10 | 93.29 ± 227.10 | 0.20 | 149.62 ± 73.04 | 152.63 ± 90.72 | 0.86 | ||
| Adjusted | 159.11 ± 74.62 | 143.88 ± 74.49 | 0.36 | |||||
| Crying frequency less than 1 minute | 0.000 (-1.03, 0.86) | |||||||
| Crude | 2.04 ± 5.23 | 2.30 ± 5.15 | 0.88 | 4.34 ± 1.92 | 4.36 ± 2.22 | 0.95 | ||
| Adjusted | 4.39 ± 2.12 | 4.31 ± 2.12 | 0.86 | |||||
| Fecal frequency | 0.005 (-1.03, 0.51) | |||||||
| Crude | 2.45 ± 5.66 | 2.39 ± 5.97 | 0.56 | 3.66 ± 1.93 | 3.35 ± 1.48 | 0.41 | ||
| Adjusted | 3.63 ± 1.68 | 3.38 ± 1.72 | 0.51 | |||||
a Values are expressed as mean ± SD.
b Obtained by Independent sample t-test.
c Obtained by ANCOVA/adjusting for baseline values and history of colic.
Clinically, the incidence of colic in the synbiotic group was approximately half of the placebo group at the end of the trial; however, this difference did not reach statistical significance (P = 0.12).
The incidence of colic in the synbiotic and placebo groups was analyzed using binary logistic regression across three models (Table 5). None of the models revealed a statistically significant association between synbiotic supplementation and the incidence of colic.
Table 5.
Comparison of Colic Incidence Between Synbiotic and Placebo Groups a
| Incidence of Colic | P-Value (95% CI) b |
|---|---|
| Crude | 0.43 (0.14, 1.28) |
| Model 1 | 0.42 (0.13, 1.28) |
| Model 2 | 0.39 (0.12, 1.23) |
| Model 3 | 0.39 (0.12, 1.26) |
a Model 1 was adjusted for a history of colic in a previous child (yes/no). Model 2 was further adjusted for maternal-related confounders, including mode of delivery (vaginal/cesarean) and infant feeding type (breastfeeding/formula/mixed). Model 3 was additionally adjusted for infant-related confounders, including infant sex (female/male) and birth weight (< 2500 g/≥ 2500 g).
b Binary logistic regression.
4. Discussion
This randomized, placebo-controlled clinical trial was conducted on healthy infants. Daily supplementation with 10¹⁰ CFU of a synbiotic supplement for 2 months led to a clinically meaningful reduction in the incidence of colic and maternal pain. The intervention also resulted in a reduction in fecal calprotectin levels, crying duration, and restlessness in infants; however, these changes did not reach statistical significance. Additionally, no significant effects were observed in infant growth parameters.
Our findings are consistent with previous clinical trials by some researchers, which investigated the preventive use of L. rhamnosus — a strain included in our synbiotic supplement — at a dose of 10⁹ CFU for 6 months and reported similar trends in reducing colic (19-21). Other studies evaluating probiotic supplementation for the prevention of colic have also demonstrated positive and significant outcomes (14, 22).
The discrepancy in findings across studies could be attributed to cultural differences in infant care practices, genetic variability, and methodological differences in colic assessment — since no gold standard for diagnosing colic exists, relying largely on physician assessment and parental reports. Variations in dosage, duration of intervention, probiotic strain(s), and inclusion/exclusion criteria further contribute to inconsistencies across clinical trials.
Regarding maternal quality of life, our findings align with previous research that observed no significant improvement in most SF-36 dimensions following synbiotic supplementation. However, this study reported improvements in mothers' social and physical functioning, suggesting potential positive impacts on maternal well-being (13). Mothers of colicky infants frequently report higher levels of frustration, anger, depressive symptoms, and social withdrawal, highlighting how colic can significantly impair maternal quality of life (12, 13, 15, 23).
Our study also mirrors some previous trials that failed to observe a statistically significant reduction in fecal calprotectin levels following synbiotic supplementation (11, 24), though other studies have reported significant decreases (8, 25). Disparities in outcomes may stem from differences in study populations, intervention duration, probiotic strain and dose, and laboratory assay methods. While our study noted a decrease in fecal calprotectin following supplementation, this reduction was not statistically significant. The observed decrease in fecal calprotectin levels in both groups likely reflects the normal maturation of the infant gut and immune system over time, rather than a specific effect of synbiotic supplementation (26).
Similarly, the effects of synbiotic supplementation on colic-related behaviors were comparable to findings from other studies reporting no significant improvements in crying time or restlessness (11, 19, 24, 27-29). In contrast, some clinical trials have demonstrated positive outcomes (15, 30).
It is important to note that studies reporting favorable effects often assessed therapeutic — rather than preventive — use of probiotics in infants with diagnosed colic. Our study, being preventive, is more aligned with trials that have not found significant behavioral changes. Additionally, the accuracy of colic behavior recording remains a challenge, even when validated tools like the Barr scale are used, as parental reporting introduces subjectivity and potential bias.
The most plausible mechanism for the observed effects of synbiotics is their modulation of the infant gut microbiota. Emerging evidence suggests that dysbiosis — characterized by reduced Lactobacillus and Bifidobacterium populations — may contribute to GI inflammation, gas production, bloating, and disrupted bowel motility, all of which can lead to colic (7, 31). Probiotics may alleviate these symptoms by restoring microbial balance. Moreover, L. reuteri has been shown to influence pain perception via modulation of transient receptor potential vanilloid 1 channels and related neural pathways, suggesting a neuro-GI mechanism of action (32). Thus, if synbiotics can reduce colic incidence, they may also improve maternal quality of life and reduce infant distress.
Fecal calprotectin, a marker of intestinal inflammation previously used in diagnosing inflammatory bowel disease, has also been proposed as a biomarker for IC. Therefore, reductions in colic severity may be accompanied by decreases in fecal calprotectin levels (33).
Preventive trials assessing the effects of synbiotic supplementation (such as 10-drop formulations) on excessive infant crying remain limited. Our study aimed to help fill this gap. Despite its strengths — including randomized block design, triple-blinding, and the use of a validated behavioral scale — this trial has some limitations: A) although follow-up efforts were extensive, loss-to-follow-up was relatively high, albeit within acceptable thresholds. B) infant behavior data were collected through maternal self-reporting, introducing potential bias due to variability in maternal perceptions and recording accuracy. C) maternal dietary intake was not formally assessed, although mothers were instructed to maintain their usual diet during the study period.
4.1. Limitations
The short period of surveyed time is a limitation point of this study.
4.2. Conclusions
This study evaluated the preventive effects of synbiotic supplementation on IC, maternal quality of life, fecal calprotectin levels, and colic-related behaviors. Daily administration of a synbiotic formula for two months was associated with a reduction in colic symptoms and fecal calprotectin levels in both groups, although these differences were not statistically significant. Further large-scale, well-designed randomized trials are warranted to confirm these findings and explore the mechanisms underlying the potential benefits of synbiotic in early infancy.