1. Background
Chronic otitis media (COM) varies from simple dry tympanic membrane perforation to extensive draining cholesteatoma (1). It certainly stands for one of the main areas of interest in modern clinical otology, considering enormous studies on this subject (2). Without management, it can cause diverse complications such as tinnitus, hearing loss, labyrinthitis, facial nerve paralysis, and intracranial complications (1).
COM appears with or without cholesteatoma. Cholesteatoma stands for keratinizing squamous epithelium in the middle ear space. Intermittently, it becomes infected, the ear drains and may lead to ossicular chain erosion; in which case, an audiogram will demonstrate conductive hearing loss. COM diagnosis is made based on history and physical examination. A history of hearing loss, otorrhea, recurrent ear infections, or trauma gives a good clue for diagnosis (1).
Computed tomography (CT) is necessary for all patients suspected of having complications of otitis media. CT scan is a reliable method for studying the status of the mastoid air cell system, middle ear, internal auditory meatus (IAM), and also intracranial complications of otitis media. (3, 4) Treatment of COM is surgical (tympanoplasty with or without mastoidectomy). Having enough knowledge of the middle ear before the surgery can help the surgeon choose the optimal surgical procedure and achieve appropriate results (1).
Evaluation of the temporal bone is difficult because of its complex anatomy containing multiple small structures within a moderately compact area. Further information revealed by three dimensional images gives a better understanding of temporal bone anatomy and advances the capability to evaluate related disease, thus optimizing surgical planning (5).
2. Objectives
This study was conducted to compare spiral and conventional CT scan in evaluating complications of COM.
3. Patients and Methods
In this cross-sectional study, 62 ears of 50 patients with COM who were referred to our otolaryngology clinic were studied.
Essential clinical examinations and hearing tests including pure tune audiometry, tympanometry, speech discrimination test, and speech reception threshold were performed on all patients. Demographic data and clinical hearing evaluation findings were also recorded in a questionnaire.
Fifty patients enrolled in the study underwent plane and three-dimensional CT scan (PHILIPS-MX 8000/ 16-section spiral CT scanner). The studies were performed with the following parameters: 1.00-mm collimation, 1.00-mm section thickness, KV = 120, MA = 270, PITCH = 0.5, reconstruction thickness = 0.75 mm, and collimation = 0.6 mm.
Ossicles changes, mastoid cavity, tympanic cavity and presence of cholesteatoma were studied. The results of the two methods were then compared and interpreted by a radiologist, recorded in questionnaires, and analyzed.
A radiologist reported all scans. He was blinded to Patients' names, history and physical examination. Since only one radiologist reported the CT scans, inter-observer reliability was not evaluated in this study. In the case of intra-observer reliability, the agreements were tested and presented with Kappa values, the consistency was also studied using McNemar test. SPSS Ver. 18 for Windows (SPSS Inc., Chicago, Il, USA) was used to perform statistical analysis. Results are expressed as mean ± SD. Logistic regression analysis and Kappa coefficient of agreement were used for statistical analysis. The statistical significance was set at P < 0.05.
The study protocol was reviewed and approved by the ethics committee of Mashhad Branch, Islamic Azad University. Written informed consent was obtained from all patients.
4. Results
Fifty patients were enrolled in the study, 31 females (62%) and 19 males (38%) [mean age: 39.4 ± 16.5 years; range: 9 - 72]. Tinnitus was the most frequent chief complaint (48%) and vertigo (16%) had the lowest frequency. Other complaints were as follows: hearing loss (46%), otorrhea (46%), retro-auricular pain (32%), itching (26%), otalgia (24%), and headache (20%).
The majority of patients had nasal septal deviation (16%). Marginal perforation (37%) had the highest frequency among 62 ears in physical examination; whereas, total and subtotal perforation had the lowest frequency (15%). Totally, 40 ears had otorrhea in physical examination of which 68% (n = 26) had fetid smelling; whereas, 35% (n = 14) did not smell. Purulent (60%) and serous (17.5%) otorrhea had the highest and the lowest frequency among all types of otorrhea, respectively. Mucoid otorrhea was observed in nine (22.5%) ears with otorrhea. Other predisposing factors were allergy (8%), corneal hypertrophy (2%), adenoid hypertrophy (2%) (n = 1). Cleft palate and taking ototoxic drugs were not seen in the patients.
A group of patients had single bony destruction with dislocation (Figure 1A-C and 3B) and some of them had more bony lesions. According to the results of our study, decrease of mastoid air cells were seen in 51 (82.3%) ears in conventional CT and in 58 (93.5%) ears in spiral CT, the diagnostic value difference in this issue was significant.
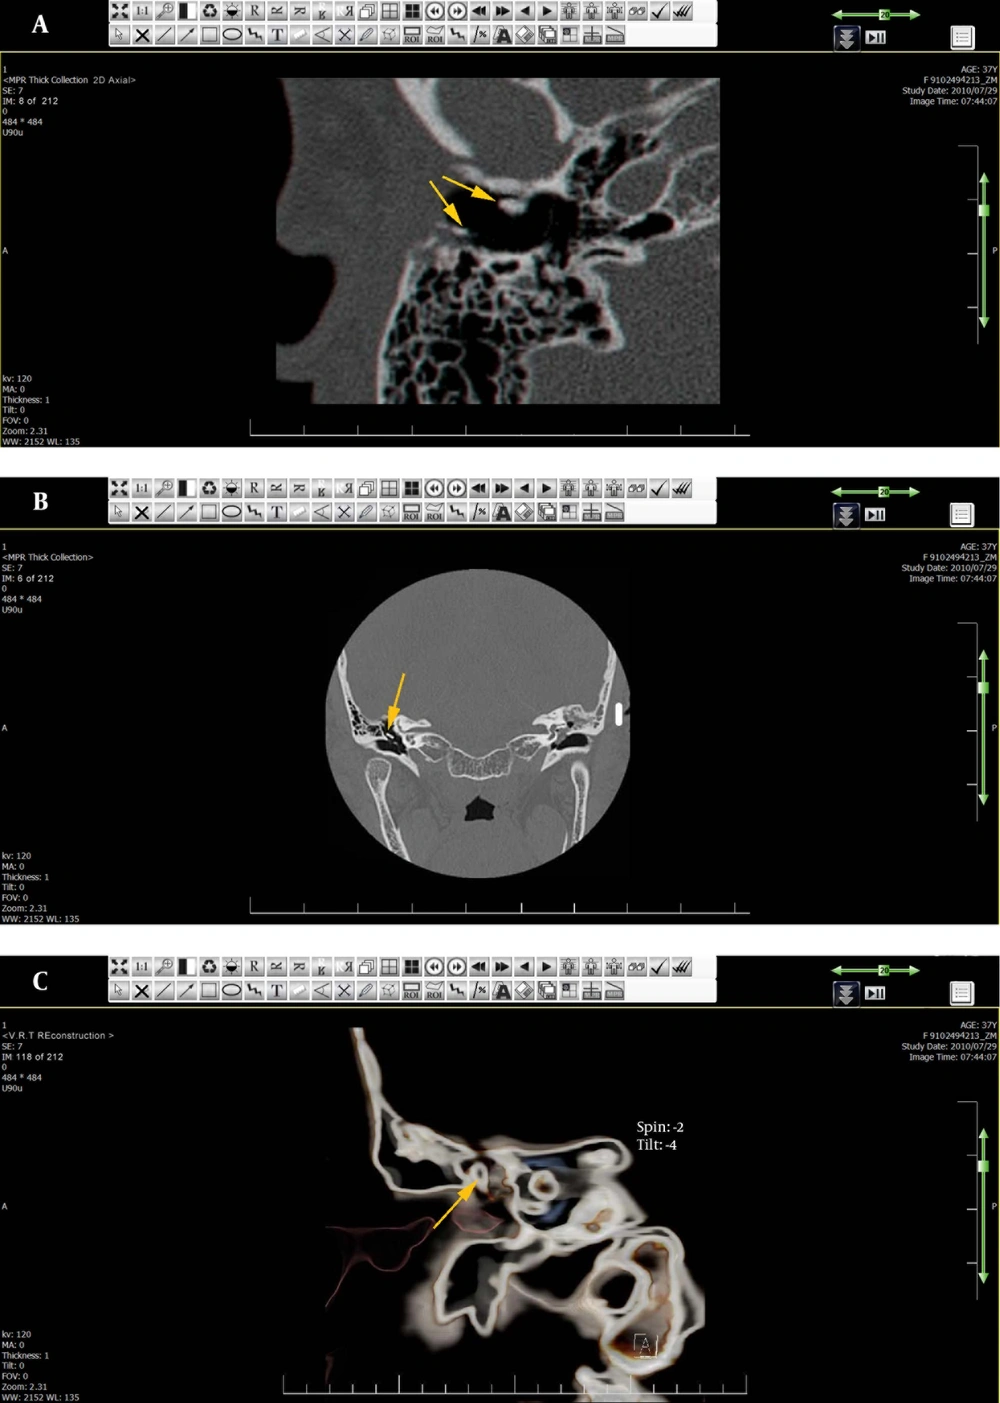
Figure 1.
A 37-year-old woman with right ear hearing loss. A, Axial view 2D CT image, Dislocation of the ossicular chain is better shown in this view (malleoloincus dislocation) (arrows); B, Coronal view of conventional CT scan; C, Three dimensional reconstructed image in the same patient.
In our study, conventional CT showed no decreased volume in tympanic cavity while it was seen in one ear (1.6%) by means of spiral CT. Also opacity in the tympanic cavity was seen in eight (12.9%) ears by conventional CT, but spiral CT showed 25 (40.3%) ears with opacity in the tympanic cavity (P value = 0.0001).
Ossicular chain erosion was identified in 11.2% (n = 7) of conventional CT reports, whereas spiral CT scan recognized erosion in 37% (n = 23) (Figure 2A and 3A). Actually, conventional CT scan reported 4.8% (n = 3) erosion in the incus (Figure 2A and B), 3.2% in the stapes (n = 2), and 3.2% in the malleus (Figure 2A and B) (n = 2); while spiral CT scan showed 16.1% (n = 10) erosion in the incus, 13% (n = 8) in the stapes, and 8% (n = 5) in the malleus.
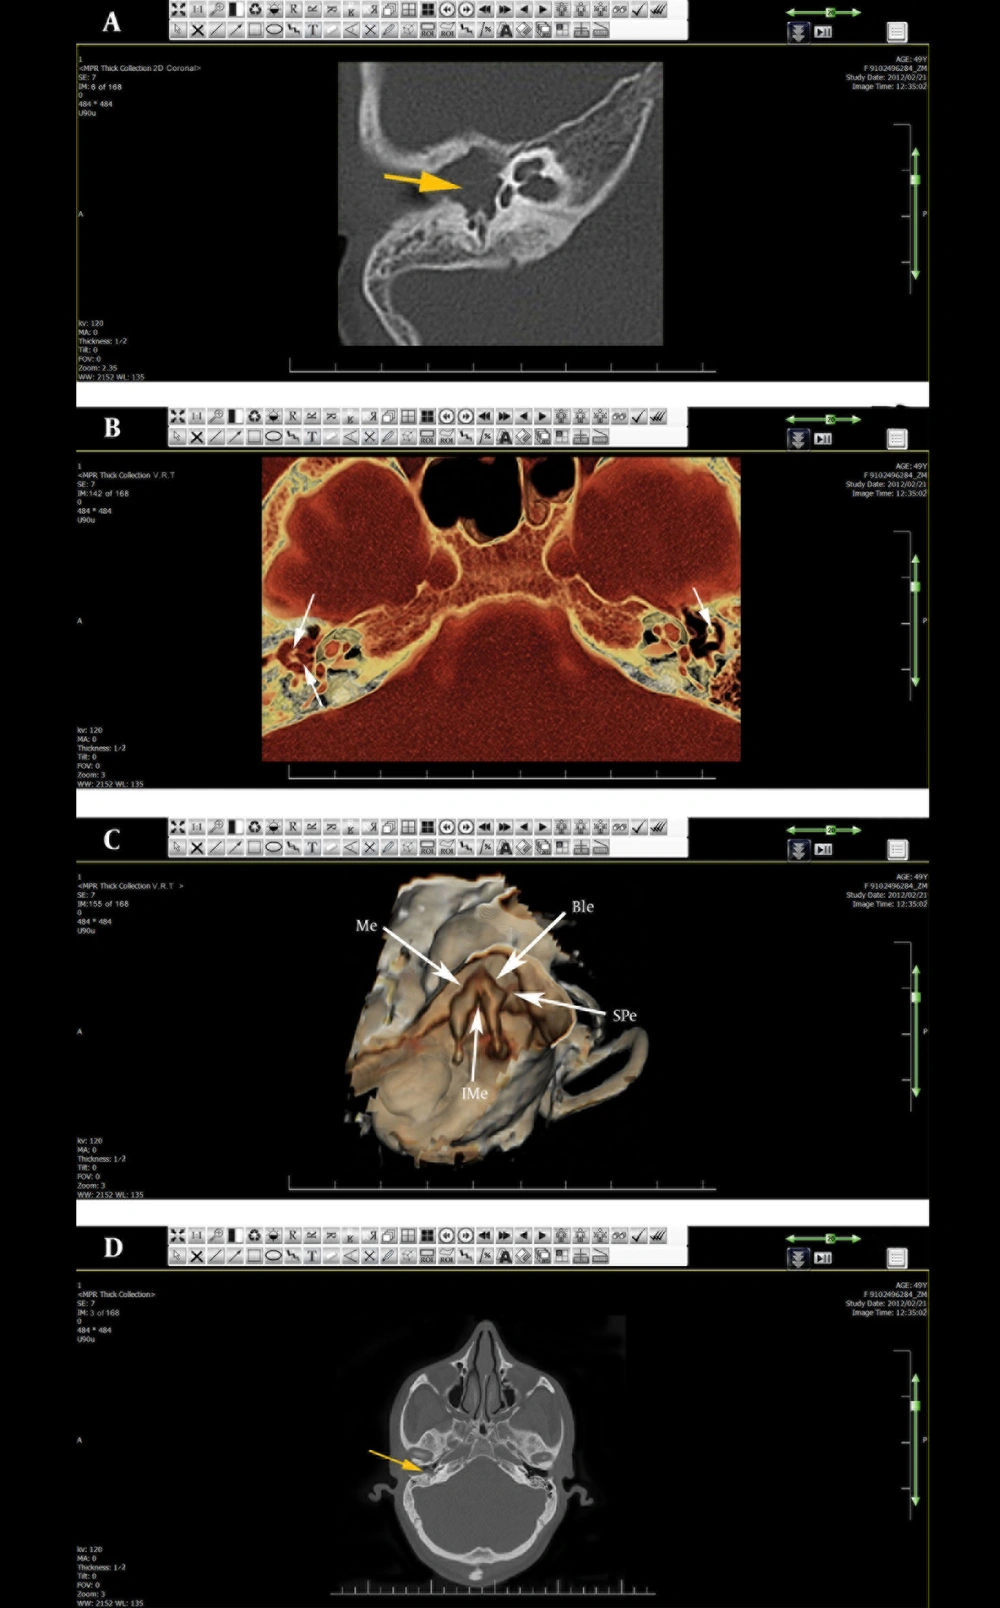
Figure 2.
Cholesteatoma in a 49-year-old man with right-sided hearing loss and discharge. A, Axial view of two dimensional CT image. Erosion of the right malleus and incus is detected. The stapes (St) is intact; B, 3D CT reformatted image in the same patient shows erosion of the right malleus and incus (arrows). The stapes is intact and is better seen in the 3D image. The left malleus and incus (arrow) are normal; C, 3D volume rendered (VR) CT image (lateral view after dissection of the anteroinferior portion of the external auditory canal shows pressure erosion of the head of the right malleus (Me) and the body of the incus (BIe), along with nearly complete erosion of the short process of the incus (SPe). Extension of the erosion into the incudomalleolar articulation (IMe) is also noted; D, Axial view of conventional CT scan shows cholesteatoma causing right-sided hearing loss in the same patient.
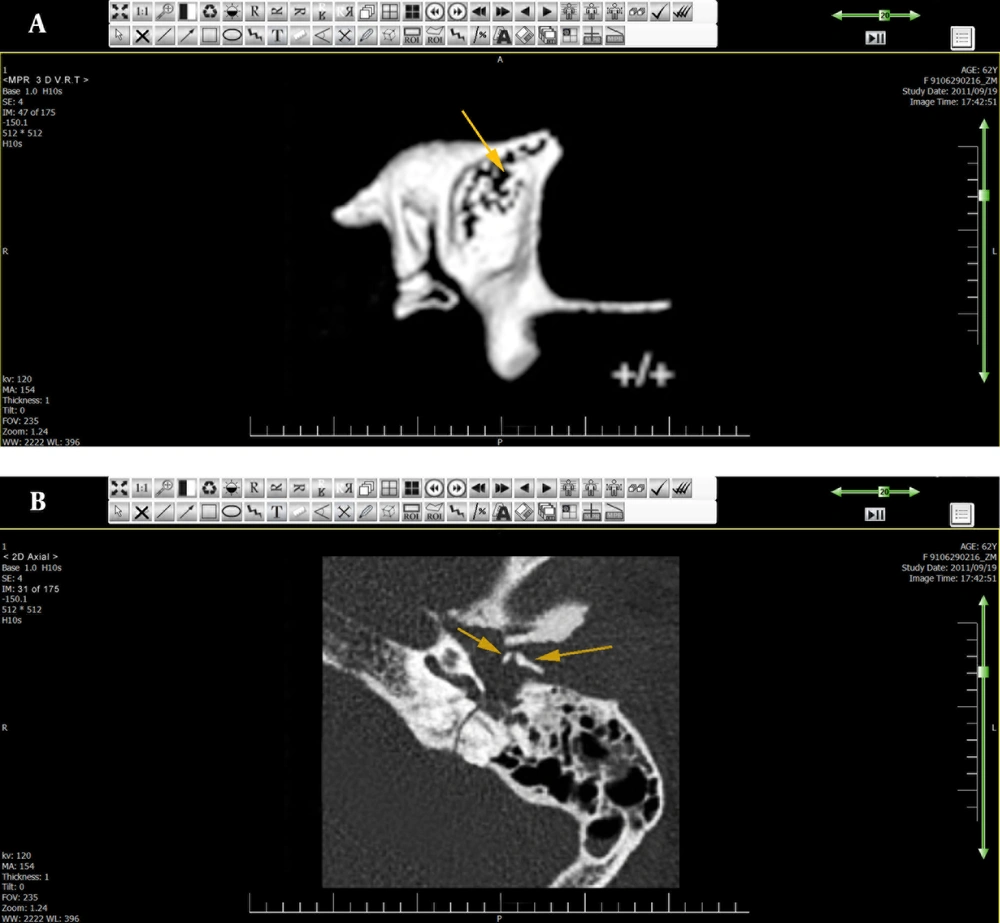
Figure 3.
A 62-year-old woman with missed old trauma and hearing loss in the left ear. A, 3D reconstructed volume rendered (VR) CT image. Destruction and erosion in the malleolus and mild stapoincus dislocation that is best shown in 3D VR in comparison with 2D images; B, 2D left axial view of CT scan image in the same patient. Malleo-inco-stapes dislocation due to previous trauma is noted.
Table 1, shows agreement between spiral and conventional CT scan for ossicle erosion in detail. A significant agreement between spiral CT and conventional CT results was observed in recognizing ossicle erosion (Kappa Coefficient: 0.355) (McNemar test P-value: 0.0001). Table 2, shows agreement between spiral and conventional CT scan in ossicle destruction. No significant agreement between spiral CT and conventional CT results was observed for recognizing ossicle destruction (Kappa Coefficient: 0.101) (McNemar test P-value: 0.0001). Cholesteatoma was found in two cases (3.22%) by conventional CT, but 26 (42%) by spiral CT (Figure 2A-D) Table 3 shows agreement between spiral and conventional CT scan in the presence of cholesteatoma. No significant agreement was detected between spiral CT and conventional CT results for recognizing the presence of cholesteatoma (Kappa Coefficient = 0.088) (McNemar Test P-value = 0.0001).
Table 1.
Agreement Between Spiral and Conventional CT Scan in Detecting Ossicle Erosion
| Conventional CT | Spiral CTa | Measurement of Agreement | P Value (McNemar Test) | |||
|---|---|---|---|---|---|---|
| Yes | No | Total | Kappa | P Value | ||
| Malleus | 0.551 | 0.0001 | 0.250 | |||
| Yes | 2 (40.0) | 0 (0.0) | 2 (3.2) | |||
| No | 3 (60.0) | 57 (100.0) | 60 (96.8) | |||
| Total | 5 (100.0) | 57 (100.0) | 62 (100.0) | |||
| Incus | 0.418 | 0.0001 | 0.016 | |||
| Yes | 3 (30.0) | 0 (0.0) | 3 (4.8) | |||
| No | 7 (70.0) | 52 (100.0) | 59 (95.2) | |||
| Total | 10 (100.0) | 52 (100.0) | 62 (100.0) | |||
| Stapes | 0.367 | 0.0001 | 0.031 | |||
| Yes | 2 (25.0) | 0 (0.0) | 2 (3.2) | |||
| No | 6 (75.0) | 54 (100.0) | 60 (96.8) | |||
| Total | 8 (100.0) | 54 (100.0) | 62 (100.0) | |||
| Total | 0.355 | 0.0001 | 0.0001 | |||
| Yes | 7 (30.4) | 0 (0.0) | 7 (11.3) | |||
| No | 16 (69.6) | 39 (100.0) | 55 (88.7) | |||
| Total | 23 (100.0) | 39 (100.0) | 62 (100.0) | |||
aData are presented as No. (%).
Table 2.
Agreement Between Spiral and Conventional CT Scan in Detecting Ossicle Destruction
| Conventional CT | Spiral CTa | Measurement of Agreement | P Value (McNemar Test) | |||
|---|---|---|---|---|---|---|
| Yes | No | Total | Kappa | P Value | ||
| Malleus | 0.315 | 0.001 | 0.125 | |||
| Yes | 1 (20.0) | 0 | 1 (1.6) | |||
| No | 4 (80.0) | 57 (100.0) | 61 (98.4) | |||
| Total | 5 (100.0) | 57 (100.0) | 62 (100.0) | |||
| Incus | 0.098 | 0.074 | 0.0001 | |||
| Yes | 1 (6.7) | 0 | 1 (1.6) | |||
| No | 14 (93.3) | 47 (100.0) | 61 (98.4) | |||
| Total | 15 (100.0) | 47 (100.0) | 62 (100.0) | |||
| Stapes | 0.189 | 0.011 | 0.0001 | |||
| Yes | 2 (13.3) | 0 | 2 (3.2) | |||
| No | 13 (86.7) | 47 (100.0) | 60 (96.8) | |||
| Total | 15 (100.0) | 47 (100.0) | 62 (100.0) | |||
| Total | 0.101 | 0.069 | 0.0001 | |||
| Yes | 4 (11.4) | 0 | 4 (6.5) | |||
| No | 31 (88.6) | 27 (100.0) | 58 (93.5) | |||
| Total | 35 (100.0) | 27 (100.0) | 62 (100.0) | |||
aData are presented as No. (%).
Table 3.
| Conventional CT | Spiral CT | ||
|---|---|---|---|
| Yes | No | Total | |
| Yes | 2 (7.7) | 0 | 2 (3.2) |
| No | 24 (92.3) | 36 (100.0) | 60 (96.8) |
| Total | 26 (100.0) | 36 (100.0) | 62 (100.0) |
aData are presented as No. (%).
bKappa coefficient of agreement = 0.088 , P value = 0.091.
cMcNemar Test P value = 0.0001.
Significant agreements between spiral CT and conventional CT results for recognizing mastoid air cells (Kappa Coefficient: 0.485) (McNemar Test P-value = 0.016), and opacity in the tympanic cavity (Kappa Coefficient: 0.360), (McNemar Test P-value = 0.0001) were also observed.
5. Discussion
CT is helpful in the work up of patients with severe hypoacusis. In cases of surgical failure, CT also plays a key role in identifying dislocation of ossiculoplasty or destruction of the middle ear due to fluid effusion (6, 7). Although CT gives important information about the middle ear and mastoid, pathology assessment based on CT alone is not appropriate (8). Spiral CT imaging plays a key role in diagnosing cholesteatoma and particularly soft tissue occupancy and bony erosion that can provide essential information for surgery (9). When joined with clinical findings, CT scans can be an enlightening guide to otolaryngologists for preoperative assessment of tympanosclerosis (7).
A moderate to good correlation between preoperative radiological images and intra-operative clinical findings on tympanic cholesteatoma, mastoid cholesteatoma, and ossicular chain erosion was reported in a study conducted by Gerami et al. There was also a weak and insignificant correlation in cases of lateral semicircular canal (LSCC) fistulae, facial canal dehiscence and tegmen tympani erosion (6).
Spiral CT scan precisely shows signs of bony erosion due to cholesteatoma in the middle ear and different sized soft tissue occupancy derived from different sites. Comparing the findings during operation and CT imaging before surgery, the consistency in bone erosion, in soft tissue occupancy and in invasion of ossicle chain was 89.1%, 94.4% and 89.3%, respectively (9).
Three dimensional temporal bone reconstruction using sagittal tomographic images is practical in the assessment of the state of mastoid air cell system development and in studying the pathology in middle ear disease (10). Three dimensional CT of the middle ear can characterize the auditory ossicles dispassionately and can present detailed diagnosis (11). Preoperative CT scan may be supportive in decision making for surgery in cases of ossicular erosion and cholesteatoma. Regardless of limitations, three-dimensional CT is a useful accessory to the management of chronic otitis media (6).
Results of our study are in accordance with most of the published articles. In 1989, Grevers et al. showed that preoperative high resolution CT (HRCT) is a reliable diagnostic method to reveal middle ear abnormalities (12). In 1996, Gong et al. concluded that 3D helical CT of the middle ear can represent the auditory ossicles objectively and can present detailed diagnosis (11). Leng et al. also suggested “Axial and coronal HRCT for external and middle ear deformation is highly valuable for decision making and surgical planning” (13). Rodt et al. stated that high-quality 3D-models allow accurate imaging of anatomical structures. They also suggested middle ear 3D-visualisation using CT-data for surgical planning (14). Truy et al. also mentioned image reconstruction method as a practical complement to classical CT images in evaluating constitutional abnormalities of the middle ear (15). Sun et al. concluded that with proper approach, CT virtual endoscopy has the benefit of demonstrating ear ossicles and their connections, which is an excellent supplement of usual CT (16).
However, 3D simulation CT has its limitations. Wang et al. compared CT methods in evaluating ossicular chain. In their study, the accuracy of CT virtual endoscopy (CTVE) images in identifying ossicular destruction was 92.6%, significantly higher than that of axial HRCT (83.9%) and multiplanar reformation (MPR) (76.5%) images. CTVE could also clearly reveal the postoperative condition and congenital dysplasia of the auditory ossicular chain. They concluded that CTVE can clearly show a three-dimensional image of the auditory ossicular chain and is helpful in evaluating diseases of the ear, especially auditory ossicles. They also emphasized that CTVE could not clearly exhibit abnormal soft tissue within the tympanic cavity, abnormalities of the tympanic membrane and tympanic walls, and could be simply influenced by artificial factors (17).
Himi et al. suggested that virtual middle ear simulations precisely represent major intraoperative findings and may have a significant role in preoperative planning and postoperative assessment in otology (18). Dahmani-Causse et al. compared two techniques of CT on evaluating temporal bone anatomy and pathology and showed that cone beam CT (CBCT) provides reliable morphologic evaluation of temporal bone due to higher spatial resolution than multislice helical computed tomography (MSCT) with significantly reduced radiation dose (19). In a similar study, Martin et al. studied the value of virtual endoscopy (VE) in the diagnosis of ossicular chain lesions and compared VE and two-dimensional (2D) spiral CT data. They emphasized on the value of VE in the diagnosis of dislocation of the ossicles and ossicular prostheses and mentioned that VE was less effective in diagnosing other pathologies of the ossicular chain (epitympanic fixations, othosclerosis, ossicularlysis and minor aplasia) (20).
Implementation of methods to correlate 2D and 3D images to post-processing-software will be useful for radiological diagnosis, surgical planning (the preoperative and intraoperative understanding of structures and lesions), and teaching. Three dimensional images will help shorten the operation time and improve the safety of the operation.
In conclusion, spiral CT scan is superior to conventional CT scan in the diagnosis of lesions in chronic otitis media before operation and it can be used for detailed assessment of ossicular chain in such patients. Studies with larger sample volumes associated with surgical findings are recommended.