Retro-Aortic Inverted Left Renal Vein: A Rare Anomaly Found in a Renal Donor

Authors

Sofia Sabouri1, Ashrafsadat Hosseini1,*, Seyedeh Shirin Shivaei2
1Department of Radiology, Shohada-e-Tajrish Hospital, Shahid Beheshti University of Medical Sciences, Tehran, Iran
2Department of Radiology, Tooska Medical Imaging Center, Tehran, Iran
*Corresponding Author: Corresponding author: Ashrafsadat Hosseini, Department of Radiology, Shohada-e-Tajrish Hospital, Shahid Beheshti University of Medical Sciences, Tehran, Iran. Tel: +98-9132592680, E-mail: Email: hosseinibamakan@yahoo.com

Iranian Journal of Radiology:Vol. 12, issue 2; e11374
Published online:Apr 22, 2015
Article type:Case Report
Received:Mar 31, 2013
Accepted:Jun 03, 2013
How to Cite:Sabouri S, Hosseini A, Shivaei SS. Retro-Aortic Inverted Left Renal Vein: A Rare Anomaly Found in a Renal Donor. I J Radiol. 2015;12(2):e11374. doi: https://doi.org/10.5812/iranjradiol.11374

Abstract

Awareness of the renal vascular anatomy including variants of the renal vein is important for abdominal and renal surgeries, such as renal transplantation. The complex embryological development of the renal vein results in the following variations: additional renal veins on the left side, circum-aortic renal collar and retro-aortic renal veins. In this report, we present a case of a 35-year-old renal donor who had a rare renal vein anomaly that had been shown by computed tomography (CT) angiography. The left renal vein was single, and just before draining into the inferior vena cava (IVC) made two branches craniocaudally, which both passed posteriorly to the aorta and entered separately into the IVC.

Highlights

1. Introduction

Complete knowledge of the anatomy and variations of renal veins is necessary for retro-peritoneal surgeries, including renal transplantation. Failure to diagnose these anomalies at surgery may lead to bleeding, nephrectomy and even death (1-3). Furthermore, hematuria, proteinuria or varicocele may be caused by left renal vein (LRV) anomalies, which are usually detected incidentally (3). These variations are more frequently detected and better assessed with the advent of multidetector computed tomography (CT) (4). Computed tomography angiography (CTA) has been accepted as a reliable method for assessment of renal donors (5). LRV anomaly is more common than that of right side (6). There are few reports of rare cases of renal vein anomalies. Yesildag et al. reported LRV anomaly in 32 out of 984 cases (3.2%) in their study. Twenty-three (2.3%) of the cases were retro-aortic and 9 (0.9%) were circum-aortic LRV (2). Other variations in LRV are also reported (7-10). In this case report, we introduce a case with uncommon form of LRV drainage to the inferior vena cava (IVC).

2. Case Presentation

The patient was a 35-year-old man who was a renal donor. Routine ultrasonography of kidneys was normal. He was scheduled for abdominal CTA to define any preoperative vascular anomalies. Computed tomography angiography (CTA) was done with a 4-multidetector row CT scanner (light-speed QXi, GE Healthcare, Milwaukee, USA). Protocol of scan included 1.25 mm collimation, 7.5mm table speed and 1.5 pitch. Afterwards, One hundred milliliter of visipaque (300 mg/mL) was injected by a power injector. The scan was performed from diaphragm down to the level of pubic symphysis. To achieve optimal opacification of renal vein in addition to renal artery in renal donors, we use bolus tracking method, in which we start scan in the late arterial phase. Data were analyzed and processed on a workstation (ADW 4.1; GE medical system). Images were reviewed by the multiplanar reconstructions, maximum intensity projection and volume rendering options. Duplicated renal artery was observed on right side. The accessory renal artery originated from abdominal aorta adjacent to superior mesenteric artery, and both renal arteries had normal diameter and density (Figure 1A and B). The LRV was single, and just before draining into IVC, made two branches craniocaudally, which both passed posteriorly to the aorta and each one had a separate drainage to IVC (Figure 2A, B and C). Right renal vein and its drainage into IVC were normal (Figure 3).
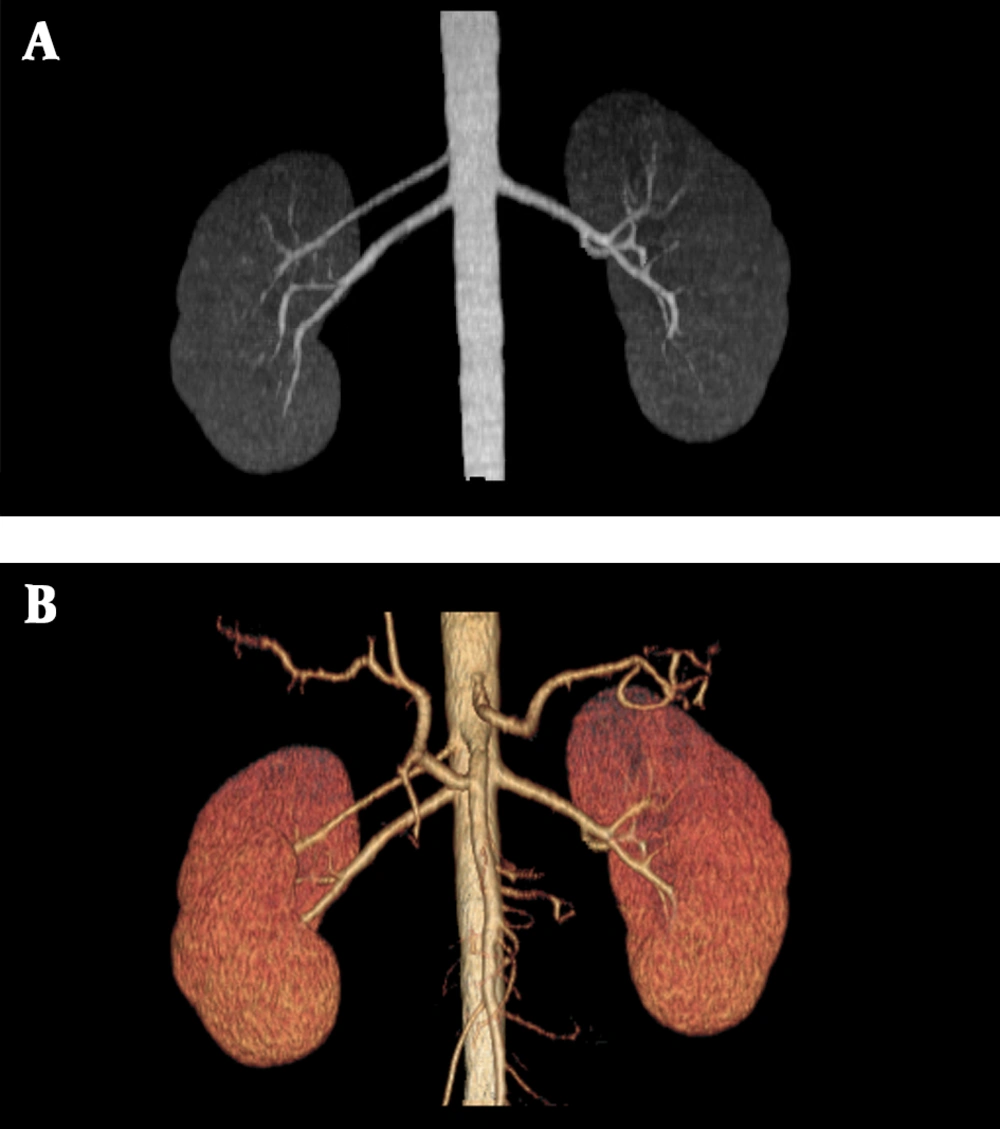
A 35-year-old renal donor man with duplicated right renal artery (A,B)
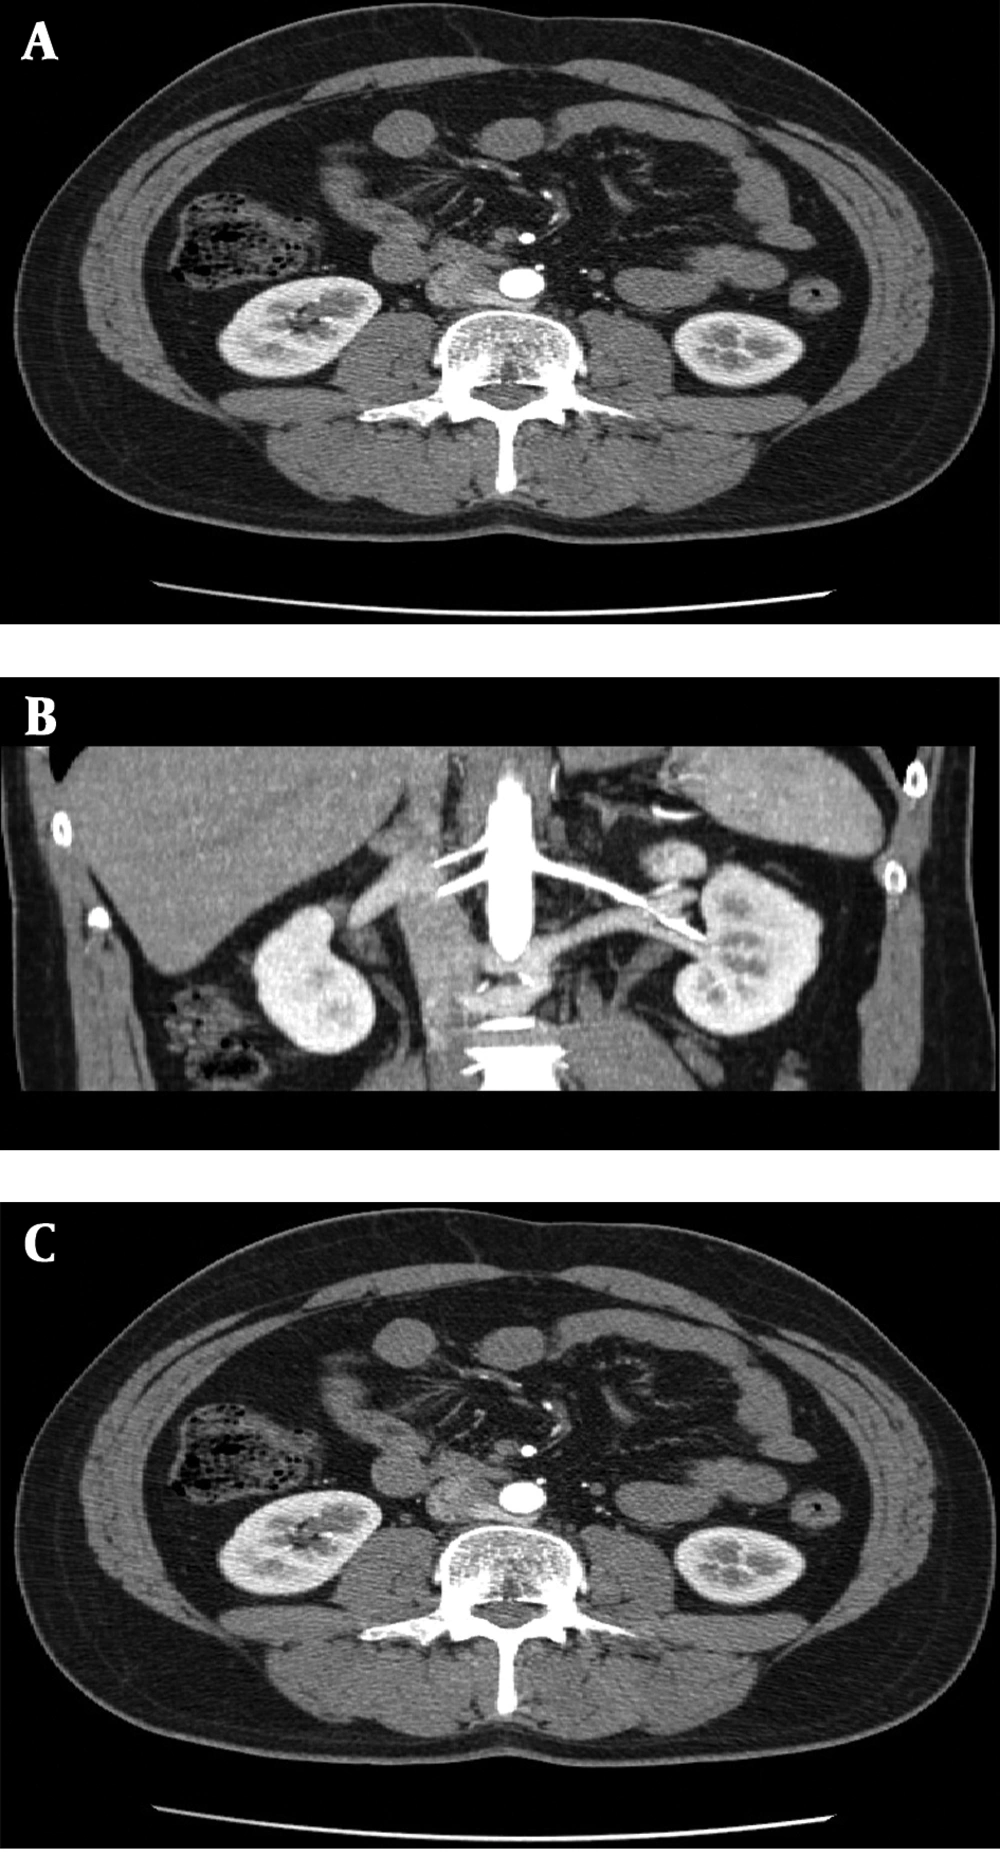
Figure 1.
A 35-year-old renal donor man with duplicated right renal artery (A,B)
Single retro-aortic left renal vein with dual drainage to inferior vena cava (A-C)
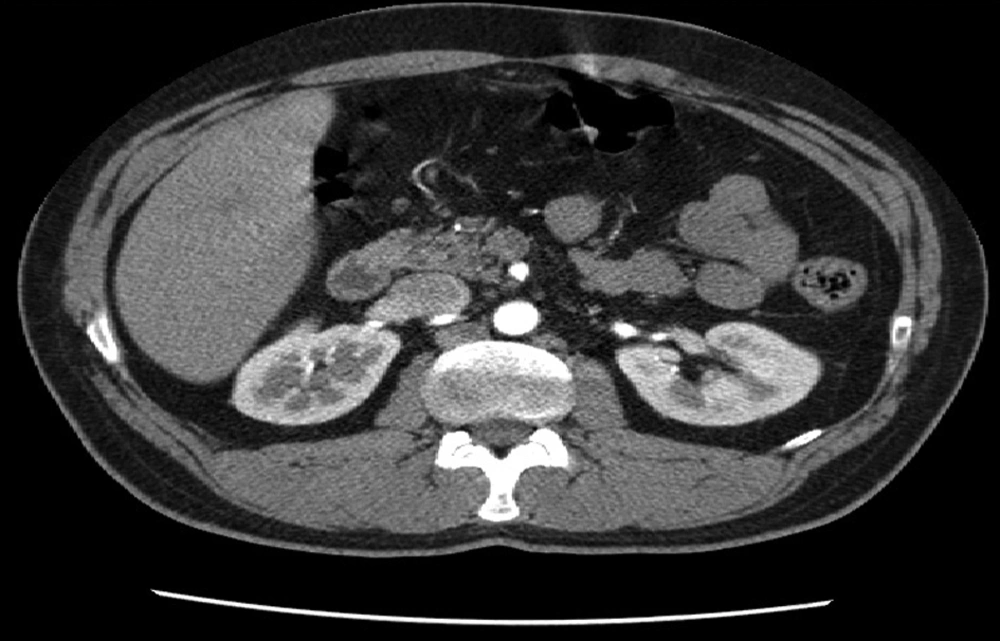
Figure 2.
Single retro-aortic left renal vein with dual drainage to inferior vena cava (A-C)
Normal right renal vein
Figure 3.
Normal right renal vein

3. Discussion

In renal transplantation, the morphology of the renal veins has a special importance in that variations may affect the method of the surgery. For example, variations limit availability of vein for mobilization methods. During surgery, the surgeon may see a pre-aortic vein while being unaware of an additional retro-aortic portion or a posterior primary branch, and may disturb it while mobilizing the kidney (1-3). Thus, imaging screening of potential renal transplantation donors seems to be critical. These variations are more frequently detected and better assessed with the advent of multidetector CT. Computed tomography angiography (CTA) is a noninvasive accurate method to evaluate renal donor (5), even though venous anomalies can be distinguished in routine abdominal CT scan with a careful review (2). During fetal development, there are 3 major types of renal vein (I, II, III) based on the drainage pattern of the primary renal vein tributaries. The most common type is type 1A, which has two upper and lower primary tributaries that combine together to make the main renal vein. The second most common is type 1B with upper, lower and posterior tributaries. Type 3 has the additional renal vein too (11). Classically, there are variations of the LRV configuration: a single-renal vein crossing in front of the aorta to drain into the IVC (normal), retro-aortic LRV, duplication of the IVC or transposition of the IVC and circum-aortic LRV (2, 3, 8). There are few reports of rare cases of renal vein anomalies. Brancatelli et al. reported a 27-year-old man evaluated with a 1-year history of recurrent right flank pain, hematuria, fever and dysuria. Images showed a retro-aortic (LRV) attaching the left common iliac vein (7). Turgut et al. reported a retro-aortic (LRV) attaching the left common iliac vein (8). There is also a variant of the retro-aortic LRV category with a possible low implantation to the IVC at the L4-L5 level, which has been described by Hoeltl and colleagues (9). Two cases, one with two LRV’s draining in two different sites of the IVC and one with orthotropic IVC and ectopic left common iliac vein represent a combination of the normal LRV attitude and low-positioned variant of the retro-aortic LRV. An additional renal vein is an accessory vein with a separate origin from renal hilum and a draining site into IVC, which has been found in more common cases (10). In our case, the (LRV) was single and just before draining into IVC made two branches craniocaudally, which both passed retro-aorticly and each one had a separate drainage to IVC. Since we could not find a similar case, our case should be the first reported one with this anomaly.

Acknowledgments

Footnotes

  • Authors’ Contributions:Dr. Sabouri developed the original idea and the protocol, abstracted and analyzed data,assessed the images, wrote the manuscript, and is a guarantor. Ashraf Sadat Hosseini and Seyedeh Shirin Shivaei contributed to the development of the protocol, abstracted data, and prepared the manuscript.

  • Funding/Support:All the procedures and steps of this study were done with the financial support of Radiology Department of Shahid Beheshti University of Medical Sciences.

References

  • 1.
    Mitty HA. Circumaortic renal collar. A potentially hazardous anomaly of the left renal vein. Am J Roentgenol Radium Ther Nucl Med. 1975;125(2):307-10. [PubMed ID: 1200228].
  • 2.
    Yesildag A, Adanir E, Koroglu M, Baykal B, Oyar O, Gulsoy UK. [Incidence of left renal vein anomalies in routine abdominal CT scans]. Tani Girisim Radyol. 2004;10(2):140-3. [PubMed ID: 15236129].
  • 3.
    Satyapal KS, Kalideen JM, Haffejee AA, Singh B, Robbs JV. Left renal vein variations. Surg Radiol Anat. 1999;21(1):77-81. [PubMed ID: 10370998].
  • 4.
    Chai JW, Lee W, Yin YH, Jae HJ, Chung JW, Kim HH, et al. CT angiography for living kidney donors: accuracy, cause of misinterpretation and prevalence of variation. Korean J Radiol. 2008;9(4):333-9. [PubMed ID: 18682671]. https://doi.org/10.3348/kjr.2008.9.4.333.
  • 5.
    Panaro F, Testa G, Balakrishnan N, Rao B, Bogetti D, Jarzembowski T, et al. Living related small bowel transplantation in children: 3-dimensional computed tomography donor evaluation. Pediatr Transplant. 2004;8(1):65-70. [PubMed ID: 15009843]. https://doi.org/10.1046/j.1397-3142.2003.00134.x.
  • 6.
    Gillaspie C, Miller LI, Baskin M. Anomalous renal vessels and their surgical significance. Anat Rec. 1916;11(3):77-86. https://doi.org/10.1002/ar.1090110304.
  • 7.
    Brancatelli G, Galia M, Finazzo M, Sparacia G, Pardo S, Lagalla R. Retroaortic left renal vein joining the left common iliac vein. Eur Radiol. 2000;10(11):1724-5. [PubMed ID: 11097397]. https://doi.org/10.1007/s003300000383.
  • 8.
    Turgut HB, Bircan MK, Hatipoglu ES, Dogruyol S. Congenital anomalies of left renal vein and its clinical importance: a case report and review of literature. Clin Anat. 1996;9(2):133-5. [PubMed ID: 8720788].
  • 9.
    Hoeltl W, Hruby W, Aharinejad S. Renal vein anatomy and its implications for retroperitoneal surgery. J Urol. 1990;143(6):1108-14. [PubMed ID: 2342169].
  • 10.
    Raman SS, Pojchamarnwiputh S, Muangsomboon K, Schulam PG, Gritsch HA, Lu DS. Surgically relevant normal and variant renal parenchymal and vascular anatomy in preoperative 16-MDCT evaluation of potential laparoscopic renal donors. AJR Am J Roentgenol. 2007;188(1):105-14. [PubMed ID: 17179352]. https://doi.org/10.2214/AJR.05.1002.
  • 11.
    Satyapal KS. Classification of the drainage patterns of the renal veins. J Anat. 1995;186(Pt 2):329-33. [PubMed ID: 7649831].

Copyright

Copyright © 2015, Tehran University of Medical Sciences and Iranian Society of Radiology. This is an open-access article distributed under the terms of the Creative Commons Attribution-NonCommercial 4.0 International License (http://creativecommons.org/licenses/by-nc/4.0/) which permits copy and redistribute the material just in noncommercial usages, provided the original work is properly cited.

Similar Articles

1
Nov
2003
Evaluation of the renal arteries in kidney donors by conventional

Evaluation of the renal arteries in kidney donors by conventional

F Fahimi,
M Saba

Fahimi F, Saba M. Evaluation of the renal arteries in kidney donors by conventional. J Inflamm Dis. 2024;7(3):e154960. doi:

17
Sep
2018
Vena Cava and Left Renal Vein Variations and Association with Other Anomalies Including Horseshoe Kidney

Vena Cava and Left Renal Vein Variations and Association with Other Anomalies Including Horseshoe Kidney

Serife Leblebisatan,
Bozkurt Gulek,
Gokhan Soker

Leblebisatan S, Gulek B, Soker G. Vena Cava and Left Renal Vein Variations and Association with Other Anomalies Including Horseshoe Kidney. I J Radiol. 2019;16(1):e79503. doi: https://doi.org/10.5812/iranjradiol.79503

28
Feb
2014

Anomalous Retro Aortic Left Brachiocephalic Vein

Ghazaleh Amjad,
Shahram Kahkouee,
Elham Pedarzadeh

Amjad G, Kahkouee S, Pedarzadeh E. Anomalous Retro Aortic Left Brachiocephalic Vein. I J Radiol. 2014;11(30th Iranian Congress of Radiology):e21272. doi: https://doi.org/10.5812/iranjradiol.21272

22
May
2018
Unusual Pattern of Left Inferior Vena Cava: A Case Report

Unusual Pattern of Left Inferior Vena Cava: A Case Report

Ah Reum Park,
Kyung Eun Bae

Park AR, Eun Bae K. Unusual Pattern of Left Inferior Vena Cava: A Case Report. I J Radiol. 2018;15(3):e60669. doi: https://doi.org/10.5812/iranjradiol.60669

30
Jun
2021
Misplaced Central Venous Catheter in the Left Hemiazygos Vein; A Case Report

Misplaced Central Venous Catheter in the Left Hemiazygos Vein; A Case Report

Najmeh Zarei Jelyani,
Razieh Sadat Mousavi-Roknabadi

Zarei Jelyani N, Mousavi-Roknabadi RS. Misplaced Central Venous Catheter in the Left Hemiazygos Vein; A Case Report. Int Cardiovasc Res J. 2021;15(2):e108483. doi:

More by these authors

Sofia SabouriPubMedScholar
Ashrafsadat HosseiniPubMedScholar
Seyedeh Shirin ShivaeiPubMedScholar
Share
Cited by
Metrics